Nonketotic hyperglycinemia: proposal of a diagnostic and treatment strategy

Yuka Suzuki1, Shigeo Kure, Masaaki Oota

  • 1Department of Pediatrics, Ehime University Graduate School of Medicine, Shitsukawa, Toon, Ehime, Japan. yusuzuki@m.ehime-u.ac.jp

Pediatric Neurology
|August 10, 2010
PubMed

Related Concept Videos

Hypoglycemia and Glucagon01:15

Hypoglycemia and Glucagon

Without prolonged fasting, healthy individuals maintain blood glucose levels above 3.5 mM due to a well-adapted neuroendocrine counterregulatory system that effectively prevents acute hypoglycemia, a potentially life-threatening condition. The primary clinical scenarios for hypoglycemia encompass diabetes treatment, inappropriate production of endogenous insulin or insulin-like substances by tumors, and the use of glucose-lowering agents in non-diabetic individuals. Notably, hypoglycemia in the...
Diabetic Ketoacidosis l: Introduction01:25

Diabetic Ketoacidosis l: Introduction
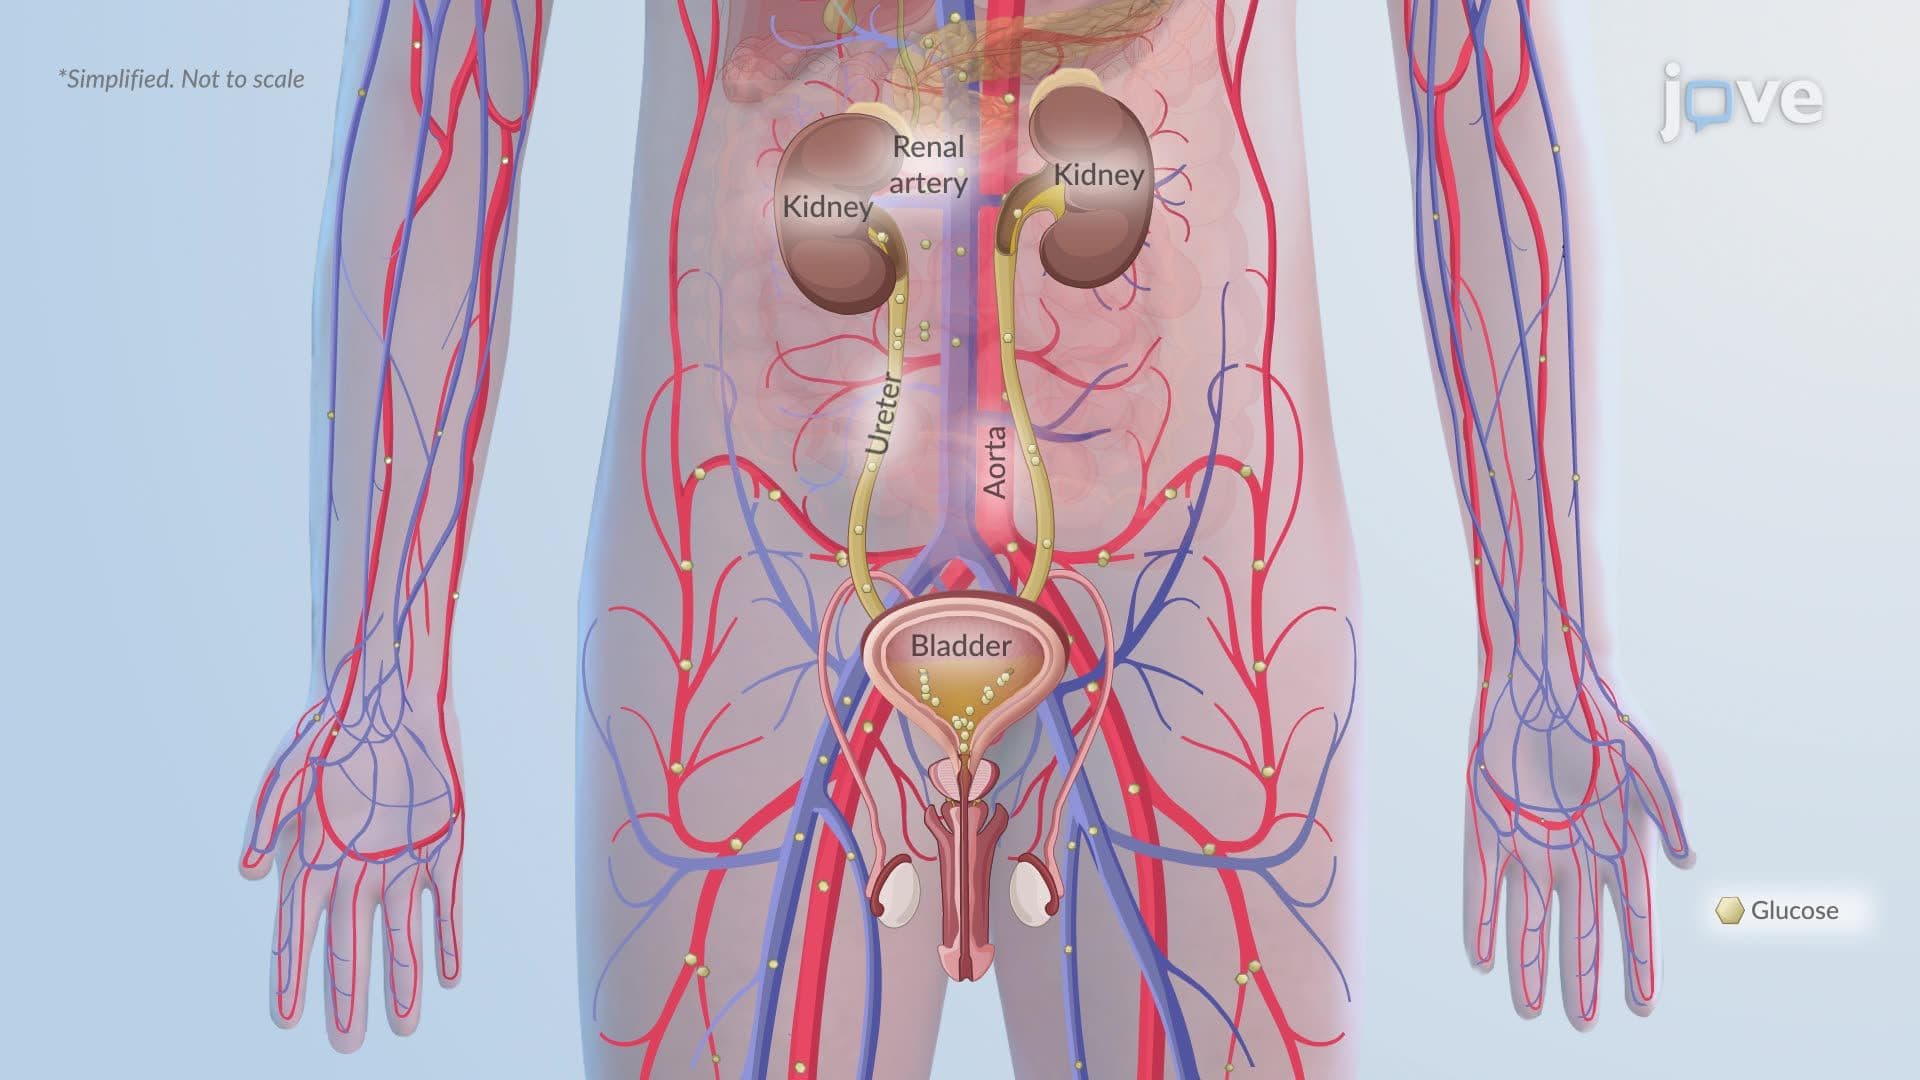
DefinitionDiabetic ketoacidosis (DKA) is an acute, life-threatening complication of diabetes mellitus, characterized by a triad of hyperglycemia (blood glucose >250 mg/dL), ketonemia or ketonuria, and metabolic acidosis (arterial pH <7.30 and serum bicarbonate <18 mEq/L). It results from insulin deficiency combined with elevated levels of counterregulatory hormones—glucagon, catecholamines, cortisol, and growth hormone—leading to increased lipolysis, hepatic ketone production, and...
Diabetic Ketoacidosis ll: Pathophysiology01:22

Diabetic Ketoacidosis ll: Pathophysiology

Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...
Diabetes: Management and Pharmacotherapy01:15

Diabetes: Management and Pharmacotherapy

The therapy for diabetes aims to alleviate hyperglycemia-related symptoms, prevent acute metabolic decompensation, and reduce chronic end-organ complications. Glycemic control is evaluated through short-term (self-monitoring, continuous glucose monitoring) and long-term (A1c, fructosamine) metrics, enabling near real-time tracking of blood glucose levels and reflecting glycemic control over specific time frames.
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis01:25

Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis

Type 2 diabetes mellitus develops gradually and is often asymptomatic in early stages.Clinical ManifestationsWhen symptoms appear, they include fatigue, blurred vision, pruritus, delayed wound healing, and recurrent infections, particularly candidal infections. Peripheral neuropathy may present as numbness or tingling in the extremities. Classic hyperglycemia symptoms—polyuria, polydipsia, and polyphagia—are less common. Most patients are overweight and frequently have associated hypertension...
Hyperglycemia01:29

Hyperglycemia

Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose levels exceed 180 mg/dL two...


