Syndrome of inappropriate ADH secretion (SIADH) associated with citalopram use

Vivek C Kirpekar1, Prashant P Joshi

  • 1Consultant Psychiatrist, Kirpekar Hospital, Nagpur.

Related Concept Videos

Diabetes Insipidus I: Introduction01:29

Diabetes Insipidus I: Introduction
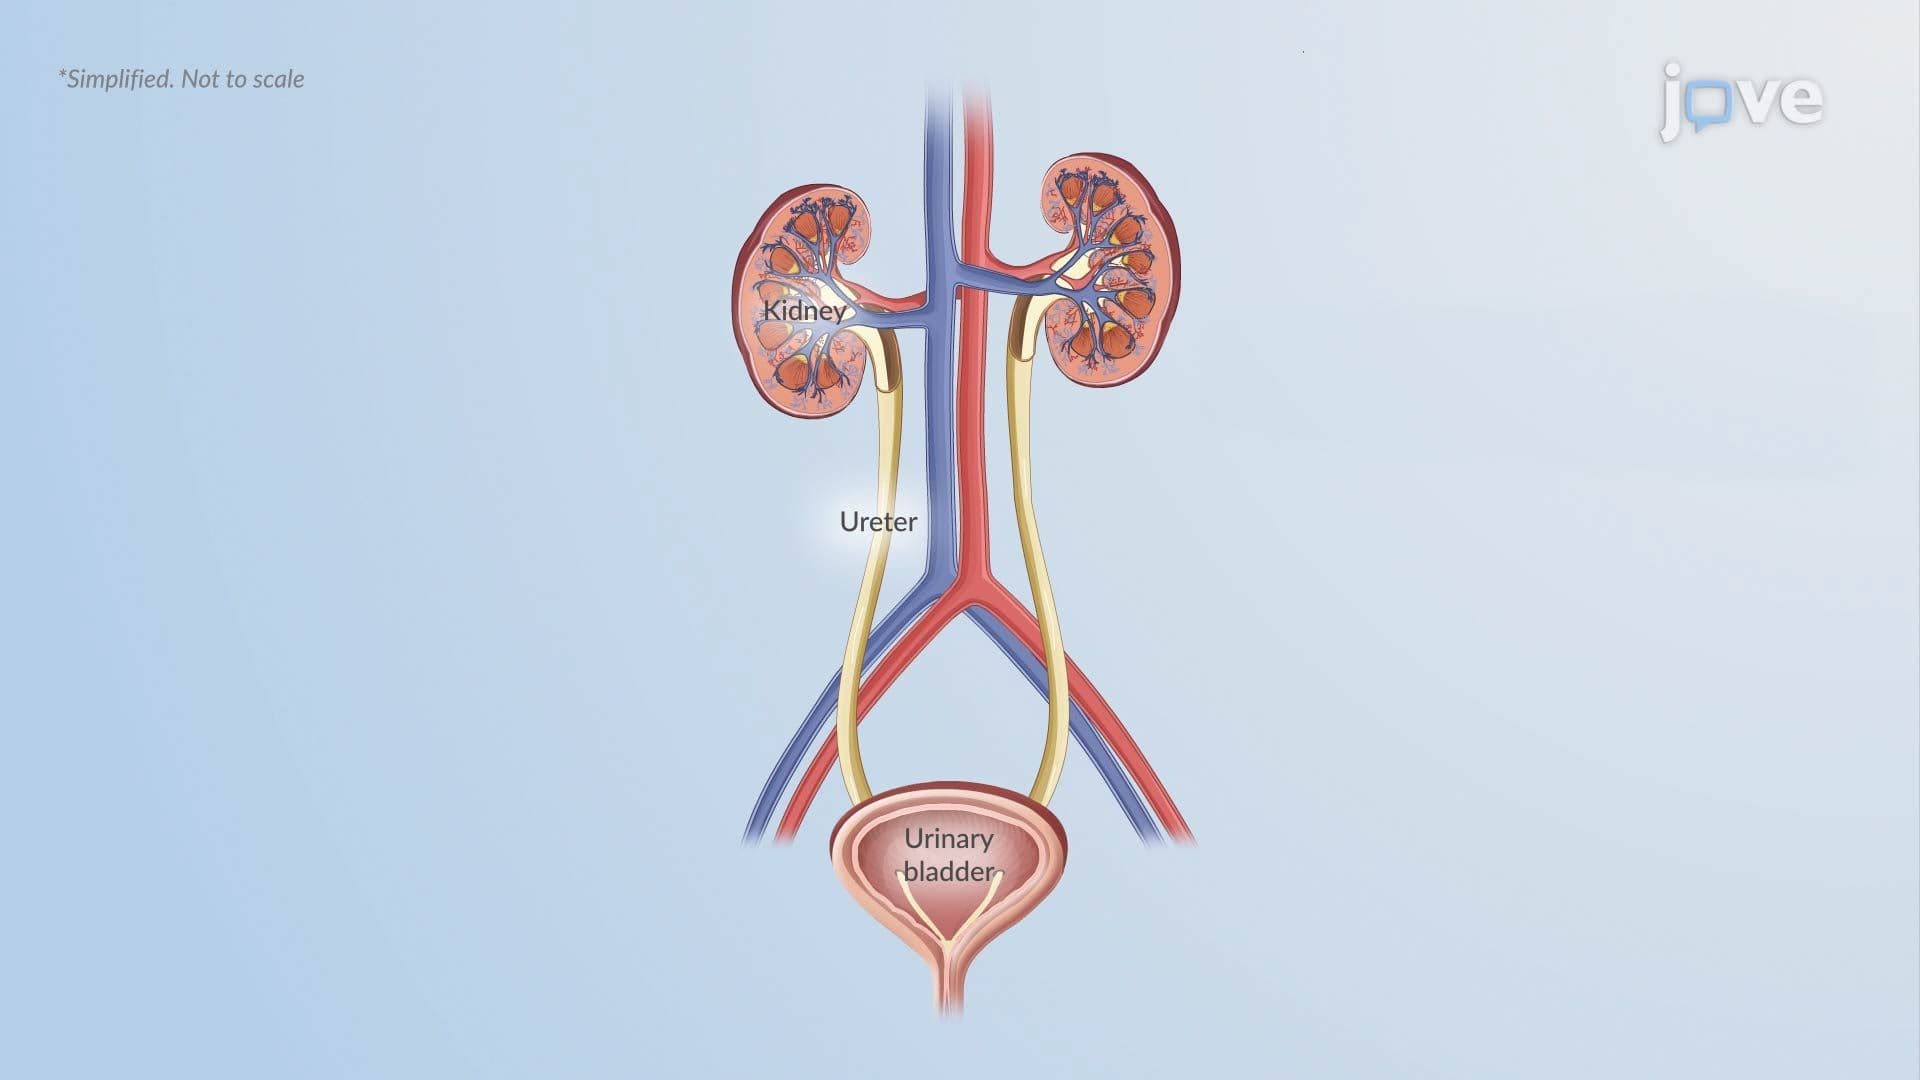
Definition Diabetes insipidus is a disorder marked by the production of large amounts of dilute urine because of impaired vasopressin production, release, or kidney response. The lack of effective vasopressin action limits water reabsorption in the renal collecting ducts, which leads to excessive urinary water loss and intense thirst.Clinical PresentationIndividuals with diabetes insipidus report persistent thirst and very high urine output. In severe cases, fluid intake can reach up to 20...
Diabetes Insipidus II: Pathophysiology01:22

Diabetes Insipidus II: Pathophysiology
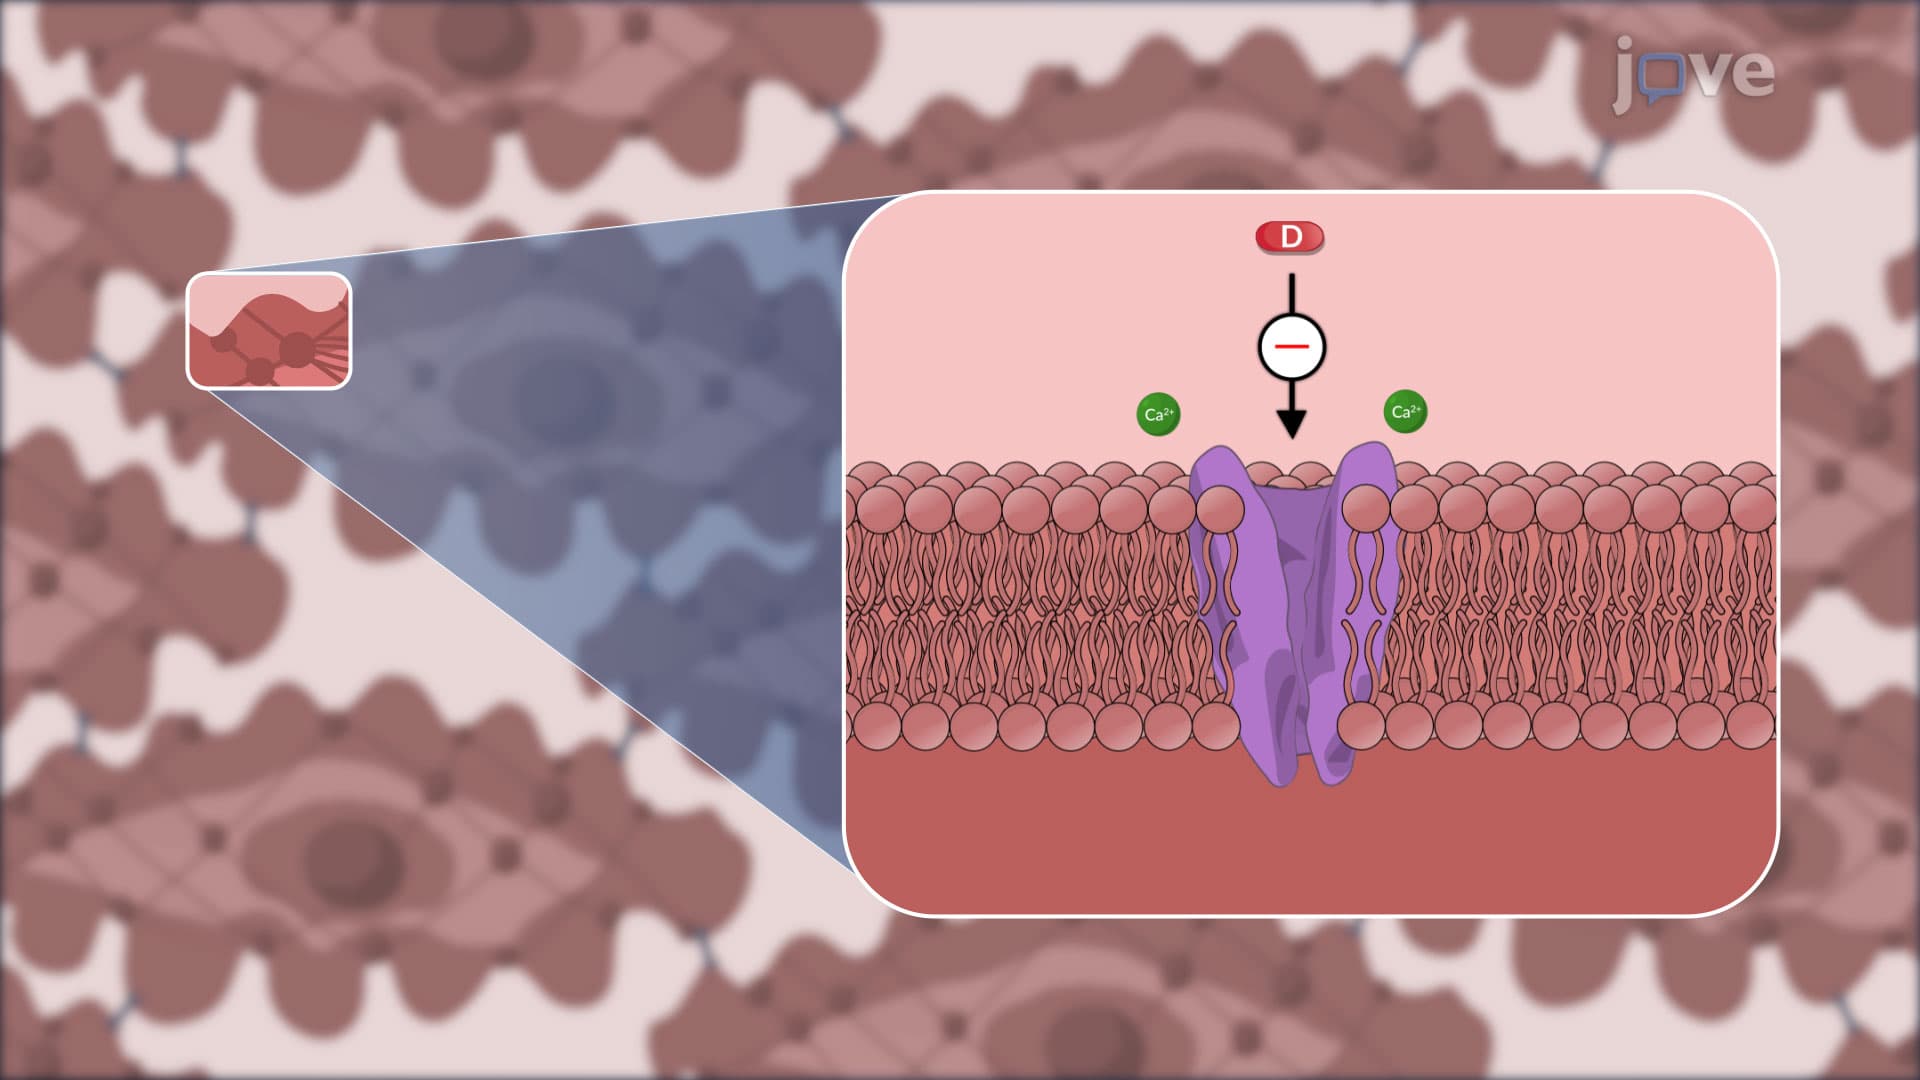
Normally, water balance is maintained through three interconnected mechanisms: the hypothalamic thirst center, the synthesis and release of antidiuretic hormone (ADH, or vasopressin), and the kidneys' responsiveness to this hormone. ADH is synthesized in the hypothalamus, released from the posterior pituitary, and acts on the distal nephron, allowing water reabsorption and concentrated urine production.Diabetes Insipidus and Its TypesIn diabetes insipidus (DI), this regulatory system is...
Antihypertensive Drugs: Thiazide-Class Diuretics01:15

Antihypertensive Drugs: Thiazide-Class Diuretics

Thiazide diuretics are sulfonamide derivatives featuring a benzothiadiazine ring system in their molecular structure. Based on this structure, thiazide diuretics can be categorized into two groups: thiazide-type and thiazide-like diuretics. Thiazide-type diuretics, including hydrochlorothiazide and chlorothiazide, consist of a benzothiadiazine backbone with an attached sulfonamide group. Thiazide-like diuretics, such as chlorthalidone and indapamide, lack the thiazide ring but demonstrate...
Cushing Syndrome I: Introduction01:26

Cushing Syndrome I: Introduction

Cushing syndrome refers to the collection of clinical manifestations that arise when tissues are exposed to excessive amounts of cortisol or cortisol-like medications over an extended period. Cortisol, a glucocorticoid produced by the adrenal cortex, regulates metabolism, immune responses, and the body’s adaptation to stress. When its concentration remains chronically elevated, these physiological pathways become dysregulated, resulting in the characteristic features of the syndrome.Exogenous...
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features of the...
Antihypertensive Drugs: Potassium-Sparing Diuretics01:28

Antihypertensive Drugs: Potassium-Sparing Diuretics

Liddle syndrome is a genetically inherited form of hypertension characterized by the overactivity of epithelial sodium channels in the nephron, the functional unit of the kidney. This heightened activity leads to increased sodium reabsorption and excessive excretion of potassium. To counteract this, potassium-sparing diuretics such as amiloride are used. They function by blocking these sodium channels, thereby reducing the influx of sodium into the epithelial cells and minimizing the loss of...



