Related Experiment Video
Updated: Jun 10, 2026
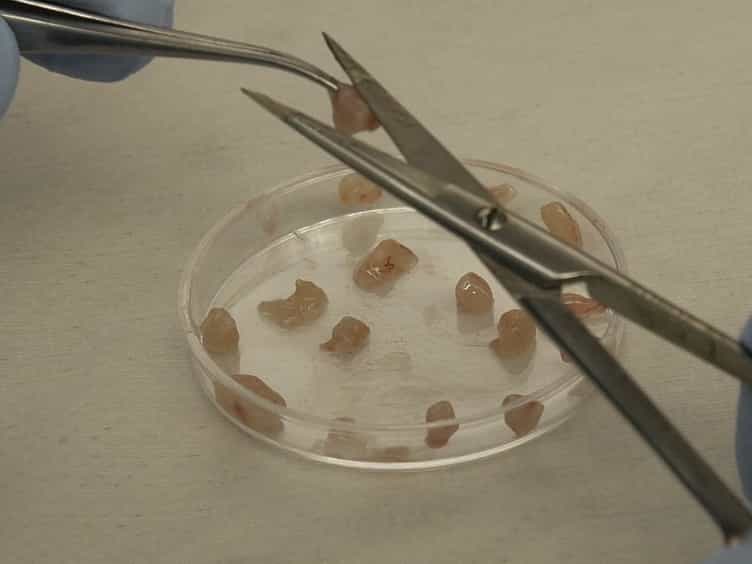
Development and Maintenance of a Preclinical Patient Derived Tumor Xenograft Model for the Investigation of Novel Anti-Cancer Therapies
Published on: September 30, 2016
KRAS mutation testing of colorectal cancer for anti-EGFR therapy: dogmas versus evidence
József Tímár1, Balázs Hegedüs, Erzsébet Rásó
12nd Department of Pathology, Semmelweis University, Budapest, H-1091, Hungary. jtimar@korb2.sote.hu

Abstract:
KRAS mutation testing opened up a new era in routine pathological diagnostics of colorectal cancer similar to the introduction of HER-2 testing in breast cancer with the significant difference that mutational analysis exclusively relies on molecular methodologies. In order to critically analyze the current rational of KRAS mutation testing in colorectal carcinoma we have performed evaluation of related articles available in PubMed/Medline, Society recommendations, anti-EGFR antibody registration documents and NCCN guidelines. KRAS mutation is frequent in colorectal cancer and data suggest a negative prognostic, but neutral predictive significance, with the exception of its strong negative predictive value in case of anti-EGFR antibody therapies. However, there is only scattered information on the significance of rare mutations and copy number changes of KRAS. Furthermore, other mutations in EGFR signaling pathway may also have predictive value such as BRAF, PIK3CA or PTEN. It also seems to be a critical issue whether the K-RAS testing must be done on primary, regional or distant metastatic tissues: data already suggest a small but significant chance of alteration during tumor progression. Technically KRAS mutation testing can be performed by various methods characterized by different sensitivities and specificities, although the clinical significance of these parameters are unknown at the present. The consensus strongly suggests the need for an effective quality control program for these methods. KRAS mutation testing in colorectal cancer raised fundamental biological, clinical and molecular pathological questions as it has become a standard application for predicting sensitivity for anti-EGFR antibody therapies. However, these questions can only be answered by rigorous, dogma-free preclinical and clinical studies.
Insights
KRAS mutation testing is crucial for colorectal cancer, primarily predicting response to anti-EGFR therapies. Further research is needed to clarify rare mutations, copy number changes, and testing across different tumor stages.
Area of Science:
- Oncology
- Molecular Pathology
- Cancer Diagnostics
Background:
- KRAS mutation testing is standard in colorectal cancer (CRC) diagnostics, similar to HER-2 in breast cancer.
- Unlike HER-2, KRAS analysis relies solely on molecular methods.
- Its role extends beyond diagnostics to predicting treatment response.
Purpose of the Study:
- To critically analyze the rationale and current understanding of KRAS mutation testing in colorectal carcinoma.
- To evaluate existing data on KRAS mutations, including rare variants and copy number changes.
- To assess the impact of tumor progression on KRAS status and explore other relevant mutations.
Main Methods:
- Systematic literature review of PubMed/Medline.
- Analysis of Society recommendations.
- Evaluation of anti-EGFR antibody registration documents and NCCN guidelines.
Main Results:
- KRAS mutations are frequent in CRC, generally having negative prognostic but neutral predictive significance.
- A strong negative predictive value exists for anti-EGFR antibody therapies.
- Information on rare KRAS mutations, copy number changes, and testing on metastatic tissues is limited.
- Other EGFR pathway mutations (BRAF, PIK3CA, PTEN) may also hold predictive value.
- Tumor progression can lead to alterations in KRAS status.
- Various testing methods exist with unknown clinical significance of their sensitivities/specificities.
Conclusions:
- KRAS mutation testing is vital for predicting anti-EGFR therapy sensitivity in CRC.
- Standardization and quality control of testing methods are essential.
- Further rigorous studies are required to address biological, clinical, and pathological questions surrounding KRAS testing.

