Stiletto stabbing: penetrating injury to the hypothalamus with hyperacute diabetes insipidus

Eyal Itshayek1, John Moshe Gomori, Sergey Spektor

  • 1Department of Neurosurgery, Hadassah - Hebrew University Medical Center, Jerusalem, Israel. eyal.itshayek@gmail.com

Related Concept Videos

Diabetes Insipidus I: Introduction01:29

Diabetes Insipidus I: Introduction
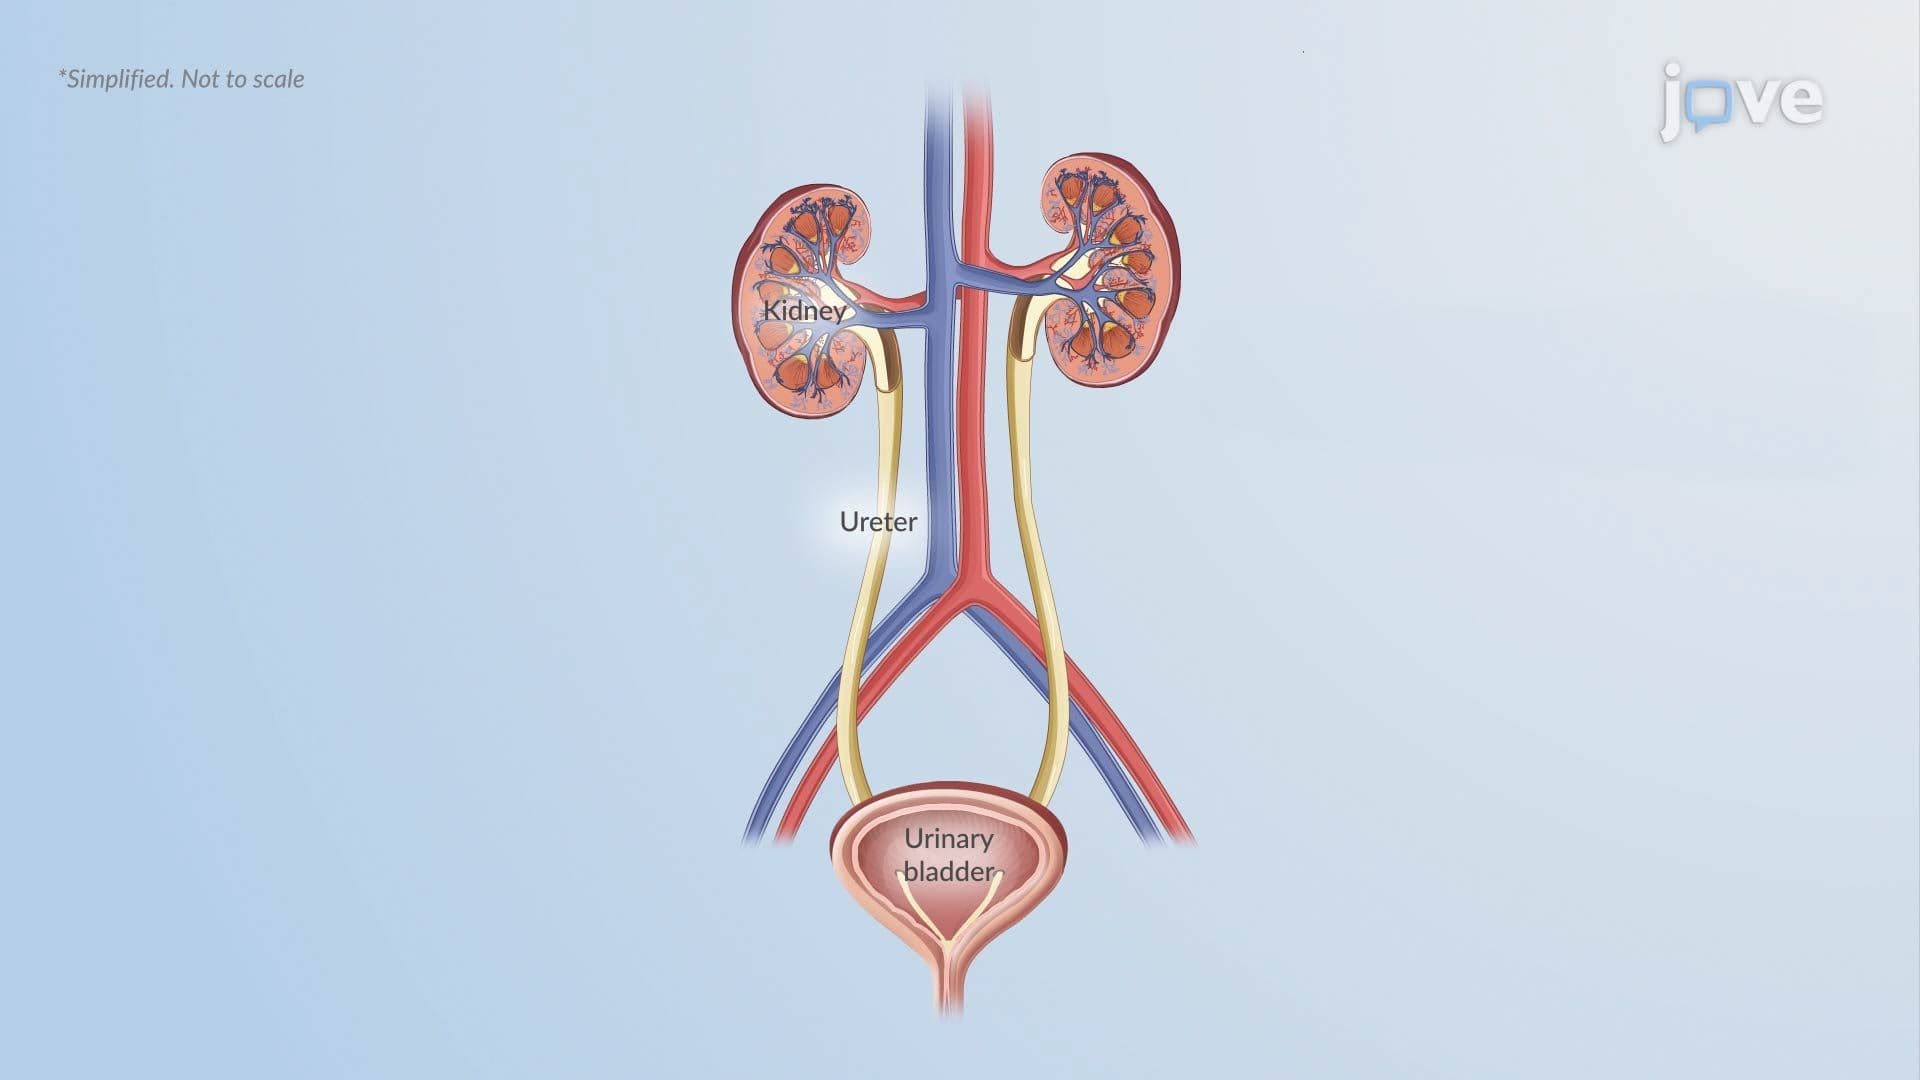
Definition Diabetes insipidus is a disorder marked by the production of large amounts of dilute urine because of impaired vasopressin production, release, or kidney response. The lack of effective vasopressin action limits water reabsorption in the renal collecting ducts, which leads to excessive urinary water loss and intense thirst.Clinical PresentationIndividuals with diabetes insipidus report persistent thirst and very high urine output. In severe cases, fluid intake can reach up to 20...
Diabetes Insipidus II: Pathophysiology01:22

Diabetes Insipidus II: Pathophysiology

Normally, water balance is maintained through three interconnected mechanisms: the hypothalamic thirst center, the synthesis and release of antidiuretic hormone (ADH, or vasopressin), and the kidneys' responsiveness to this hormone. ADH is synthesized in the hypothalamus, released from the posterior pituitary, and acts on the distal nephron, allowing water reabsorption and concentrated urine production.Diabetes Insipidus and Its TypesIn diabetes insipidus (DI), this regulatory system is...
Hyperglycemia01:29

Hyperglycemia

Hyperglycemia is an abnormally high blood glucose level. It is diagnosed by fasting glucose ≥126 mg/dL, 2-hour oral glucose tolerance test (or OGTT) ≥200 mg/dL, random glucose ≥200 mg/dL with symptoms, or HbA1c ≥6.5%. However, HbA1c results may be unreliable in certain conditions, such as anemia or hemoglobinopathies, and the diagnosis should be confirmed unless classic symptoms are present. Postprandial hyperglycemia is typically considered significant when glucose levels exceed 180 mg/dL two...
Type I Diabetes III: Clinical Manifestations01:19

Type I Diabetes III: Clinical Manifestations
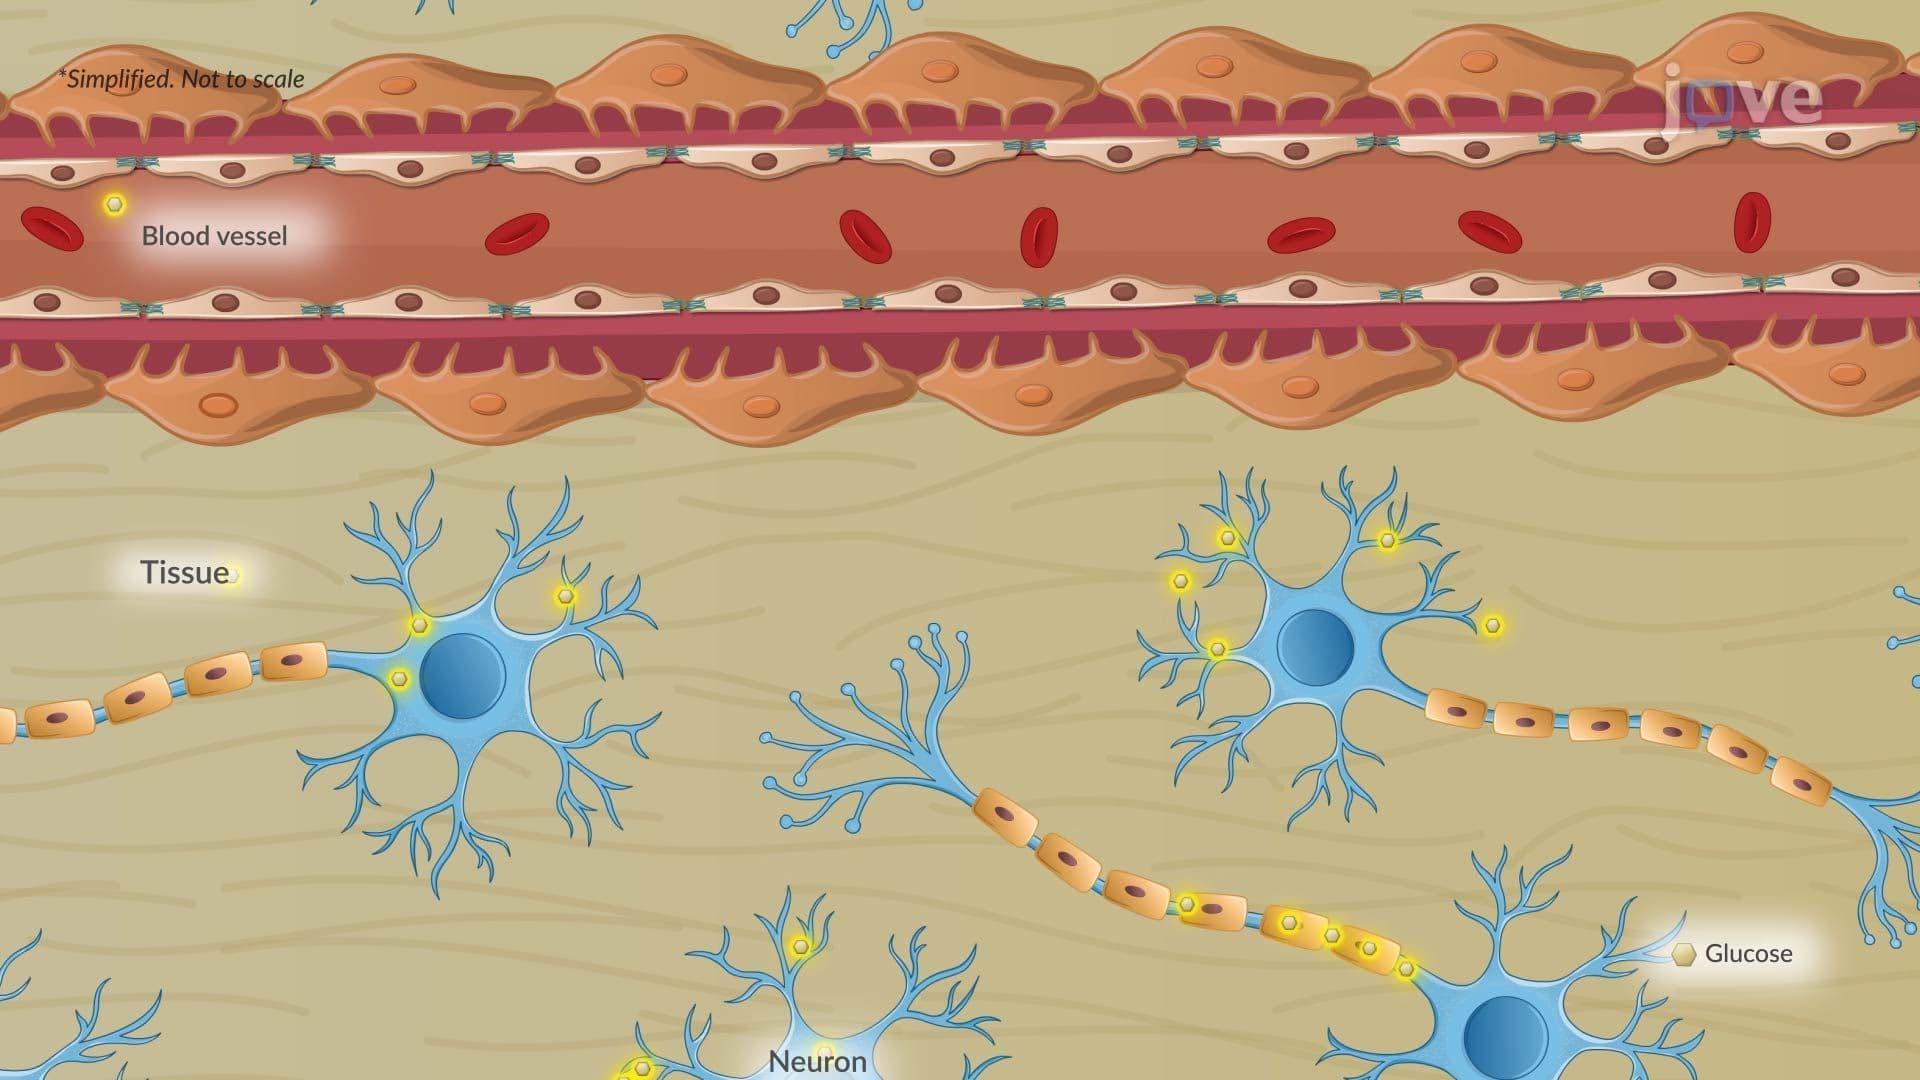
Type 1 diabetes mellitus typically presents with rapid-onset symptoms due to the body’s inability to utilize glucose in the absence of insulin. Since insulin is required for glucose uptake into cells, its deficiency leads to hyperglycemia and cellular energy deprivation, resulting in characteristic clinical features.Polyuria and PolydipsiaOne of the earliest, most prominent symptoms is polyuria (excessive urination). When blood glucose concentrations rise above the renal threshold, the kidneys...
Diabetic Neuropathy01:22

Diabetic Neuropathy

DefinitionDiabetic neuropathy is nerve damage caused by long-standing diabetes mellitus. It results directly from prolonged high blood sugar levels.PathophysiologyThe pathophysiology of diabetic neuropathy involves both metabolic and vascular disturbances triggered by chronic hyperglycemia.Metabolic injury: Elevated glucose levels activate the polyol pathway within nerve cells, leading to the accumulation of sorbitol and fructose. This increases oxidative stress, disrupts normal nerve...
Hyperosmolar Hyperglycemic State01:21

Hyperosmolar Hyperglycemic State

Hyperosmolar Hyperglycemic State, or HHS, is a serious and life-threatening complication of type 2 diabetes mellitus. It is characterized by three main features: severe hyperglycemia, profound dehydration, and elevated serum osmolality, all occurring without significant ketoacidosis.HHS typically develops in older adults or individuals with limited access to fluids. This may result from illness, cognitive impairment, or medications such as diuretics or corticosteroids. These factors reduce...




