Related Experiment Video
Updated: Jun 10, 2026


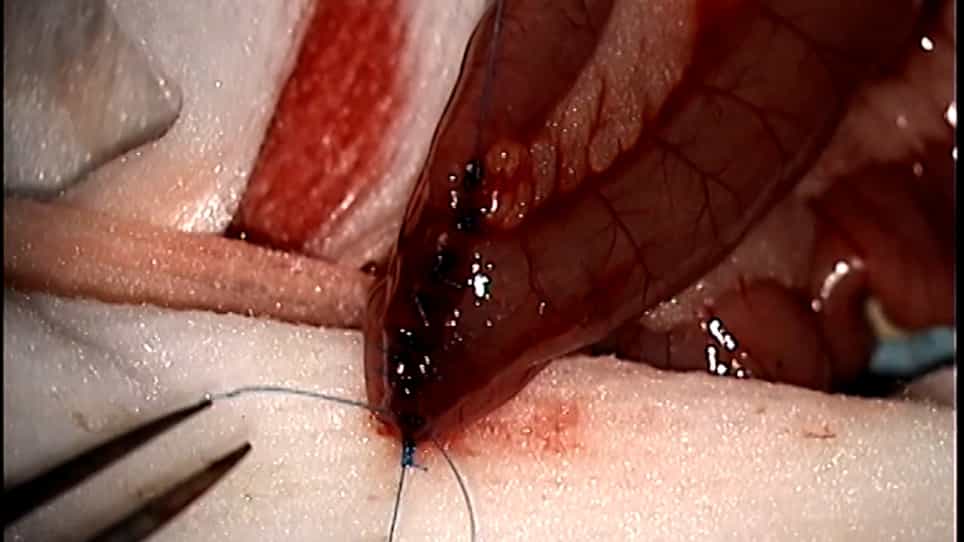
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Early marginal ulcer following Roux-en-Y gastric bypass under proton pump inhibitor treatment: prospective
Arthur Belarmino Garrido1, Marçal Rossi, Sizenando Ernesto Lima
1Instituto Garrido, São Paulo, SP, Brazil. abgarrido@uol.com.br

Context:
Causal factors of gastrojejunal ulcers after Roux-en-Y gastric bypass include peptic acid secretion from the gastric pouch. Esomeprazole is a potent inhibitor of acid secretion.
Objective:
To assess the occurrence of dyspepsia and gastrojejunal ulcers within the first 2 months after Roux-en-Y gastric bypass during the use of esomeprazole.
Methods:
One hundred eighteen morbid obese subjects were submitted to Roux-en-Y gastric bypass. Preoperative upper gastrointestinal tract endoscopy was negative for H. pylori. All subjects received esomeprazole for 60 days after surgery.
Results:
Two weeks after surgery only 13 mild symptoms were reported. After 2 months, 17 also moderate complaints were registered. Endoscopy around the 60th day showed esophagitis in 10 (8.5%), hiatal hernia in 2 (1.7%), foreign body in the anastomotic line in 12 (10.2%) and gastrojejunal ulcers was observed in 9 (7.6%) subjects, 2 of which had a suture material or metallic staple granuloma in the gastrojejunostomy. Ten subjects took nonsteroidal anti-inflammatory drugs at least once during study, but none of them developed ulcer. None of the subjects with ulcer had dyspeptic symptoms.
Conclusion:
The incidence of ulcer in the gastrojejunal anastomosis within the first 2 months following Rouxen-Y gastric bypass under proton pump inhibitors is considerable. It was not related to the use of non-steroidal anti-inflammatory drugs, highlighting the possibility of ischemia and foreign body as causal factors. The ulcers were asymptomatic, and all post-surgical dyspeptic symptoms were moderate in severity.

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:24
Peptic Ulcer Disease II: Pathophysiology