Related Experiment Video
Updated: Jun 9, 2026


Isolation of Human Islets from Partially Pancreatectomized Patients
Published on: July 30, 2011
Outcome of patients with type 1 or 2 autoimmune pancreatitis
Frédérique Maire1, Yann Le Baleur, Vinciane Rebours
1Department of Gastroenterology and Pancreatology, Beaujon Hospital, AP-HP, Diderot-Paris VII University, Clichy, France. frederique.maire@bjn.aphp.fr

Objectives:
Autoimmune pancreatitis (AIP) is better described than before, but there is still no international consensus for definition, diagnosis, and treatment. Our aims were to analyze the short- and long-term outcome of patients with focus on pancreatic endocrine and exocrine functions, to search for predictive factors of relapse and pancreatic insufficiency, and to compare patients with type 1 and type 2 AIP.
Methods:
All consecutive patients followed up for AIP in our center between 1999 and 2008 were included. Two groups were defined: (a) patients with type 1 AIP meeting HISORt (Histology, Imaging, Serology, Other organ involvement, and Response to steroids) criteria; (b) patients with definitive/probable type 2 AIP including those with histologically confirmed idiopathic duct-centric pancreatitis ("definitive") or suggestive imaging, normal serum IgG4, and response to steroids ("probable"). AIP-related events and pancreatic exocrine/endocrine insufficiency were looked for during follow-up. Predictive factors of relapse and pancreatic insufficiency were analyzed.
Results:
A total of 44 patients (22 males), median age 37.5 (19-73) years, were included: 28 patients (64%) with type 1 AIP and 16 patients (36%) with type 2 AIP. First-line treatment consisted of steroids or pancreatic resection in 59 and 27% of the patients, respectively. Median follow-up was 41 (5-130) months. Steroids were effective in all treated patients. Relapse was observed in 12 patients (27%), after a median delay of 6 months (1-70). Four patients received azathioprine because of steroid resistance/dependence. High serum IgG4 level, pain at time of diagnosis, and other organ involvement were associated with relapse (P<0.05). At the end point, pancreatic atrophy was observed in 35% of patients. Exocrine and endocrine insufficiencies were present in 34 and 39% of the patients, respectively. At univariate analysis, no factor was associated with exocrine insufficiency, although female gender (P=0.04), increasing age (P=0.006), and type 1 AIP (P=0.001) were associated with the occurrence of diabetes. Steroid/azathioprine treatment did not prevent pancreatic insufficiency. Type 2 AIP was more frequently associated with inflammatory bowel disease than type 1 AIP (31 and 3%, respectively), but relapse rates were similar in both groups.
Conclusions:
Relapse occurs in 27% of AIP patients and is more frequent in patients with high serum IgG4 levels at the time of diagnosis. Pancreatic atrophy and functional insufficiency occur in more than one-third of the patients within 3 years of diagnosis. The outcome of patients with type 2 AIP, a condition often associated with inflammatory bowel disease, is not different from that of patients with type 1 AIP, except for diabetes.
Related Concept Videos
 01:26
Type I Diabetes II: Pathophysiology
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:21
Chronic Pancreatitis II: Pathophysiology
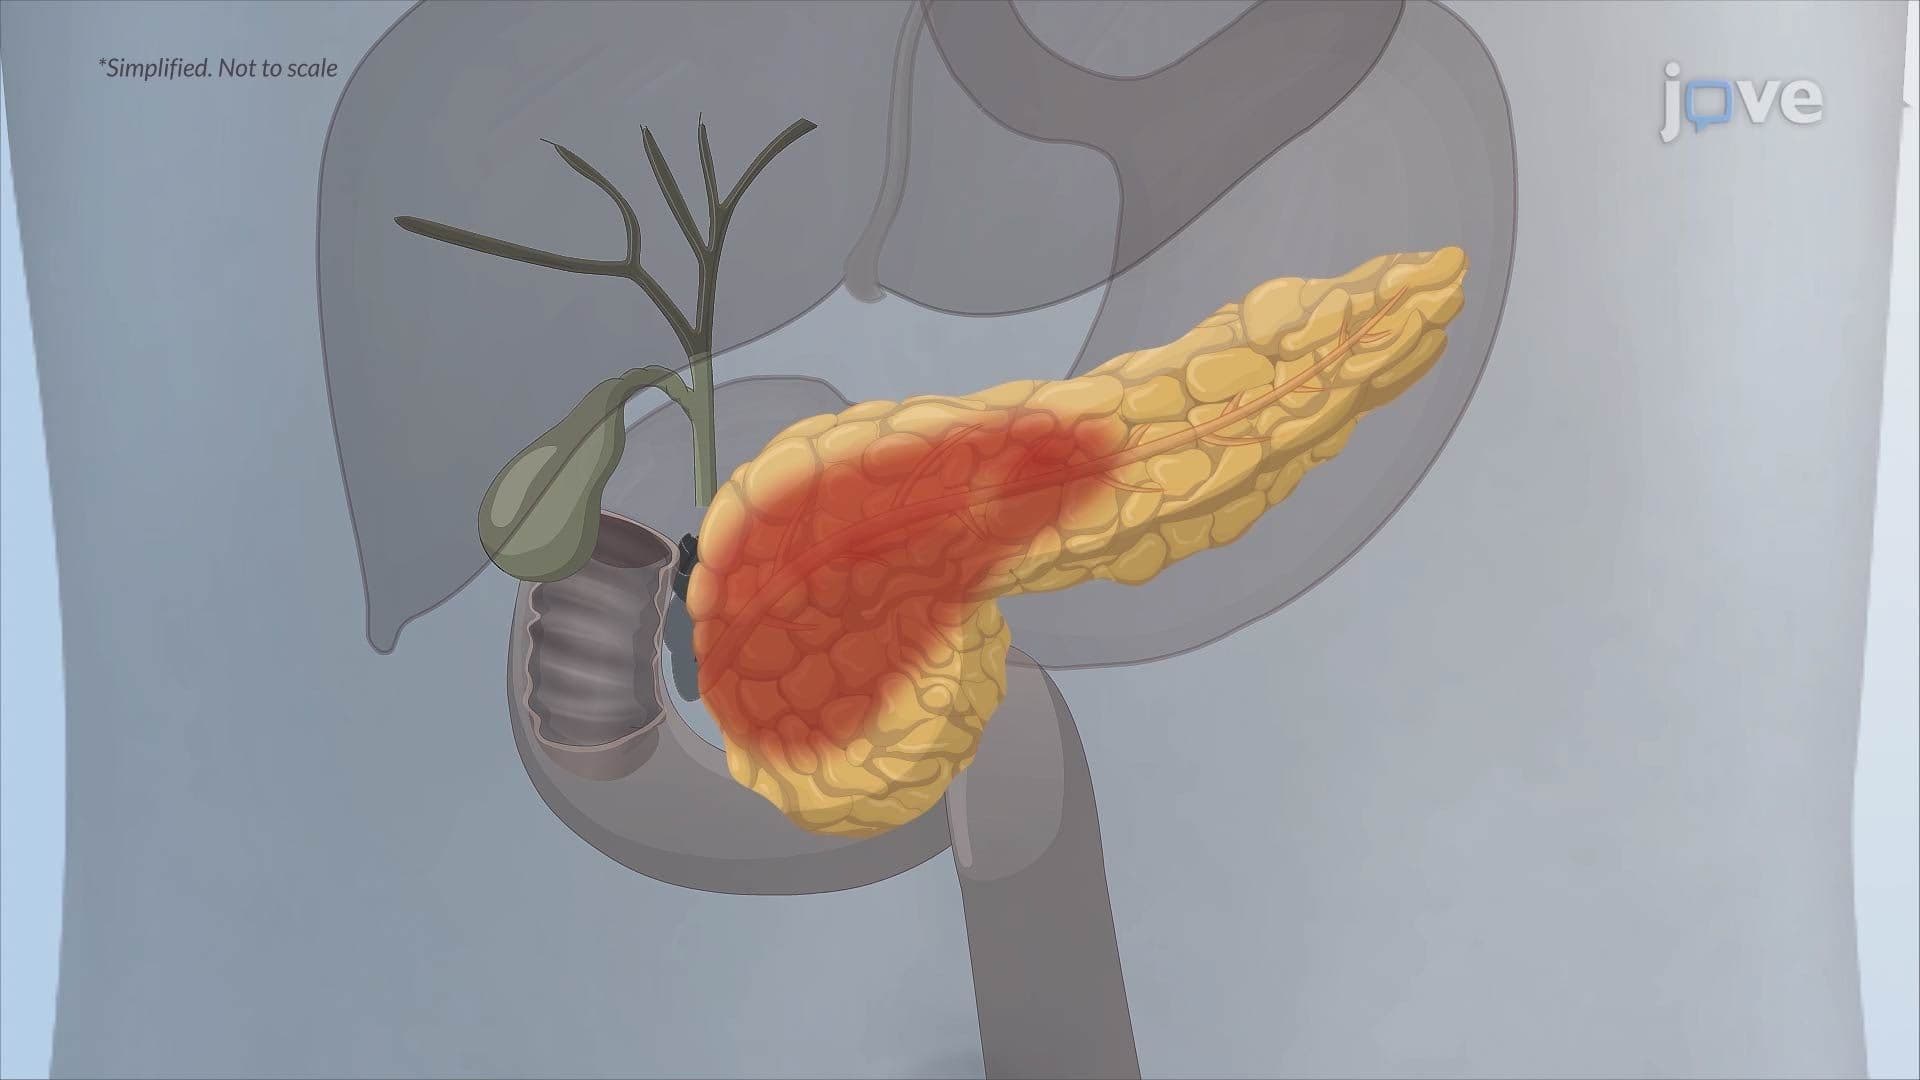 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: