Related Experiment Video
Updated: Jun 9, 2026


Culturing and Measuring Fetal and Newborn Murine Long Bones
Published on: April 26, 2019
Physeal change after tuberculous osteomyelitis of the long bone in children
Hsuan-Kai Kao1, Wen-E Yang, Hsin-Nung Shih
1Department of Orthopedics, Chang Gung Memorial Hospital at Linkou, Chang Gung University College of Medicine, Taoyuan, Taiwan.

Background:
Tuberculous osteomyelitis of the long bone in children is often neglected, and established transphyseal bone lesions are common. The purpose of this study was to evaluate the clinical outcomes of these patients.
Methods:
Between January 1990 and December 2008, 19 patients (10 boys and 9 girls) with sustained tuberculous osteomyelitis of the long bone accompanied by physeal involvement were treated at our institute. The average age was 23.8 months (range, 10-58 months). All patients received surgical treatment and antituberculosis therapy for at least 6 months. The final radiographic and functional results were analyzed.
Results:
All patients were followed up for an average of 61.8 months (range, 14-123 months). The most common site of infection was the distal femur (8 patients, 42.1%), followed by the proximal tibia (5 patients, 26.3%) and the distal tibia (3 patients, 15.8%). Most of the lesions were osteolytic, round to oval in shape, and showed marginal sclerosis. Some lesions were expanding or multiloculated. The periosteal reaction was minimal. Even in cases with extensive surgical curettage through the physis, the growth plate maintained its function and gradually remodeled. Clinical symptoms improved within 4-6 weeks. All bone lesions decreased in size in 3-6 months. Further, physeal bar formation was observed, but the extent was minimal. All transphyseal lesions healed gradually over a period of several years. Good remodeling of skeletal lesions was noted.
Conclusions:
The diagnosis of tuberculous osteomyelitis of the long bone should be considered in every child with unexplained chronic limb pain or swollen limbs. The lesions are usually located in the metaphysis and easily cross the growth plate to the epiphysis. Surgical debridement is beneficial in both diagnosis and treatment. In patients with growth plate involvement, careful surgical debridement is recommended to eradicate infection since the risk of permanent physeal damage is minimal. The physis can heal gradually, and full range of motion of the adjacent joints can be maintained.
Related Concept Videos
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
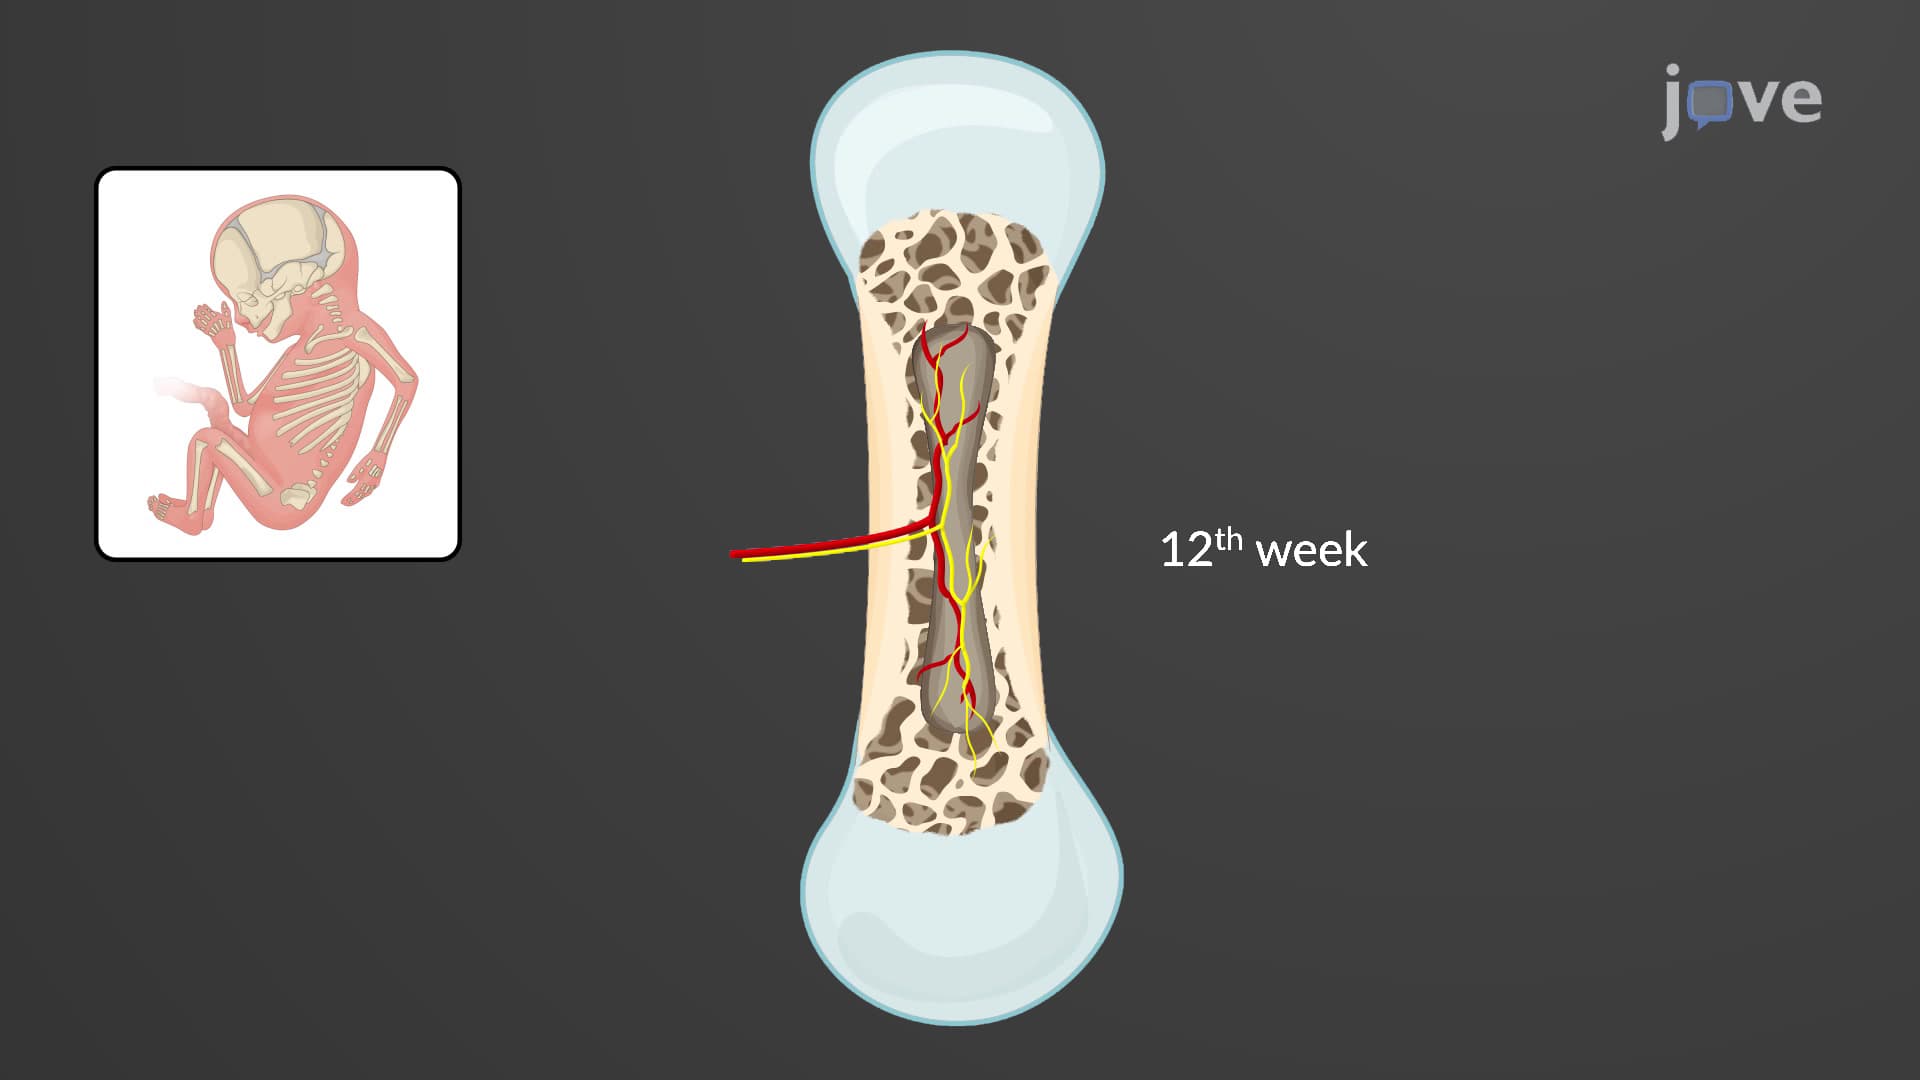
Bone Formation by Endochondral Ossification
 01:17
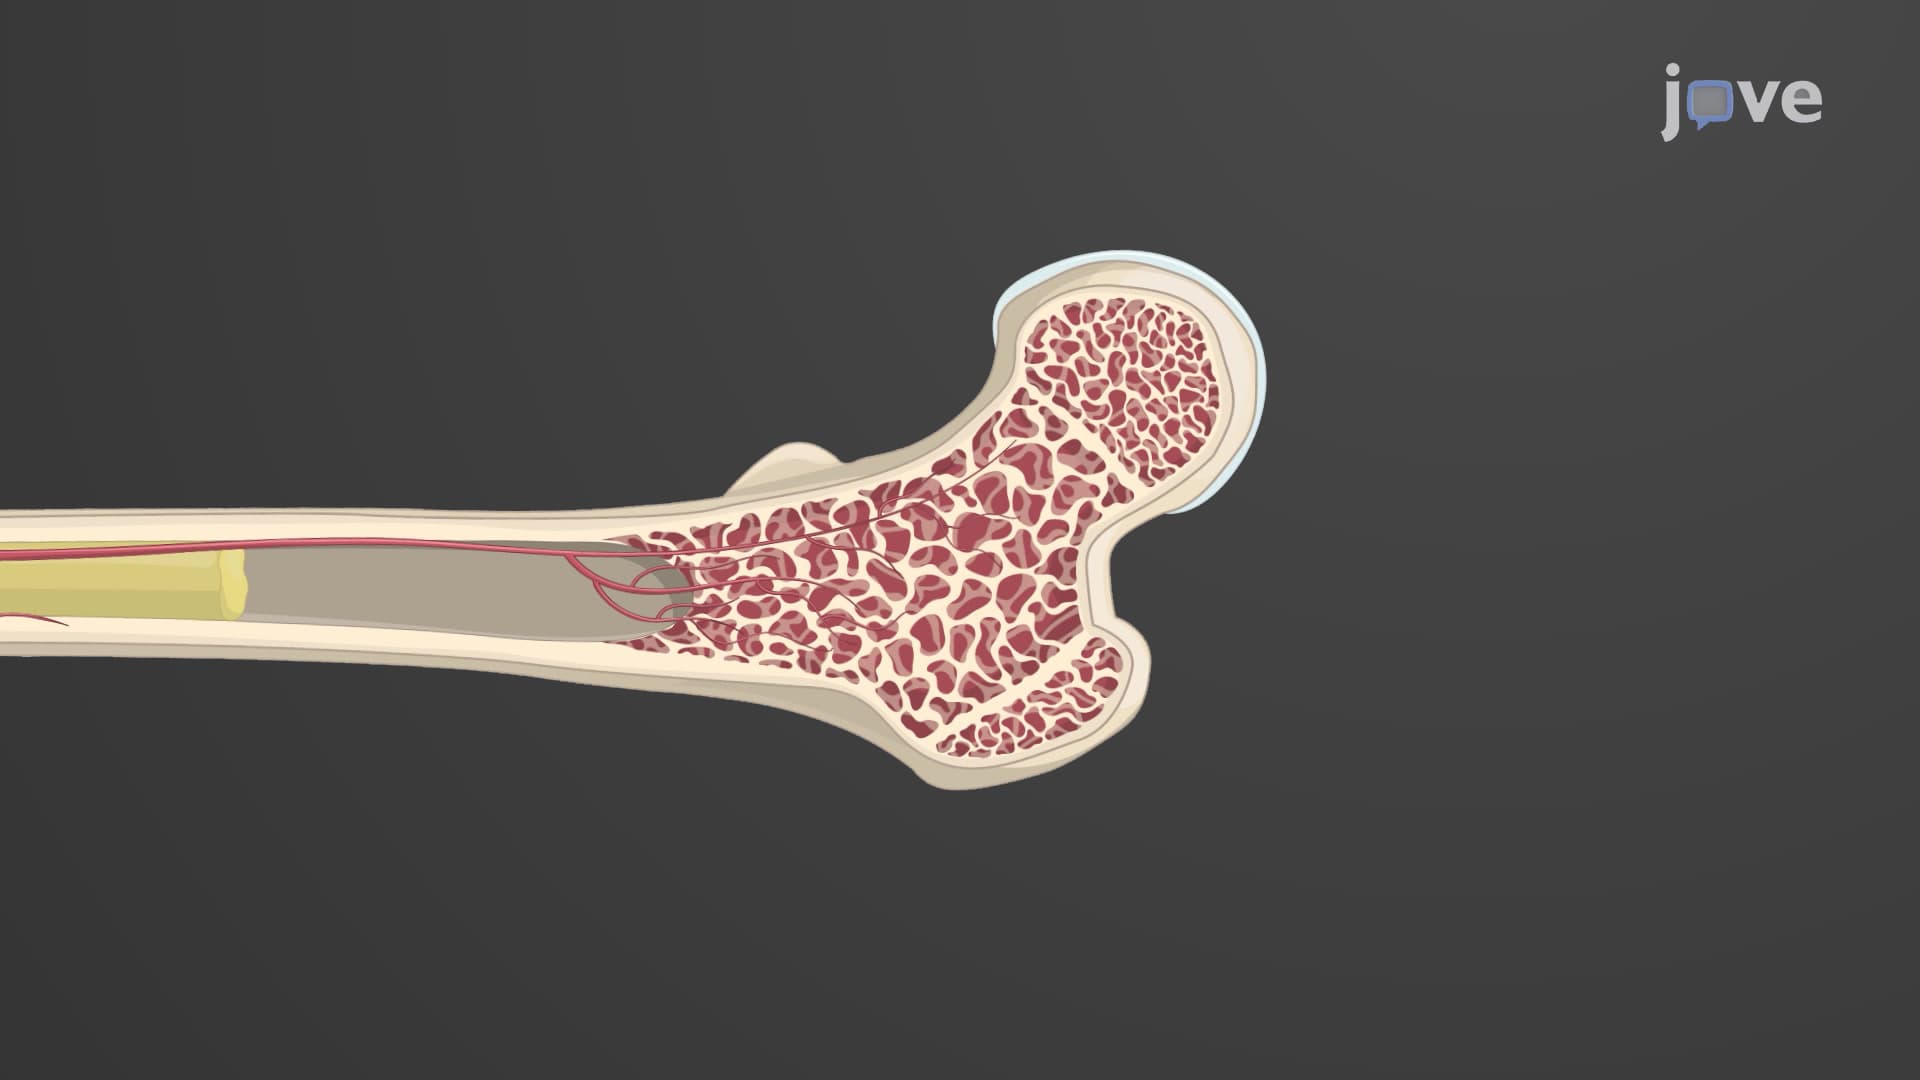
Gross Anatomy of Bone
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in adults, it...
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling