Related Experiment Video
Updated: Jun 9, 2026

Application of Simplified Stent-bridging Pancreaticogastrostomy in Open Pancreaticoduodenectomy
Published on: March 17, 2026
Gastric Outlet Obstruction Palliation: A Novel Stent-Based Solution
Natasha M Rueth1, Rafael S Andrade, Shawn S Groth
1Division of Thoracic and Foregut Surgery, Department of Surgery, University of Minnesota, Minneapolis, Minn., USA.

Abstract:
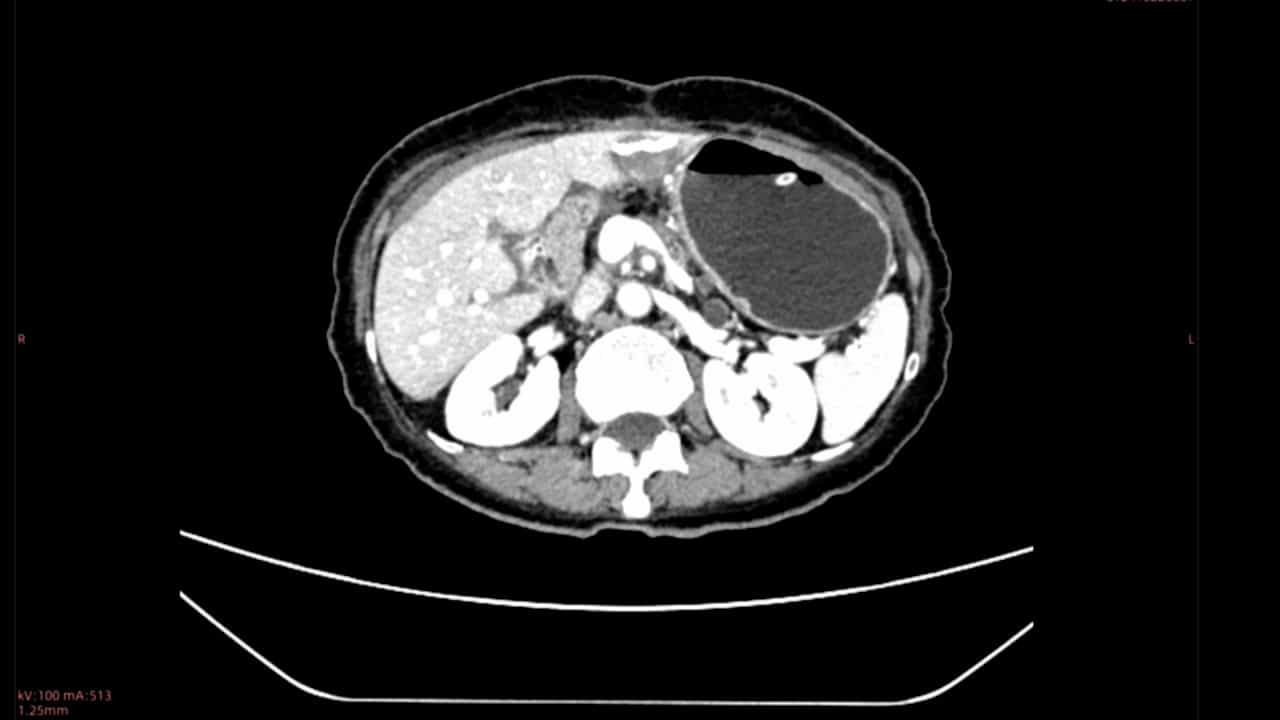
Gastric outlet obstruction (GOO) after esophagectomy is a morbid outcome and significantly hinders quality of life for end-stage esophageal cancer patients. In the pre-stent era, palliation consisted of chemotherapy, radiation, tumor ablation, or stricture dilation. In the current era, palliative stenting has emerged as an additional tool; however, migration and tumor ingrowth are ongoing challenges. To mitigate these challenges, we developed a novel, hybrid, stent-based approach for the palliative management of GOO. We present a patient with esophageal cancer diagnosed with recurrent, metastatic disease 1 year after esophagectomy. She developed dehydration and intractable emesis, which significantly interfered with her quality of life. For palliation, we dilated the stenosis and proceeded with our stent-based solution. Using a combined endoscopic and fluoroscopic approach, we placed a 12-mm silicone salivary bypass tube across the pylorus, where it kinked slightly because of local tumor biology. To bridge this defect and ensure luminal patency, we placed a nitinol tracheobronchial stent through the silicone stent. Clinically, the patient had immediate relief from her pre-operative symptoms and was discharged home on a liquid diet. In conclusion, GOO and malignant dysphagia after esophagectomy are significant challenges for patients with end-stage disease. Palliative stenting is a viable option, but migration and tumor ingrowth are common complications. The hybrid approach presented here provides a unique solution to these potential pitfalls. The flared silicone tube minimized the chance of migration and impaired tumor ingrowth. The nitinol stent aided with patency and overcame the challenges of the soft tube. This novel strategy achieved palliation, describing another endoscopic option in the treatment of malignant GOO.

Related Concept Videos
 01:11
Pyloric Obstruction
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...