Related Experiment Video
Updated: Jun 9, 2026


Hydra, a Computer-Based Platform for Aiding Clinicians in Cardiovascular Analysis and Diagnosis
Published on: September 26, 2018
Aggregate cardiovascular risk is a stronger statistical correlate of clinically evident diabetic peripheral
Mayowa O Owolabi1, Arinola Ipadeola, Jokotade O Adeleye
1Department of Medicine, University College Hospital, Ibadan, Nigeria. mayowaowolabi@yahoo.com

Insights
Cardiovascular risk load, not just HbA1c, significantly predicts diabetic peripheral neuropathy. Managing multiple risk factors is crucial for preventing nerve damage in diabetes patients.
Area of Science:
- Endocrinology and Metabolism
- Neurology
- Cardiovascular Medicine
Background:
- Diabetic peripheral neuropathy (DPN) development is influenced by chronic hyperglycemia (HbA1c) and other vascular risk factors.
- The comparative impact of aggregate cardiovascular risk load versus HbA1c on DPN risk remains understudied.
Purpose of the Study:
- To compare the predictive power of aggregate cardiovascular risk load against HbA1c for clinically evident DPN.
Main Methods:
- A cohort of 277 type 2 diabetes outpatients in Nigeria were assessed.
- Neuropathy was diagnosed using the Michigan Neuropathy Screening Instrument (MNSI) criteria.
- HbA1c and aggregate cardiovascular risk load (UKPDS risk engines) were determined for all participants.
Main Results:
- 71.1% of patients exhibited clinically evident DPN.
- HbA1c showed no significant correlation with DPN development (p = .465).
- Aggregate cardiovascular risk load demonstrated a strong correlation with DPN (p = .002) and was a superior predictor in regression analysis.
Conclusions:
- Aggregate cardiovascular risk load is a more potent correlate and predictor of DPN than HbA1c.
- These findings suggest that comprehensive cardiovascular risk management is vital for DPN prevention and monitoring.
Background:
Apart from chronic hyperglycemia measured by hemoglobin A1c (HbA1c), other vascular risk factors contribute to the development of diabetic neuropathy. Even though these factors are synergistic, no study has measured the relative effect of aggregate cardiovascular risk load compared with chronic hyperglycemia alone on the risk of clinically evident diabetic peripheral neuropathy.
Objective:
To compare the effects of aggregate cardiovascular risk load and HbA1c on clinically evident diabetic peripheral neuropathy.
Methods:
We studied 277 consecutive and consenting type 2 diabetic outpatients attending the University College Hospital, Ibadan, Nigeria. Neuropathy was defined operationally as at least 7 positive responses on the Michigan Neuropathy Screening Instrument (MNSI) questionnaire or a score greater than 2.0 on the MNSI examination: thresholds defined by prior validation studies. Patients with nondiabetic causes of neuropathy were excluded. We determined the HbA1c using the ionic exchange chromatographic method and later computed the Diabetes Control Complications Trial referenced values. Aggregate cardiovascular risk load was determined using the UK Prospective Diabetes Study risk engines.
Results:
One hundred ninety-seven (71.1%) patients had clinically evident diabetic peripheral neuropathy. The mean HbA1c value was 6.9%. HbA1c correlated significantly with the average fasting plasma glucose (r = 0.36) but did not correlate significantly with the development of clinically evident diabetic peripheral neuropathy (p = .465, p = -0.045). Aggregate cardiovascular risk load had the strongest significant correlation with clinically evident diabetic peripheral neuropathy (p = .002, p = 0.186, odds ratio, 2.3 for score > 5). In the regression analysis, aggregate cardiovascular risk load was a stronger predictor of clinically evident diabetic peripheral neuropathy than HbA1c.
Conclusions:
Aggregate cardiovascular risk load was a stronger statistical correlate and predictor of clinically evident diabetic peripheral neuropathy than HbA1c. This may have implications for prevention and monitoring of clinically evident diabetic peripheral neuropathy.
Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 01:28
Diabetic Nephropathy
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:22
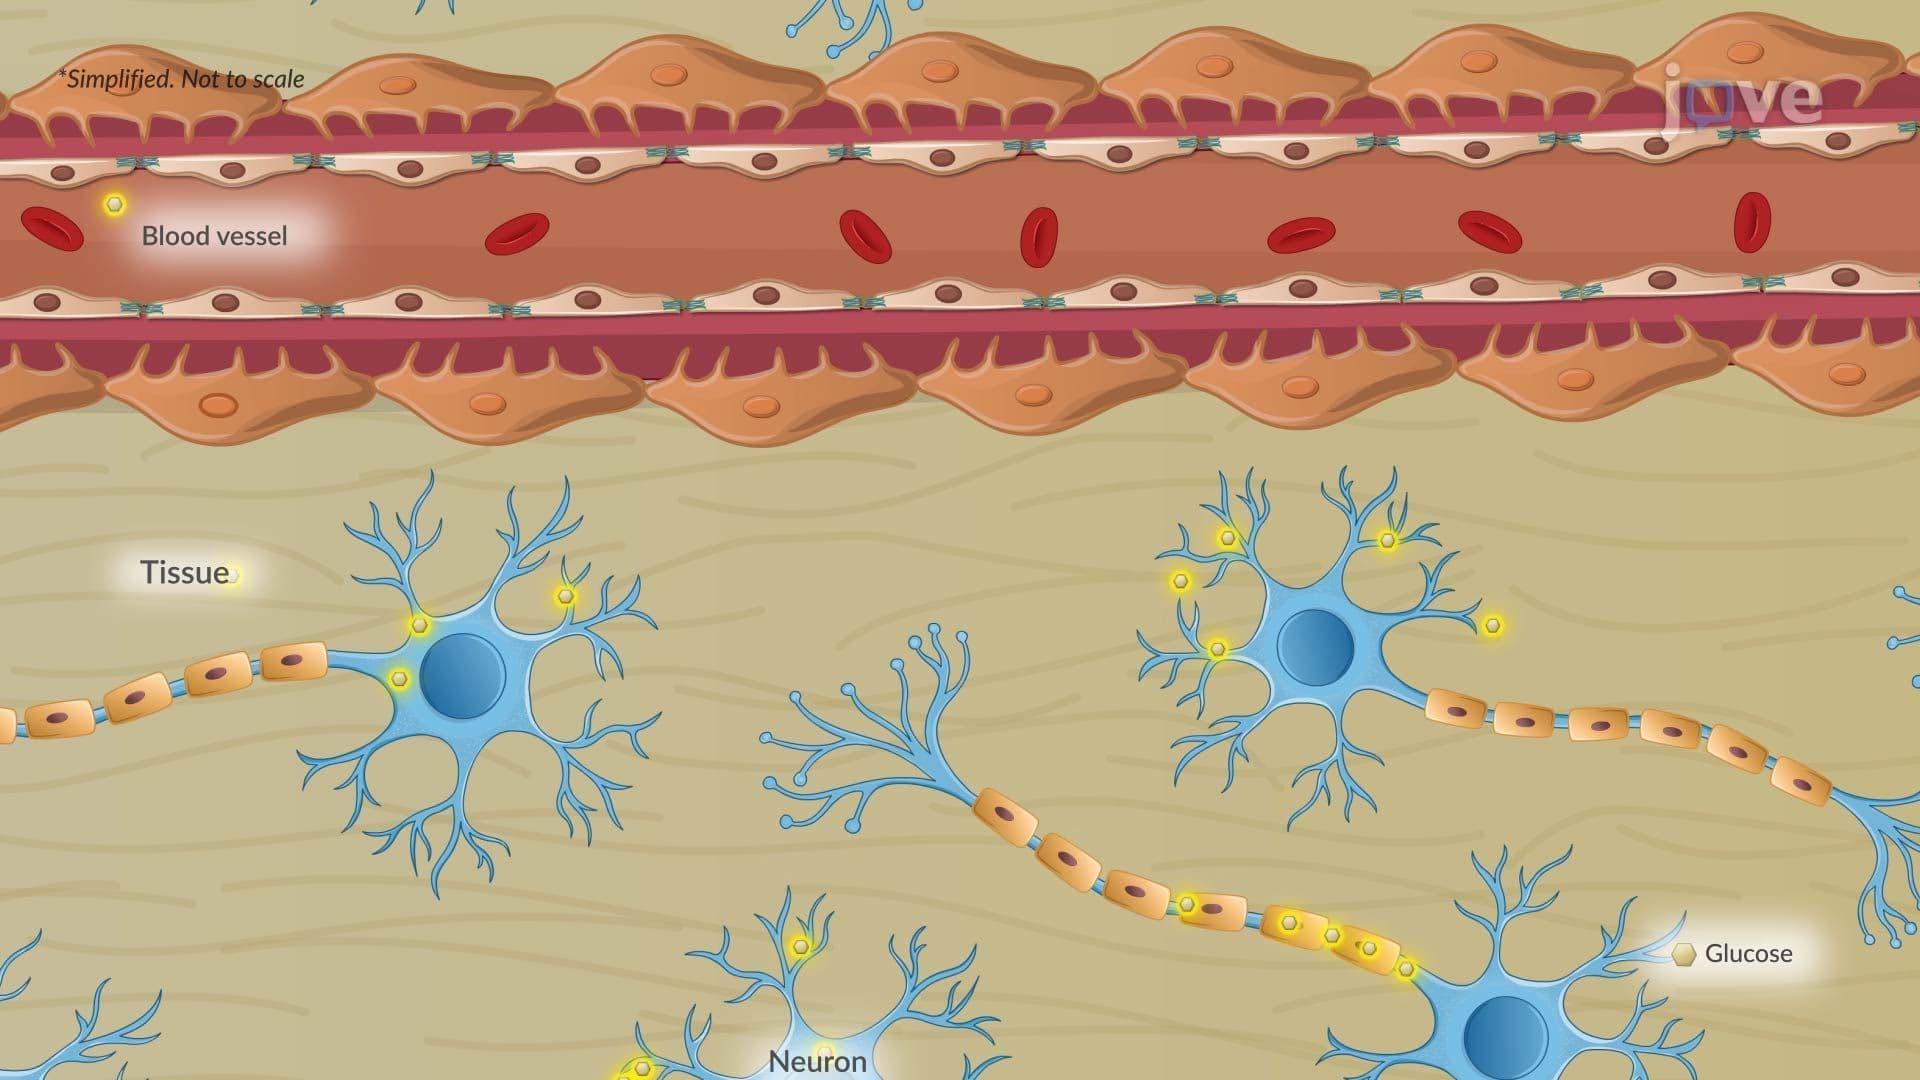
Diabetic Neuropathy
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:27
Diabetic Retinopathy