Related Experiment Video
Updated: Jun 9, 2026

Evaluation of the Cognitive Performance of Hypertensive Patients with Silent Cerebrovascular Lesions
Published on: April 23, 2021
Cerebral atrophy, apolipoprotein E varepsilon4, and rate of decline in everyday function among patients with amnestic
Ozioma C Okonkwo1, Michael L Alosco, Beth A Jerskey
1Department of Neurology, Johns Hopkins University School of Medicine, Baltimore, MD, USA. ozioma@jhmi.edu

Background:
Patients with amnestic mild cognitive impairment (MCI) demonstrate decline in everyday function. In this study, we investigated whether whole brain atrophy and apolipoprotein E (APOE) genotype are associated with the rate of functional decline in MCI.
Methods:
Participants were 164 healthy controls, 258 MCI patients, and 103 patients with mild Alzheimer's disease (AD), enrolled in the Alzheimer's Disease Neuroimaging Initiative. They underwent brain MRI scans, APOE genotyping, and completed up to six biannual Functional Activities Questionnaire (FAQ) assessments. Random effects regressions were used to examine trajectories of decline in FAQ across diagnostic groups, and to test the effects of ventricle-to-brain ratio (VBR) and APOE genotype on FAQ decline among MCI patients.
Results:
Rate of decline in FAQ among MCI patients was intermediate between that of controls and mild AD patients. Patients with MCI who converted to mild AD declined faster than those who remained stable. Among MCI patients, increased VBR and possession of any APOE varepsilon4 allele were associated with faster rate of decline in FAQ. In addition, there was a significant VBR by APOE varepsilon4 interaction such that patients who were APOE varepsilon4 positive and had increased atrophy experienced the fastest decline in FAQ.
Conclusions:
Functional decline occurs in MCI, particularly among patients who progress to mild AD. Brain atrophy and APOE varepsilon4 positivity are associated with such declines, and patients who have elevated brain atrophy and are APOE varepsilon4 positive are at greatest risk of functional degradation. These findings highlight the value of genetic and volumetric MRI information as predictors of functional decline, and thus disease progression, in MCI.
Insights
Mild cognitive impairment (MCI) patients show functional decline, especially if progressing to Alzheimer's disease (AD). Brain atrophy and APOE4 gene presence accelerate this decline, with both factors posing the greatest risk.
Area of Science:
- Neuroscience
- Gerontology
- Medical Imaging
Background:
- Amnestic mild cognitive impairment (MCI) is characterized by declining everyday function.
- Investigating predictors of functional decline in MCI is crucial for understanding disease progression.
Purpose of the Study:
- To determine if whole brain atrophy and apolipoprotein E (APOE) genotype predict the rate of functional decline in MCI patients.
- To compare functional decline trajectories across healthy controls, MCI, and mild Alzheimer's disease (AD) groups.
Main Methods:
- Utilized data from the Alzheimer's Disease Neuroimaging Initiative (ADNI) including 164 controls, 258 MCI, and 103 mild AD patients.
- Assessed functional decline using the Functional Activities Questionnaire (FAQ) over biannual assessments.
- Employed random effects regressions to analyze the impact of ventricle-to-brain ratio (VBR) and APOE genotype on FAQ decline in MCI.
Main Results:
- MCI patients exhibited an intermediate rate of functional decline between controls and mild AD.
- MCI patients who converted to mild AD showed a faster decline in FAQ scores.
- Increased VBR and the presence of an APOE varepsilon4 allele were independently associated with faster FAQ decline in MCI.
- A significant interaction showed that MCI patients with both increased VBR and APOE varepsilon4 positivity experienced the most rapid functional decline.
Conclusions:
- Functional decline is evident in MCI, particularly in those progressing to mild AD.
- Brain atrophy (VBR) and APOE varepsilon4 positivity are significant predictors of accelerated functional decline in MCI.
- Combined elevated VBR and APOE varepsilon4 positivity identify MCI patients at highest risk for functional degradation, highlighting the utility of MRI and genetic markers for predicting disease progression.
Related Concept Videos
 01:29
Alzheimer Disease l: Introduction
 01:26
Alzheimer's Disease: Overview
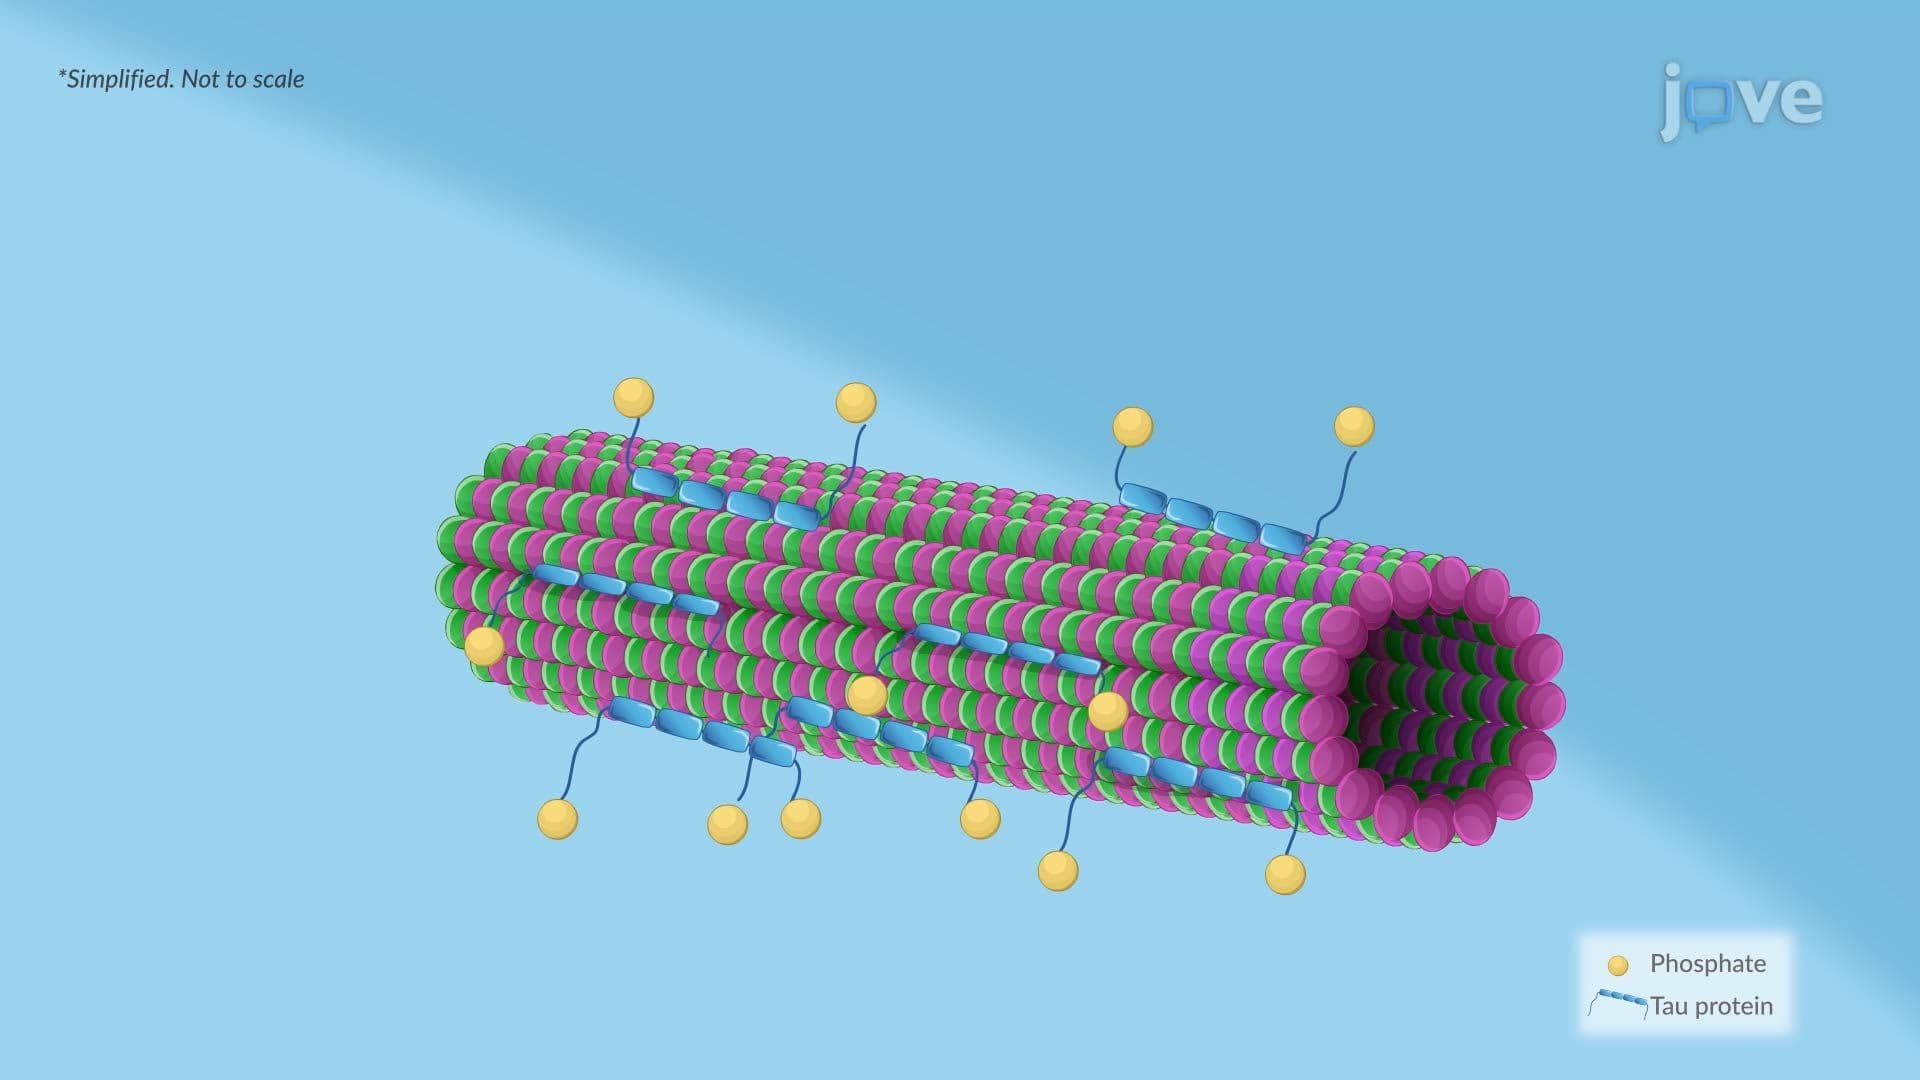
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:23
Alzheimer Disease ll: Pathophysiology
 01:22
Dementia l: Introduction
 01:22
Alzheimer's Disease: Treatment
 01:29
Hepatic Encephalopathy