Related Experiment Video
Updated: Jun 9, 2026
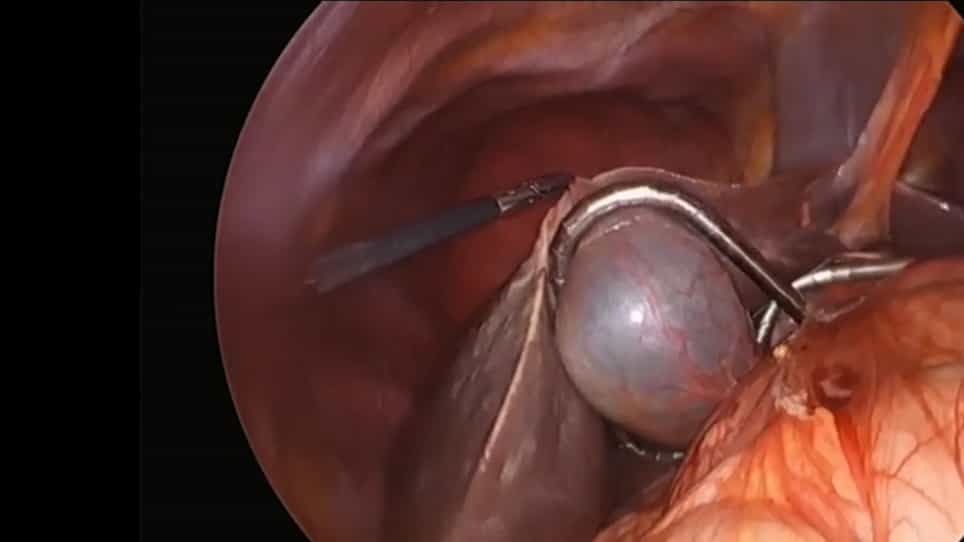

Technical Detail for Robot Assisted Pancreaticoduodenectomy
Published on: September 28, 2019
The inconsistent nature of symptomatic pancreatico-jejunostomy anastomotic strictures
Aram N Demirjian1, Tara S Kent, Mark P Callery
1Division of General Surgery, Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, MA, USA.

Background:
Pancreatico-jejunostomy strictures (PJS) after pancreatiocoduodenectomy (PD) are poorly understood.
Methods:
Patients treated for PJS were identified from all PDs (n = 357) performed for all indications in our practice (2002 to 2009). Technical aspects of the original operation, as well as the presentation, management and outcomes of the resultant stricture were assessed.
Results:
Seven patients developed a symptomatic PJS for an incidence of 2%. 'Soft' glands and small ducts (
Conclusion:
A symptomatic PJS appears to be independent of original pathological, glandular or technical features but pancreatic fistulae may contribute. Secretin MRCP is diagnostically useful, whereas ERCP has been proven to be therapeutically ineffective. Durable resolution of symptoms after surgical revision is unpredictable.
Related Concept Videos
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:24
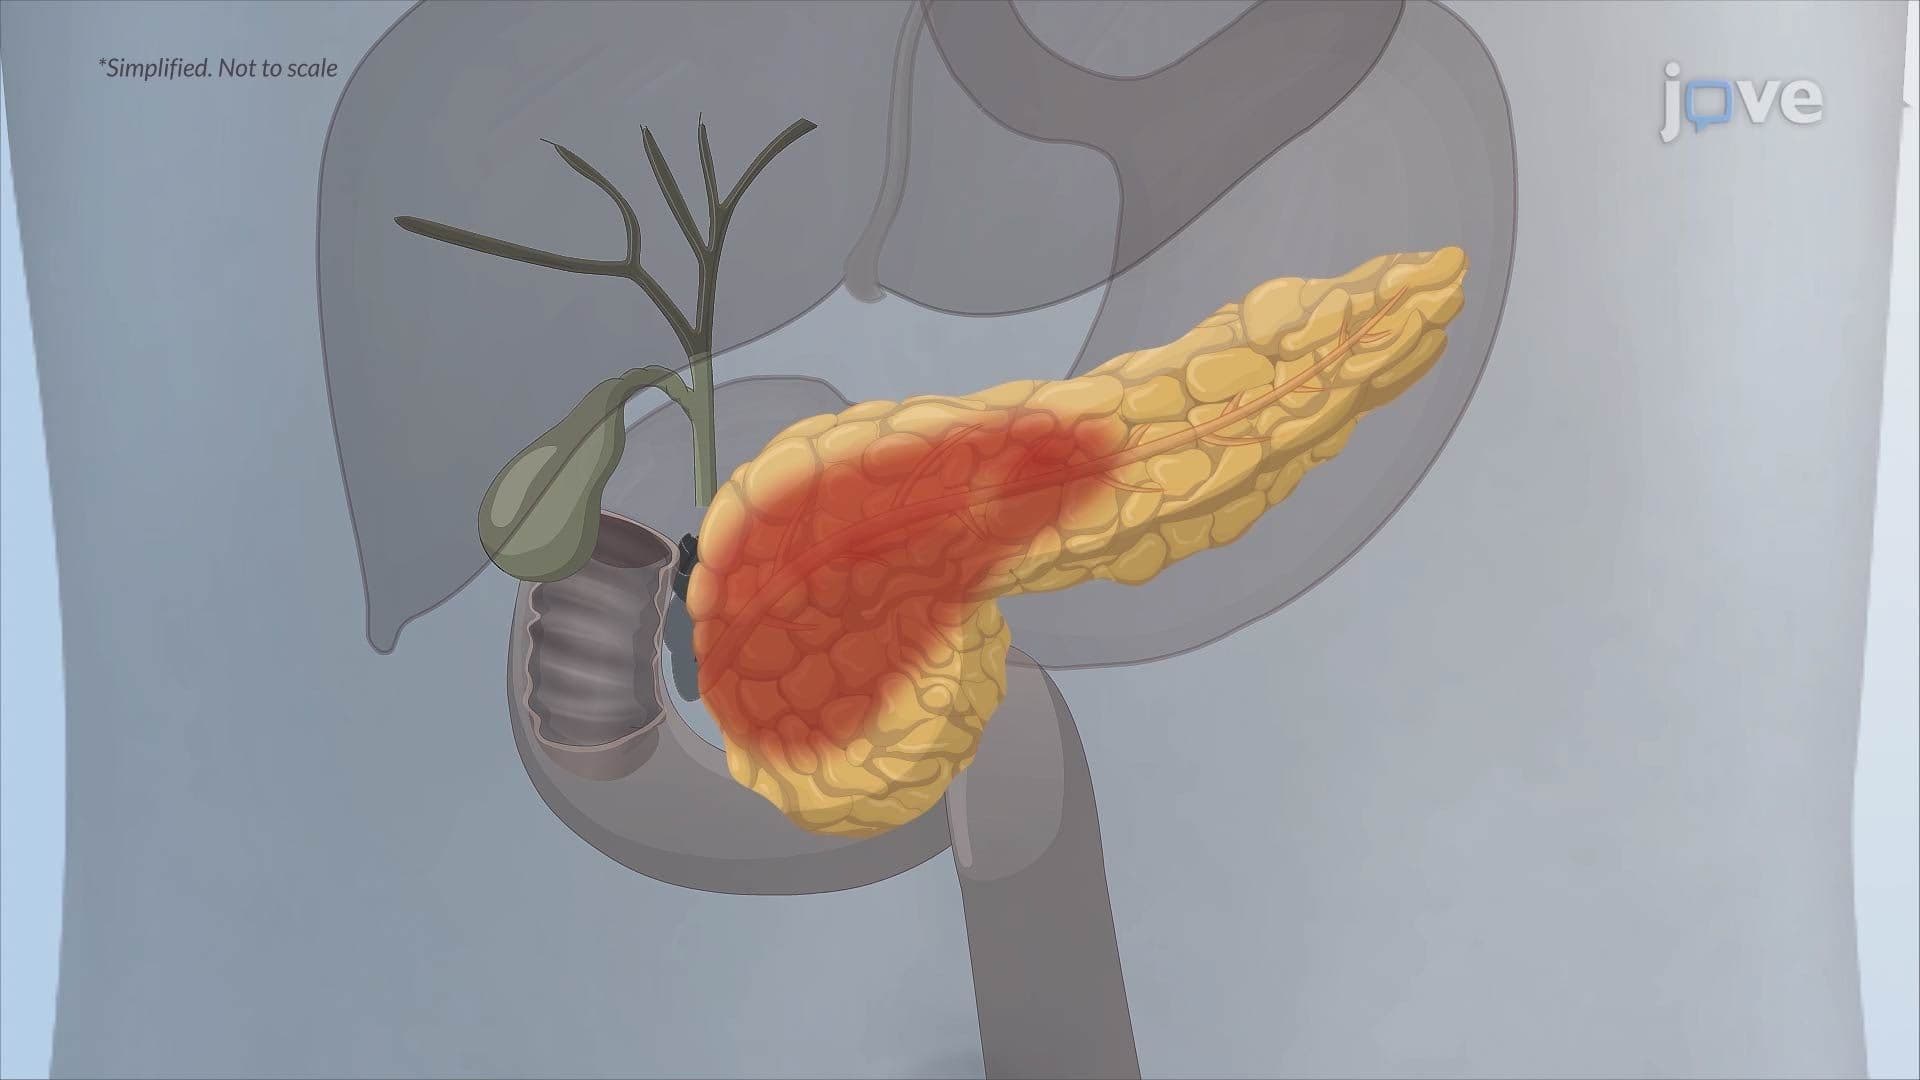
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Chronic Pancreatitis I: Introduction
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:21
Chronic Pancreatitis II: Pathophysiology