Related Experiment Video
Updated: Jun 9, 2026
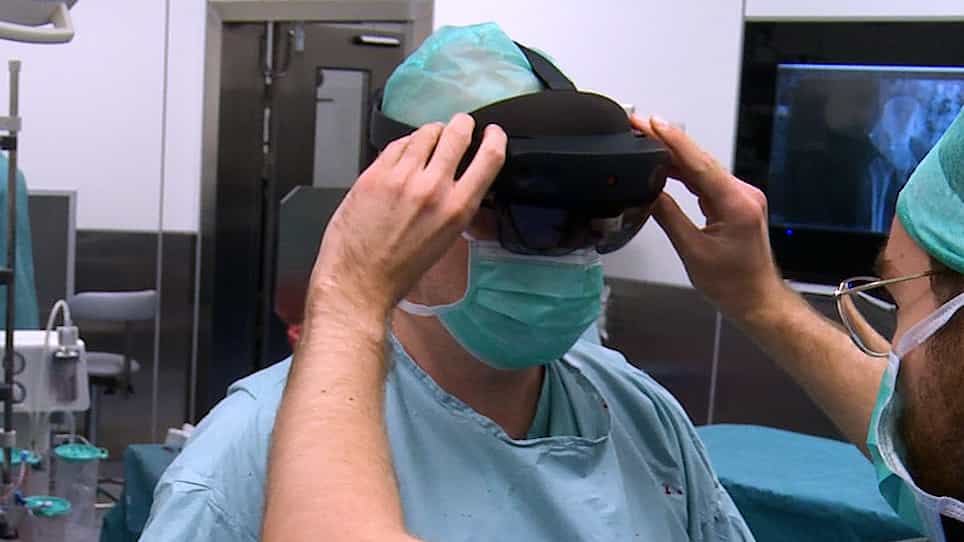

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Quality of life following proximal femoral replacement using a modular system in revision THA
Muhyeddine M Al-Taki1, Bassam A Masri, Clive P Duncan
1Division of Lower Limb Reconstruction and Oncology, Department of Orthopaedics, University of British Columbia, Room 3114, 910 West 10th Avenue, Vancouver, BC V5Z 4E3, Canada.

Background:
Proximal femoral replacement using a segmental modular system is one option for revision THA in the presence of severe bone loss or periprosthetic fracture. While many papers report function in these patients, they do not describe the quality of life.
Questions/Purposes:
We evaluated the quality of life in patients undergoing proximal femoral replacement using a segmental modular system for severe bone loss.
Patients And Methods:
We retrospectively reviewed 63 patients undergoing complex revision THA using a modular replacement system for nonneoplastic conditions between April 1996 and June 2006. Average age was 73 years (range, 23-94 years). Twenty-one patients were lost to followup and six patients died before 2-year minimum followup. The remaining 36 patients were followed for an average of 3.2 years (range, 2-10 years). Study patients were matched by age-decade to a control group of patients undergoing conventional revision THA. At baseline, both groups were comparable with respect to age, comorbidities, and quality-of-life scores.
Results:
At last followup, the modular system group showed improvement in WOMAC function, WOMAC pain, Oxford score, and the SF-12 mental component. Compared to the control group, the modular system group scored lower on WOMAC function and Oxford scores, but there were no differences in any other scores.
Conclusions:
In patients with severely compromised bone stock, a segmental modular replacement system can improve the quality of life. Special attention should be given to the stability of the hip intraoperatively and a constrained acetabular liner should be used when the risk of postoperative dislocation is high.
Level Of Evidence:
Level III, therapeutic study. See the Guidelines for Authors for a complete description of levels of evidence.
