Related Experiment Video
Updated: Jun 9, 2026

A Murine Model of Stent Implantation in the Carotid Artery for the Study of Restenosis
Published on: May 14, 2013
Exercise stress test results in patients with bare metal stents or drug-eluting stents: pathophysiological and
Roberto Nerla1, Antonio Di Monaco, Gregory A Sgueglia
1Department of Cardiovascular Medicine, Catholic University of Sacred Heart.

Insights
Drug-eluting stents (DES) are linked to more positive exercise stress tests (EST) post-percutaneous coronary intervention (PCI) compared to bare metal stents (BMS). EST can predict clinical outcomes in stented coronary artery disease patients.
Area of Science:
- Cardiology
- Interventional Cardiology
- Clinical Research
Background:
- Drug-eluting stents (DES) reduce restenosis after percutaneous coronary intervention (PCI) but may increase coronary endothelial dysfunction compared to bare metal stents (BMS).
- Limited data exist on the prognostic value of exercise stress testing (EST) in PCI patients treated with DES.
Purpose of the Study:
- To evaluate the prognostic value of exercise stress test (EST) in patients undergoing percutaneous coronary intervention (PCI) with either drug-eluting stents (DES) or bare metal stents (BMS).
- To compare the rates of positive EST between DES and BMS groups and correlate EST results with clinical outcomes.
Main Methods:
- A study of 160 patients with coronary artery disease (CAD) who received either BMS (n=86) or DES (n=74) for PCI.
- Exercise stress test (EST) performed one month post-PCI.
- Multivariate Cox-regression analysis to identify predictors of acute myocardial infarction (AMI) and target vessel revascularization (TVR).
Main Results:
- Patients receiving DES showed a significantly higher rate of positive EST (49%) compared to BMS patients (32%; P=0.03).
- At 18-month follow-up, DES demonstrated a trend towards lower target vessel revascularization (TVR) (HR 0.37) but a trend towards higher acute myocardial infarction (AMI) (HR 3.33).
- Time to 1 mm ST depression and low-workload ischemia on EST were independent predictors of both AMI and TVR.
Conclusions:
- DES implantation is associated with a higher incidence of positive EST one month post-PCI, potentially due to increased endothelial dysfunction.
- Exercise stress testing (EST) appears valuable for predicting clinical outcomes in patients with coronary stents, including those treated with DES.
Background:
Drug-eluting stents (DES) have reduced restenosis following percutaneous coronary intervention (PCI), but they seem to be associated with increased coronary endothelial dysfunction compared to bare metal stents (BMS). No data are available about the prognostic value of exercise stress test (EST) in PCI patients in the DES era.
Methods And Results:
The 160 patients with coronary artery disease (CAD) who underwent PCI with either BMS (n=86) or DES (n=74) were studied. EST was performed 1 month after PCI. DES patients had a higher rate of positive EST compared to BMS patients (49% vs 32%; P=0.03). At a median follow-up of 18 months DES showed a lower rate of target vessel revascularization (TVR) (hazard ratio (HR) 0.37, P=0.07), but a higher rate of acute myocardial infarction (AMI) (HR 3.33, P=0.08). At multivariate Cox-regression time to 1 mm ST and low-workload ischemia were independent predictors of AMI (HR 0.96, P=0.03; and HR 6.24, P=0.009, respectively), as well as of TVR (HR 0.96, P=0.007; and HR 6.43, P=0.001, respectively).
Conclusions:
DES implantation is associated with a higher rate of positive EST, compared to BMS, 1 month after PCI, likely due to a higher prevalence of endothelial dysfunction. EST seems to be helpful in predicting clinical outcome in patients with coronary stent implantation.
Related Concept Videos
 01:26
Exercise Stress Test
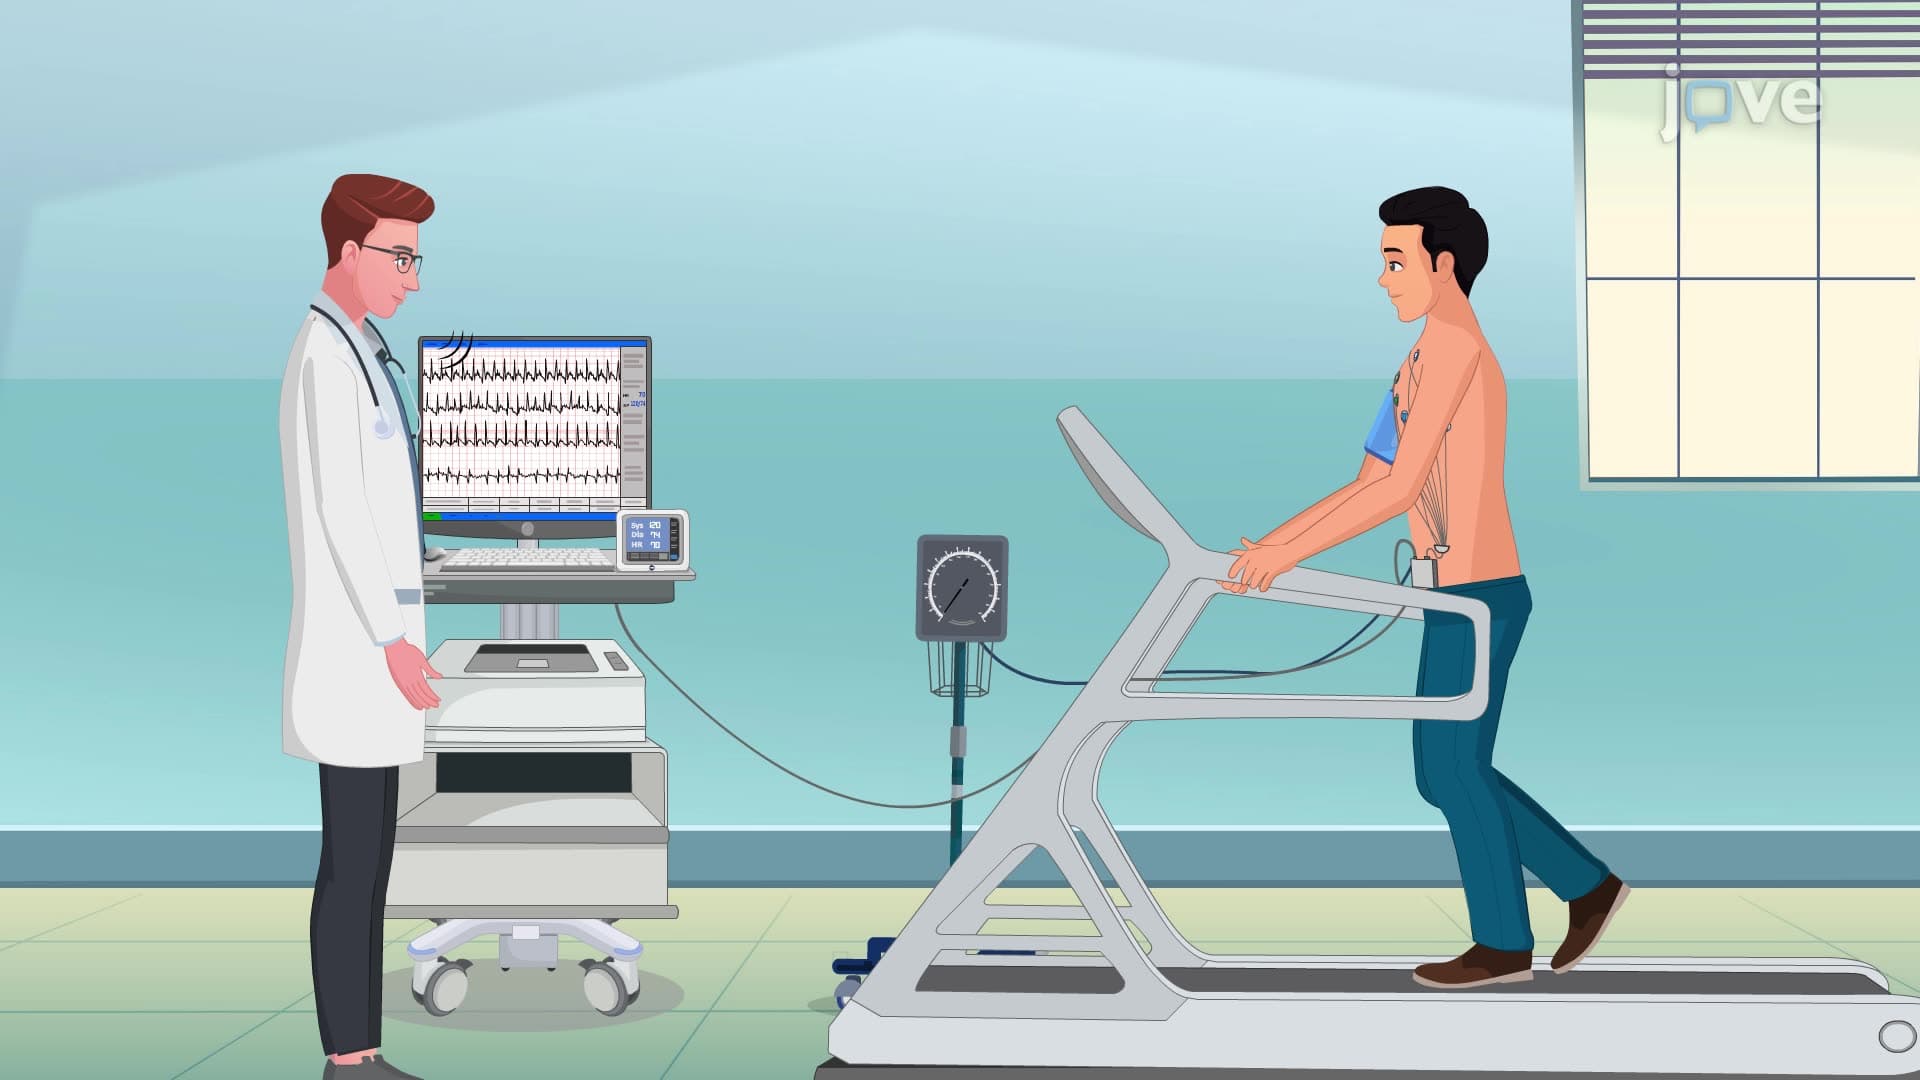
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:29
Angina III: Clinical Manifestations and Assessment
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome I: Introduction
 01:27
Coronary Artery Disease V: Interprofessional Care