Related Experiment Video
Updated: Jun 8, 2026

Biochemical Measurement of Neonatal Hypoxia
Published on: August 24, 2011
Serum prohepcidin concentrations at birth and 1 month after birth in premature infants
Junko Kitajima1, Shouichi Ohga, Tadamune Kinjo
1Department of Pediatrics, Graduate School of Medical Sciences, Kyushu University, Fukuoka, Japan.

Insights
Premature newborns have lower serum prohepcidin at birth, indicating immature iron regulation. Postnatal increases suggest adaptation of iron homeostasis in preterm infants.
Area of Science:
- Neonatal Medicine
- Pediatric Hematology
- Iron Metabolism
Background:
- Premature newborns exhibit vulnerability to iron imbalances.
- Iron homeostasis during the perinatal period requires further clarification.
- Understanding iron metabolism in preterm infants is crucial.
Purpose of the Study:
- To investigate serum prohepcidin concentrations in preterm infants.
- To analyze the association between prohepcidin levels and iron parameters.
- To clarify iron metabolism in premature neonates.
Main Methods:
- Enrolled 71 infants (61 preterm, 10 term) without underlying diseases.
- Measured serum prohepcidin concentrations at birth and 1 month postnatally.
- Utilized enzyme-linked immunosorbent assay for prohepcidin determination.
Main Results:
- Prohepcidin levels at birth correlated positively with gestational age and birth weight.
- Preterm infants had lower birth prohepcidin levels than term infants, with a subsequent increase.
- Prohepcidin levels at birth correlated with red cell counts, iron binding capacity, protein, albumin, and serum iron, but not ferritin.
- Lower birth prohepcidin was associated with pregnancy-induced hypertension and premature rupture of membranes.
Conclusions:
- Prohepcidin production is physiologically low at birth in preterm infants, influenced by gestational age.
- In utero stress may affect prohepcidin levels.
- Postnatal increases in prohepcidin may indicate maturation and adaptation of iron homeostasis.
Background:
Premature newborns are vulnerable to iron imbalance, although the iron homeostasis during the perinatal period remains unclear. To clarify the iron metabolism of premature infants, we measured serum prohepcidin concentrations of preterm infants, and analyzed the association with iron parameters.
Methods:
Seventy-one (61 preterm and 10 term) infants were enrolled for the study, that had no underlying diseases including asphyxia, bleedings, infection, and anomalies. Serum concentrations of prohepcidin at birth and 1 month after birth were determined by enzyme-linked immunosorbent assay.
Results:
Prohepcidin levels at birth but not 1 month postnatal age positively correlated with gestational age (correlation coefficient [CC]:0.334, P = 0.005) and birth weight (CC: 0.367, P = 0.002). The levels at birth of preterm infants (median: 29.93 ng/ml, range: 4.0-110.6) were lower than those of full-term infants, and increased thereafter. On the other hand, the levels in small-for-gestational age infants were not associated with gestational age or birth weight. Prohepcidin levels at birth correlated positively with red cell counts (CC = 0.487, P = 0.025), unsaturated iron binding capacity (CC = 0.755, P = 0.001), total protein (CC = 0.624, P = 0.005), and serum albumin levels (CC = 0.500, P = 0.025), and negatively with serum iron levels (CC = -0.688, P = 0.003), but not ferritin levels. Multivariate analyses indicated that prohepcidin levels at birth were lower in infants with pregnancy-induced hypertension (P = 0.03) or premature rupture of membrane (P = 0.01).
Conclusions:
Prohepcidin production was physiologically low at birth of preterm infants according to the gestational age, and the levels might be susceptible to the in utero stress. The postnatal increase might reflect the maturation and/or adaptation of iron homeostasis.

Related Concept Videos
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:15
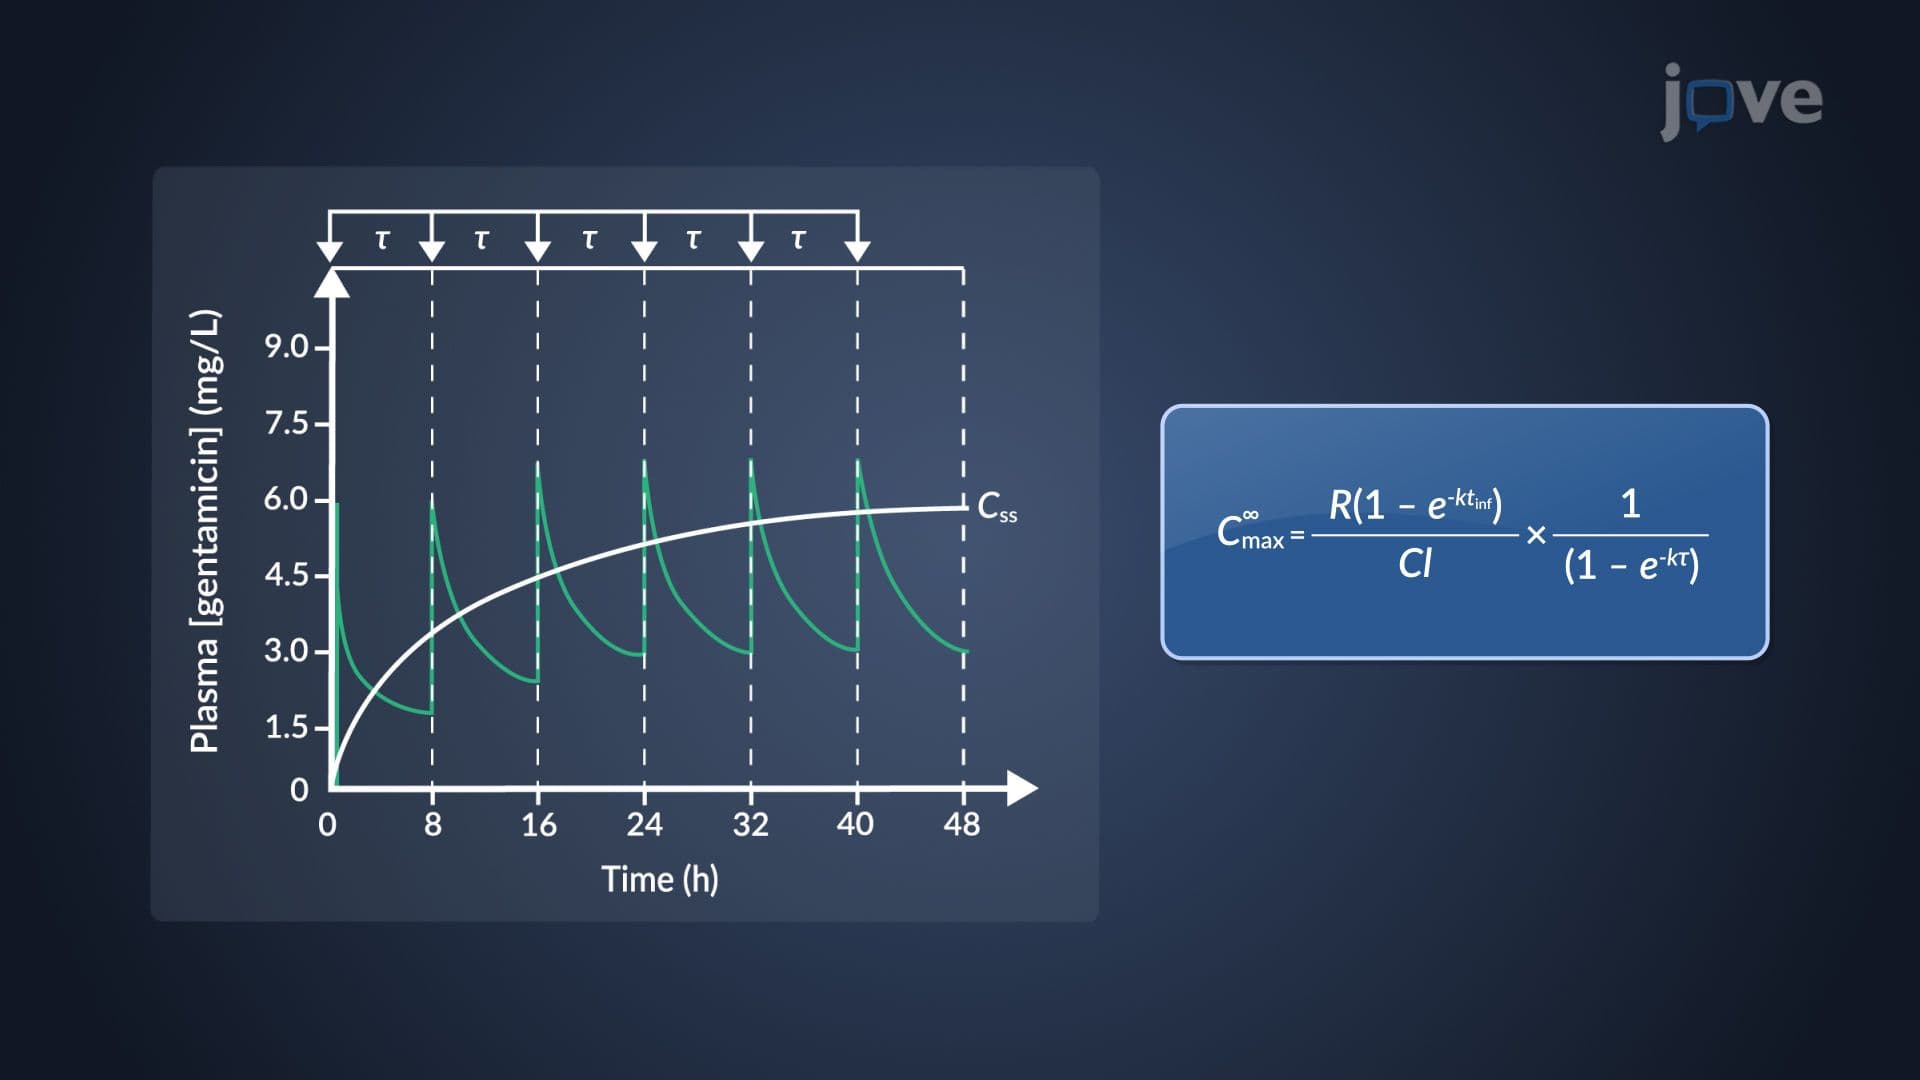
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations