Related Experiment Video
Updated: Jun 8, 2026
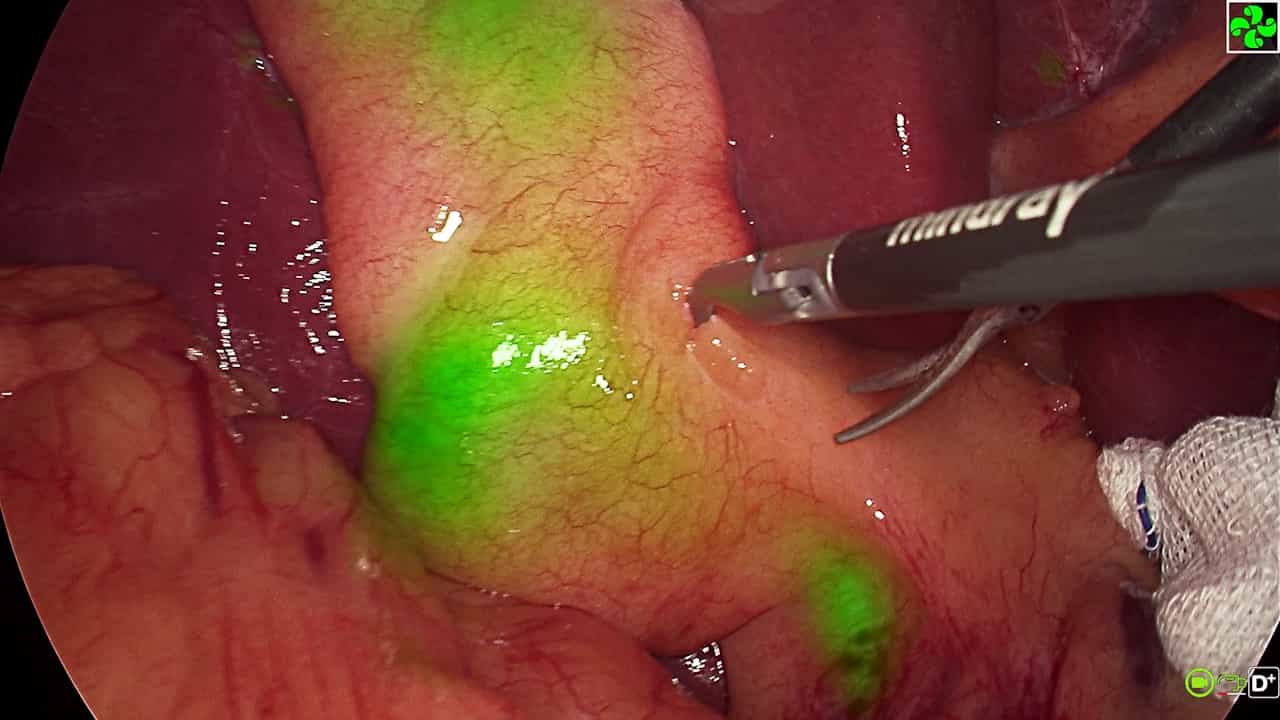

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Multimedia article. Successful endoscopic wire-guided balloon dilatation of angulated and tight ileal pouch
Emmanuel C Obusez1, Lei Lian, Abigail Oberc
1Cleveland Clinic Lerner College of Medicine and Pouchitis Clinic, Digestive Disease Institute, Desk A31, Cleveland Clinic Foundation, 9500 Euclid Ave, Cleveland, OH 44195, USA.

Background:
Ileal pouch strictures that are visually inaccessible by an endoscope may be balloon-dilated by exchange guide wire across the stricture with the aid of fluoroscopy. We present a technique of wire-guided balloon dilation without fluoroscopy to navigate strictures in the ileal pouch.
Methods:
A 50-year-old Caucasian female presented with a 24-year history of ulcerative colitis (UC) with restorative proctocolectomy and ileal pouch anal anastomosis (IPAA) for 7 years. She developed Crohn's disease (CD) of the pouch with multiple strictures at the afferent limb of the pouch and a pouch-vaginal fistula. On pouchoscopy, the patient had two strictures at the distal neoterminal ileum, at 10 cm and 15 cm proximal to the pouch inlet. In retrospect, the distal stricture was angulated and 1 cm in length, and the proximal one was ulcerated and pinhole in size, which prevented the passage of an endoscope (9.8-mm single-channel, GIF-H180; Olympus Optical, Tokyo, Japan). The stricture number and locations were confirmed by retrograde water-soluble contrast X-ray. There was great difficulty in negotiating the strictures with balloon dilation and hence concern that blind passage of the balloon into the strictures might induce mucosal trauma or perforation. A controlled radial expansion (CRE) wire-guided balloon dilation catheter (CRE TM Single-Use Wire Guided Balloon Dilator; Boston Scientific Microvasive, Natick, MA) was introduced through the scope. Wire exchange technique was applied with help of our endoscopy nurse (A.O.). The guide wire was passed through the strictures without any resistance under endoscopy view. Subsequently, the balloon was introduced across the strictures, and both were successfully dilated to 16 mm (Videos 1 and 2).
Results:
The procedure and postprocedure course were uneventful, and patient reported great symptomatic relief.
Conclusion:
Endoscopic guide-wire balloon dilation without fluoroscopic guidance appears to be feasible for CD-related strictures in experienced hands.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
Endoscopic Procedures V: ERCP
Patient...