Related Experiment Video
Updated: Jun 8, 2026


Minimally Invasive Murine Laryngoscopy for Close-Up Imaging of Laryngeal Motion During Breathing and Swallowing
Published on: December 1, 2023
Paraneoplastic jaw dystonia and laryngospasm with antineuronal nuclear autoantibody type 2 (anti-Ri)
Sean J Pittock1, Joseph E Parisi, Andrew McKeon
1Mayo Medical School College of Medicine, Mayo Clinic, Rochester, MN 55905, USA. pittock.sean@mayo.edu

Background:
Opsoclonus-myoclonus syndrome and breast carcinoma were initially described as neurologic and oncologic accompaniments of antineuronal nuclear autoantibody type 2 (ANNA-2, also known as anti-Ri). However, the neurologic spectrum of ANNA-2 autoimmunity is broader, includes a syndrome of jaw dystonia and laryngospasm, and can be accompanied by lung carcinoma.
Objective:
To describe clinically (with a video) ANNA-2-associated jaw dystonia and laryngospasm, its pathologic correlates, and therapeutic outcomes.
Design:
Retrospective case series with prospective clinical follow-up.
Setting:
Mayo Clinic's Neuroimmunology Laboratory, Rochester, Minnesota.
Patients:
Consecutive patients with ANNA-2 seropositivity identified since January 1, 1990.
Main Outcome Methods:
Clinical (in 9 patients) and neuropathologic (in 2 patients) findings were reviewed.
Results:
Of 48 patients with ANNA-2 seropositivity, 9 (19%) had multifocal neurologic manifestations that included jaw dystonia and laryngospasm. Among 6 patients with jaw dystonia, 5 had severely impaired nutrition, causing profound weight loss. Five patients had documented laryngospasm, which contributed to 1 patient's death. Neuropathologic examination revealed diffuse infiltration by CD8(+) T lymphocytes, with axonal loss and gliosis in brainstem and descending spinal cord tracts. Some patients improved symptomatically after immunosuppressant or cytotoxic therapies; 1 patient improved after treatment with botulinum toxin. One patient who underwent tracheostomy because of recurrent laryngospasm was alive and well longer than 3 years after symptom onset.
Conclusions:
Jaw dystonia and laryngospasm are common accompaniments of ANNA-2 autoimmunity and are associated with significant morbidity. We propose that selective damage to antigen-containing inhibitory fibers innervating bulbar motor nuclei by CD8(+) T lymphocytes (histopathologically observed infiltrating brainstem reticular formation) is the proximal cause of this syndrome. Early and aggressive therapy offers the prospect of neurologic improvement or stabilization.

Related Concept Videos
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:28
Rabies
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which leads...
 01:29
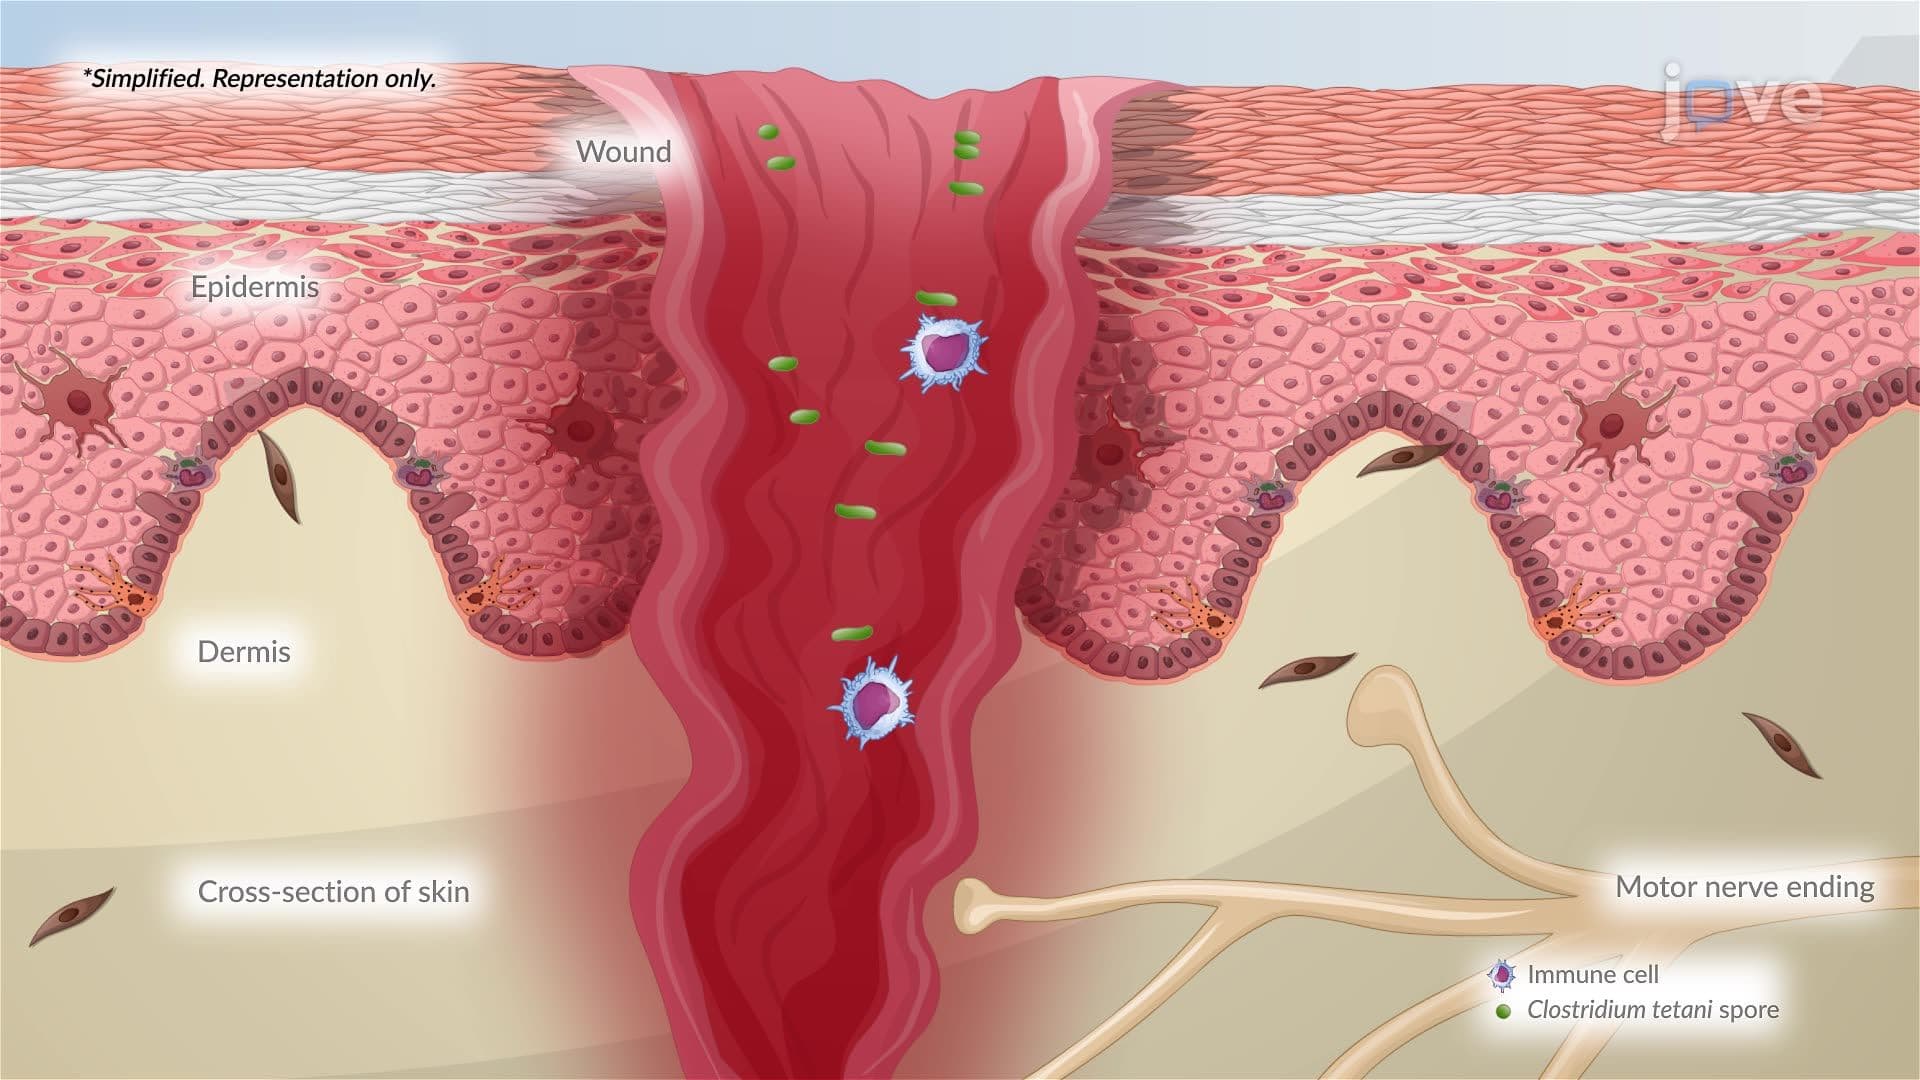
Tetanus
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...