Periprosthetic joint infection: treatment options
Related Experiment Video
Updated: Jun 8, 2026
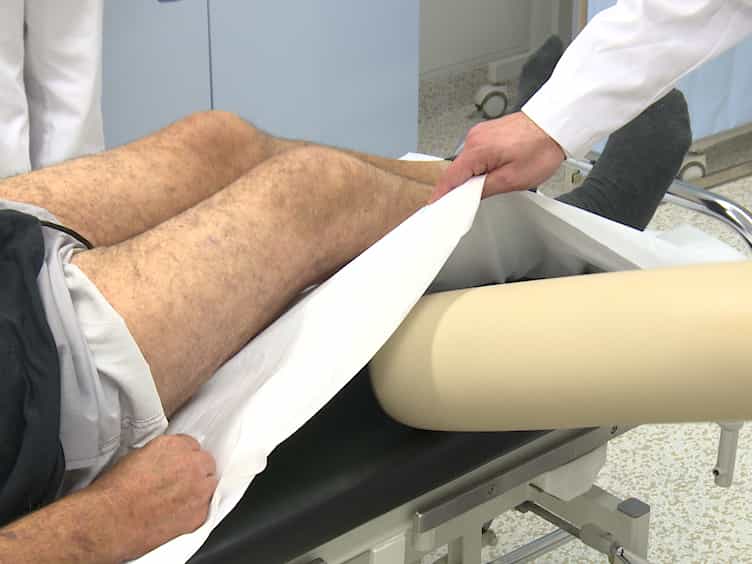
Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
Javad Parvizi1, Benjamin Zmistowski, Bahar Adeli
1Rothman Institute at Thomas Jefferson University, Philadelphia, Pennsylvania, USA. parvj@aol.com

Abstract:
Periprosthetic joint infection has become the most common cause of failure following total knee arthroplasty. Over the past 4 decades, treatment of this disease has evolved with technological innovations and pathogen profiling. The appropriate treatment selection is dependent on patient immune system quality, timing of symptom onset, and pathogen type. Antibiotic suppression alone is reserved for those cases without drainage, low-virulent antimicrobial-susceptible pathogens, and patients whose level of health increases the risk of surgery past any risk associated with chronic infection. In patients with an acute onset of symptoms and antimicrobial-susceptible pathogens, irrigation and debridement with exchange of modular components is moderately successful and offers the advantage of component retention and maximum knee function. In failed irrigation or chronic periprosthetic joint infection, resection of all components is necessitated. Resection and reimplantation can either be performed in one or two stages. A single-stage exchange has the potential to decrease the number of surgeries and therefore cost. However, the success rate of direct exchange is lower than that of two-stage revision. This has led to two-stage revision, with the placement of an intra-stage antibiotic-loaded spacer, to become the "gold" standard for periprosthetic joint infection eradication. In an immunocompromised patient with an uncontrollable periprosthetic joint infection, salvage procedures are necessitated. Complete eradication of periprosthetic joint infection is achieved by resection of all components without reimplantation through arthrodesis or above-the-knee-amputation. While amputation may be unpopular with patients it provides a greater ability to reconstruct, with an external prosthesis, a functioning joint.
Insights
Periprosthetic joint infection (PJI) treatment for total knee arthroplasty failure has evolved. Two-stage revision with an antibiotic spacer is the gold standard for PJI eradication, balancing success and function.
Area of Science:
- Orthopedic Surgery
- Infectious Diseases
- Biomedical Engineering
Background:
- Periprosthetic joint infection (PJI) is the leading cause of total knee arthroplasty failure.
- Treatment strategies have advanced with technology and pathogen understanding over four decades.
Purpose of the Study:
- To review the evolving treatment landscape for periprosthetic joint infection (PJI) after total knee arthroplasty.
- To outline current treatment selection criteria based on patient factors and infection characteristics.
Main Methods:
- Review of treatment modalities including antibiotic suppression, irrigation and debridement with component exchange, and single-stage vs. two-stage revision.
- Discussion of salvage procedures like arthrodesis and amputation for uncontrollable infections.
Main Results:
- Two-stage revision with an antibiotic-loaded spacer is the current gold standard for PJI eradication.
- Irrigation and debridement with component exchange offers component retention for acute infections.
- Salvage procedures are necessary for immunocompromised patients with uncontrollable PJI.
Conclusions:
- Treatment selection for PJI depends on patient immunity, symptom onset, and pathogen profile.
- Two-stage revision provides the highest success rate for PJI eradication.
- Salvage options like amputation may be required for severe, refractory cases.

Related Concept Videos
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:18
Endocarditis III: Medical Management
 01:29
Endocarditis IV: Nursing Management
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:26
Tonsillitis II: Management
 01:25
Endocarditis I: Introduction