Related Experiment Video
Updated: Jun 8, 2026

Fu's Subcutaneous Needling for Knee Osteoarthritis Pain
Published on: March 24, 2023
Unexplained pain after THR: what should i do?
1Alabama Spine and Joint Center, P.C., Birmingham, Alabama, USA. jcuckler@charter.net

Abstract:
Early causes of hip pain within the first year of total hip replacement (THR) include failure of fixation, infection, instability, other sources of pain (eg, lumbar spine), and mechanical dysfunction such as psoas tendon impingement or other soft tissue irritation. Metal-on-metal THRs may present with pain due to hypersensitivity within the first 1 to 3 years after arthroplasty. Late causes of pain include loosening, wear reactions, or mechanical dysfunction such as subluxation associated with wear of the articular couple. Late hematogenous infection is often sudden in onset, but may be subtle. Other sources of pain such as spinal stenosis or lumbar degenerative disk disease may also present as hip pain. Evaluation of the painful hip should start with a careful history: is the current pain similar or different to the preoperative symptoms? A review of the preoperative radiographs will provide clues as to the extent of the pathology, and if not obvious, may suggest other sources for the pain syndrome. Careful comparison of serial radiographs is necessary to identify loosening. Serologic tests should include a sedimentation rate and C-reactive protein; if both are elevated, aspiration of the joint under radiograph control for culture is indicated. In the absence of abnormalities in the studies described above, serial Technetium bone scans performed every 6 to 12 months may suggest loosening if progressive increases in uptake are observed about a component. Malposition of the acetabular component may be associated with psoas tendon impingement (symptomatic with active flexion of the hip) and may be confirmed by computed tomography scan or a psoas tenosynogram. Hypersensitivity of metal-on-metal THRs should be suspected in the presence of early (subtle) osteolysis, and the presence of predominantly mononuclear cells on the sterile aspirate. Perseverance and patience are encouraged in the pursuit of an accurate diagnosis, and objective analysis of the data is necessary. Do not operate without sufficient cause.
Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Pericarditis IV: Nursing Management
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:19
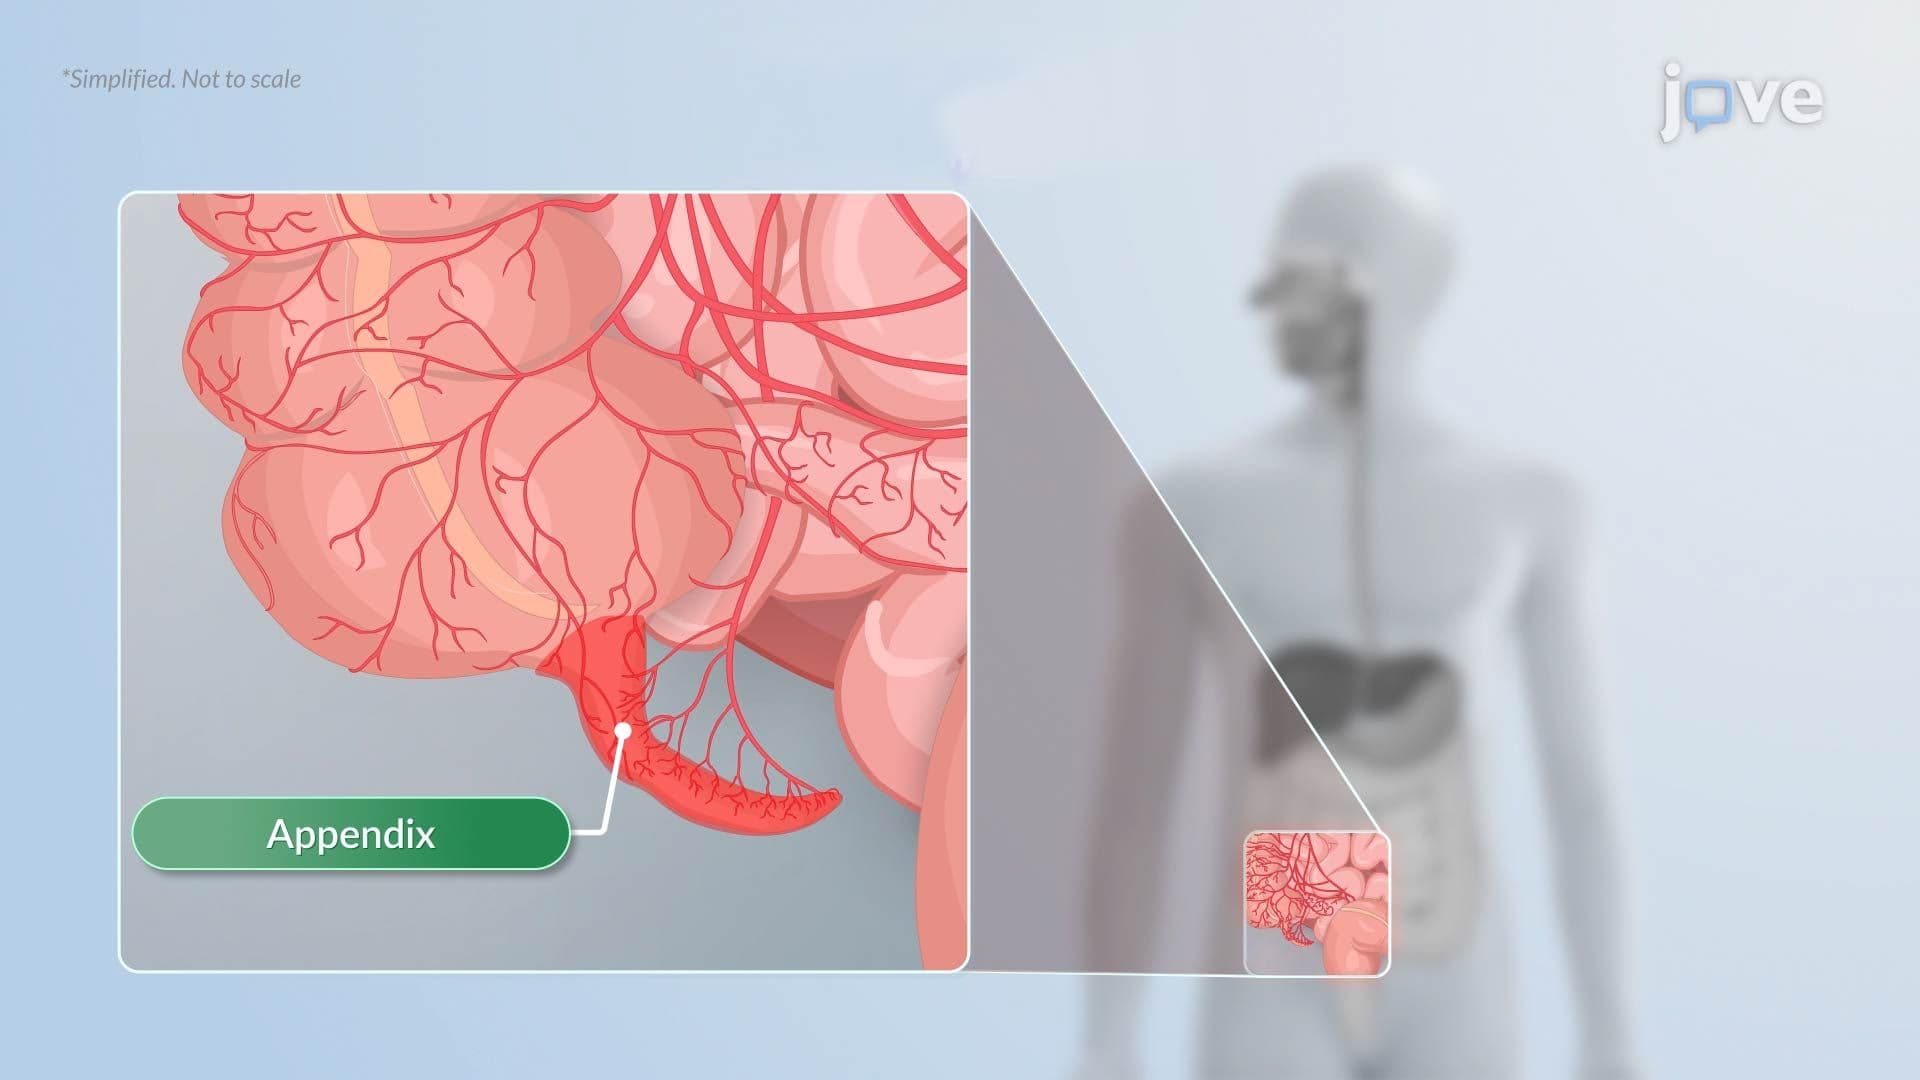
Appendicitis