Related Experiment Video
Updated: Jun 8, 2026
A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Acute pulmonary embolism. Part 2: treatment
Josien van Es1, Renée A Douma, Victor E A Gerdes
1Department of Vascular Medicine, Academic Medical Center, Meibergdreef 9, 1105 AZ Amsterdam, The Netherlands. j.vanes@amc.uva.nl

Abstract:
The clinical presentation of pulmonary embolism (PE) varies widely, ranging from only limited symptoms to severe cardiogenic shock. Treatment of PE comprises initial therapy--with low-molecular-weight heparin (LMWH), fondaparinux, or unfractionated heparin--and long-term treatment, most commonly with vitamin-K antagonists (VKAs). Methods of risk stratification, to determine whether a patient will benefit from thrombolysis, are currently under investigation. However, at present, insufficient evidence exists that hemodynamically stable patients who demonstrate echocardiographic right ventricular strain (submassive PE) benefit from thrombolysis. By contrast, thrombolysis is a widely accepted treatment strategy for patients with hemodynamic shock (massive PE). The duration of VKA treatment is commonly 3-12 months and depends on the type of PE and on the balance between the risks of recurrent PE, major bleeding, and the patient's preference. In patients with a malignancy, treatment with LMWH during the first 6 months after diagnosis of PE is recommended. Several new oral anticoagulants, such as factor IIa and factor Xa inhibitors, are now being investigated. For prevention of recurrent PE in situations where anticoagulation is contraindicated, a temporary inferior vena cava filter might be useful. Some patients with PE can be safely treated at home, but few outcome studies in this setting have been published.
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
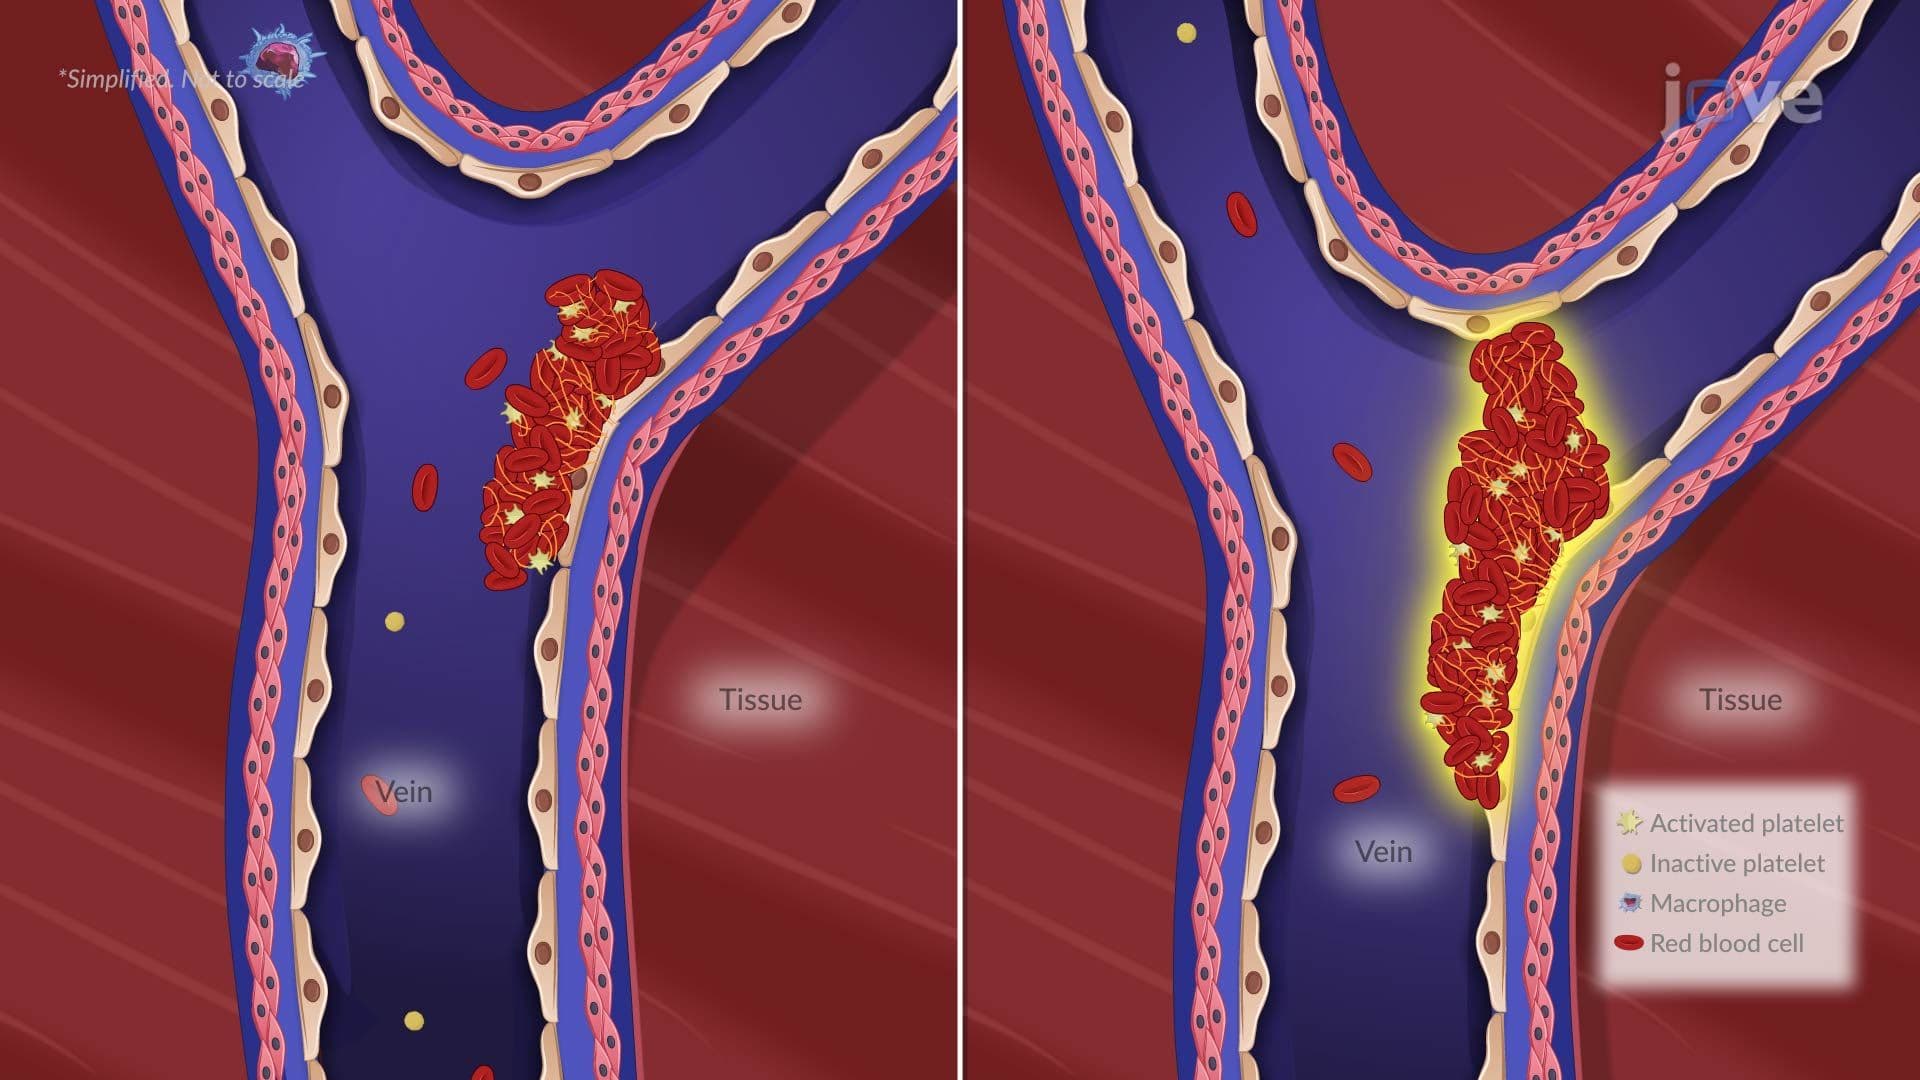
Pulmonary Embolism I: Introduction
 01:19
Pulmonary Embolism I: Introduction
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:27
Pneumothorax-II
Clinical Manifestations: