Coronary branch steal: experimental validation and clinical implications of interacting stenosis in branching coronary arteries
Related Experiment Video
Updated: Jun 8, 2026
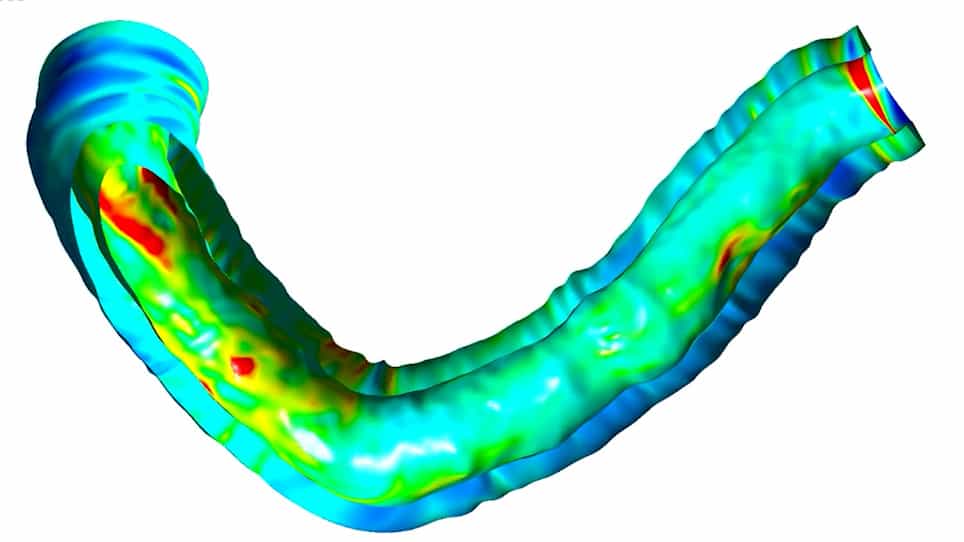
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
K Lance Gould1, Richard Kirkeeide, Nils P Johnson
1The Weatherhead P.E.T. Center for Preventing and Reversing Atherosclerosis and the Department of Medicine, Division of Cardiology, University of Texas Medical School at Houston, and Memorial Hermann Hospital, Houston, Tex., USA. k.lance.gould@uth.tmc.edu

Background:
fluid dynamic analysis predicts a new concept in coronary physiology that we call "branch steal," whereby stenosis proximal and distal to arterial branching interact with the nonstenotic branch between stenosis that shunts or "steals" flow away from the distal stenotic artery during reactive hyperemia, tested experimentally.
Methods And Results:
in 21 large hounds under surgical anesthesia, proximal and distal left circumflex and obtuse marginal coronary arteries were instrumented with electromagnetic flowmeters, proximal and distal machined Teflon screw-down stenosers with round concentric closing and distal silk-in-tubing sleeve occluders. Baseline reactive hyperemia was recorded after 15-second occlusions of both arteries at baseline and for progressive distal stenosis during each step of progressive proximal stenosis. At each combination of stenosis, a coronary arteriogram was obtained using left Judkins catheters and Philips cine calibrated with modulated transfer function to ± 0.1 mm accuracy for fluid dynamic analysis of arterial stenosis-branching anatomy. In 324 experiments of parent-child stenosis combinations of the left circumflex artery with an intervening obtuse marginal branch, coronary flow reserve (CFR) calculated by the fluid dynamic model accounting for stenosis-branch interactions and "branch steal" correlated with CFR directly measured by flowmeter (linear regression, CFRartgm=0.18+0.7×CFRflowmtr with Pearson r=0.73). Quantitative arteriography and positron emission tomography perfusion imaging confirmed the concept in clinical examples.
Conclusions:
functional severity of anatomically fixed stenosis is not constant, specific, or independent of other stenosis in branching coronary arteries but requires analysis as an integrated component of the entire branching coronary artery tree to guide revascularizations.
Related Concept Videos
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Coronary Artery Disease I: Introduction
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
Coronary Artery Disease IV: Preventive Measures