Related Experiment Video
Updated: Jun 8, 2026

Mechanism of Regulation of Adipocyte Numbers in Adult Organisms Through Differentiation and Apoptosis Homeostasis
Published on: June 3, 2016
Catecholamines, adiponectin, and insulin resistance as measured by HOMA in children with obstructive sleep apnea
Andrea Kelly1, Shayne Dougherty, Andrew Cucchiara
1Division Endocrinology/Diabetes, The Children's Hospital of Philadelphia, Philadelphia, PA, 19104, USA. kellya@email.chop.edu

Insights
Obstructive sleep apnea (OSA) in obese pubertal children is linked to worse insulin resistance and lower adiponectin. Worsening OSA correlates with increased urinary catecholamines, suggesting a potential role in metabolic dysfunction.
Area of Science:
- Pediatric Endocrinology
- Sleep Medicine
- Metabolic Syndrome Research
Background:
- Obstructive sleep apnea (OSA) is increasingly recognized for its role in metabolic syndrome development.
- The interplay between OSA, obesity, puberty, and insulin resistance in children is complex and requires further elucidation.
Purpose of the Study:
- To investigate the association between OSA and insulin resistance in obese children, accounting for pubertal status.
- To examine the relationship between OSA, adiponectin levels, and catecholamine excretion.
- To explore the potential mediating role of catecholamines in OSA-related metabolic changes.
Main Methods:
- Recruitment of normal controls and children with suspected OSA, categorized by pubertal status (pubertal/prepubertal).
- Performance of overnight polysomnography (PSG) to diagnose OSA (Total-AHI ≥ 1.5 events/h).
- Measurement of fasting glucose, insulin, adiponectin, and 24-hour urinary catecholamines; calculation of HOMA for insulin resistance; adjustment for BMI.
Main Results:
- Obese pubertal children with OSA showed increased risks of elevated insulin and HOMA (insulin resistance).
- Polysomnography markers of OSA, particularly Total-AHI, were negatively associated with adiponectin in pubertal children.
- Higher Total-AHI and oxygen desaturation correlated with increased urinary normetanephrine and norepinephrine.
Conclusions:
- In obese pubertal children, OSA is associated with heightened insulin resistance.
- Worsening OSA severity correlates with decreased adiponectin and elevated urinary catecholamines.
- Further research is warranted to confirm direct causal links and understand the implications of pediatric OSA for metabolic health.
Introduction:
Obstructive sleep apnea (OSA) has been implicated in the pathophysiology of metabolic syndrome. Its contribution to insulin resistance is complicated by obesity and puberty. We hypothesized that OSA is associated with worse insulin resistance and lower adiponectin after adjustment for obesity and puberty and that catecholamines might mediate these changes.
Methods:
Normal controls and children with suspected OSA were recruited and categorized as pubertal or prepubertal. Overnight polysomnography (PSG) was performed. Subjects were categorized as OSA for total apnea hypopnea index (Total-AHI) > or = 1.5 events/h. Fasting blood glucose, insulin, adiponectin, and 24-hour urinary catecholamines were obtained. Homeostatic model assessment of insulin resistance (HOMA) was calculated. The independent effects of OSA upon HOMA, adiponectin, and urinary catecholamines following adjustment for body mass index (BMI) were determined. RESULTS (median; min, max): Subjects (n = 98, 42F; 11 +/- 4 years, 37 prepubertal) were generally overweight (BMI-Z = 2.1; -3, 4.1) and had wide-ranging insulin sensitivities (HOMA = 2.7; 0.5, 27) and PSG parameters (Total-AHI = 1.6; 0, 185). The risks of elevated insulin (P = 0.04) and HOMA (P = 0.05) were higher in OSA vs non OSA obese pubertal children. Polysomnographic markers of OSA, including Total-AHI (P = 0.001, R2 = 0.32), were negatively associated with adiponectin in pubertal children. Total-AHI and oxygen desaturation were associated with higher urinary normetanephrine and norepinephrine.
Conclusions:
In obese pubertal children, OSA was associated with worse insulin resistance. Worsening OSA was associated with lower adiponectin and increasing urinary catecholamines. Whether OSA directly lowers adiponectin and aggravates a predisposition to insulin resistance is unknown, but these preliminary findings highlight the importance of further studying pediatric OSA.

Related Concept Videos
 01:26
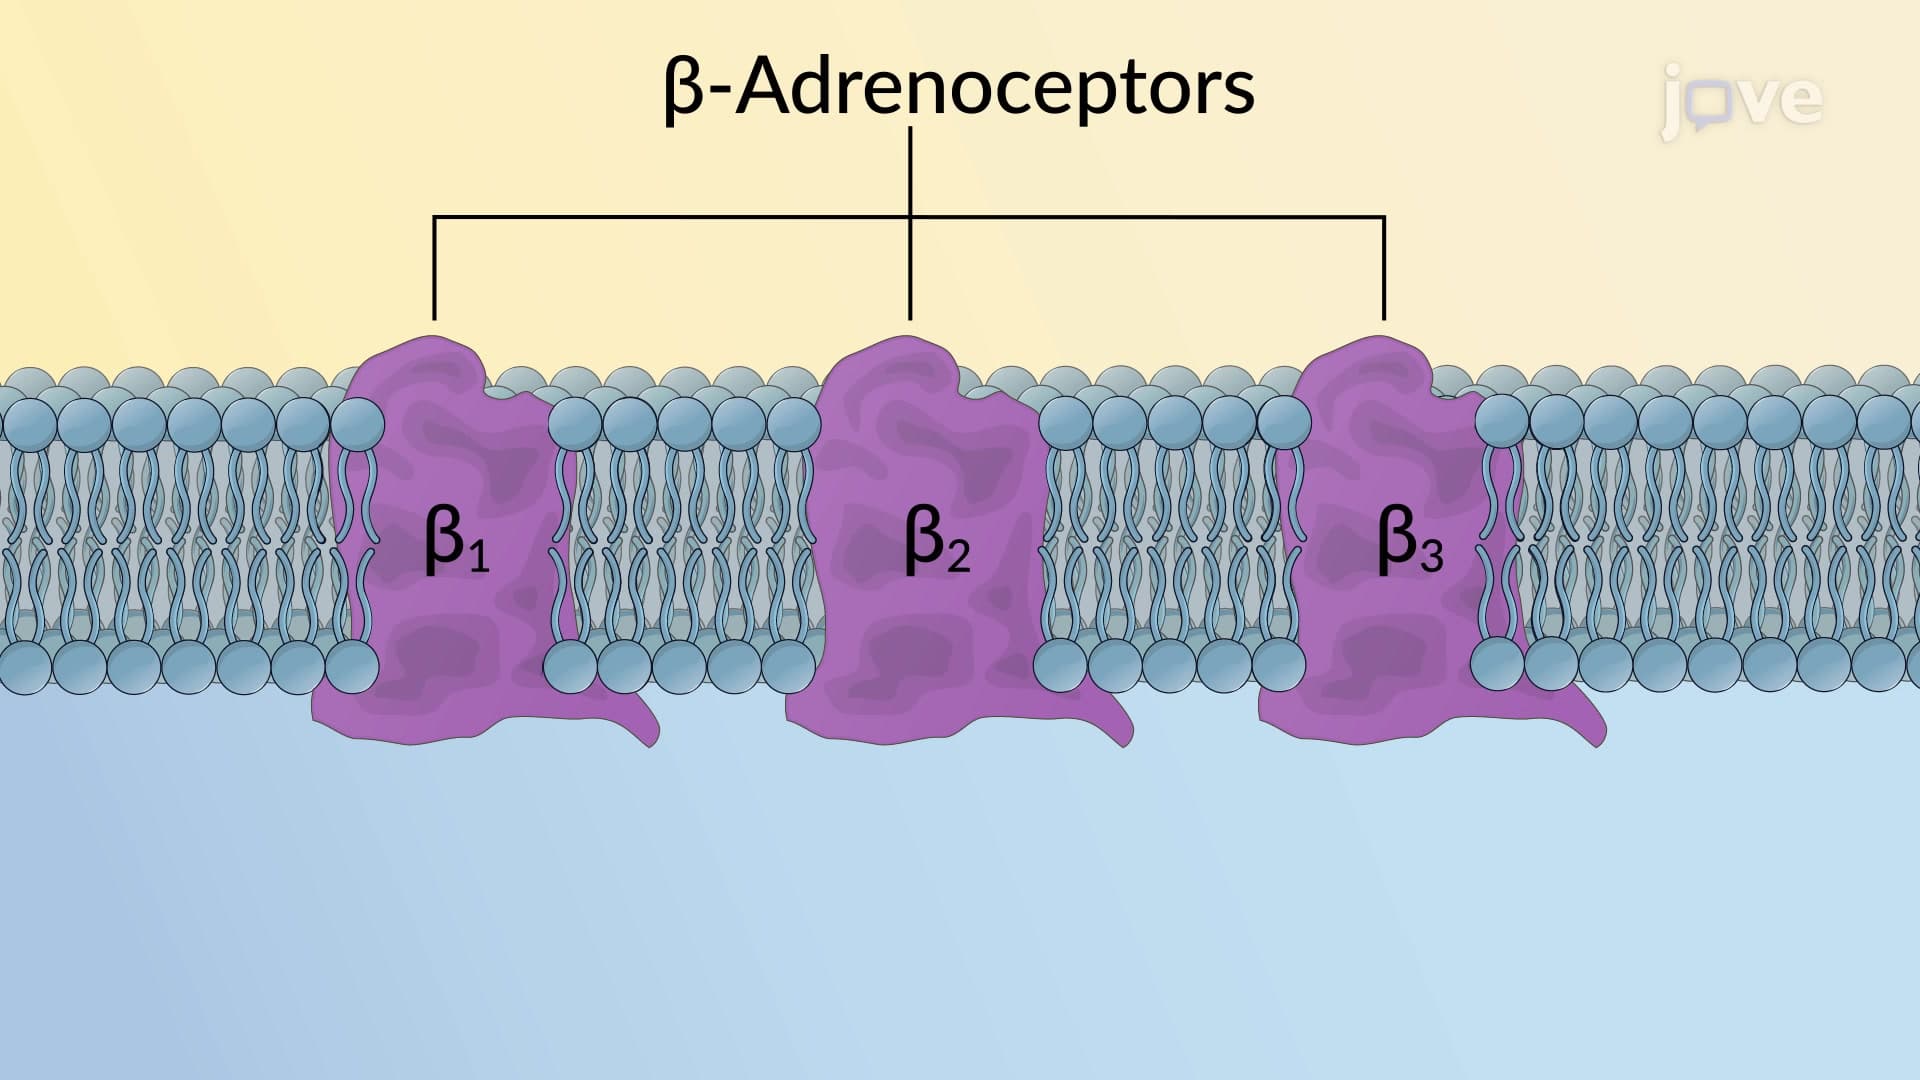
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:30
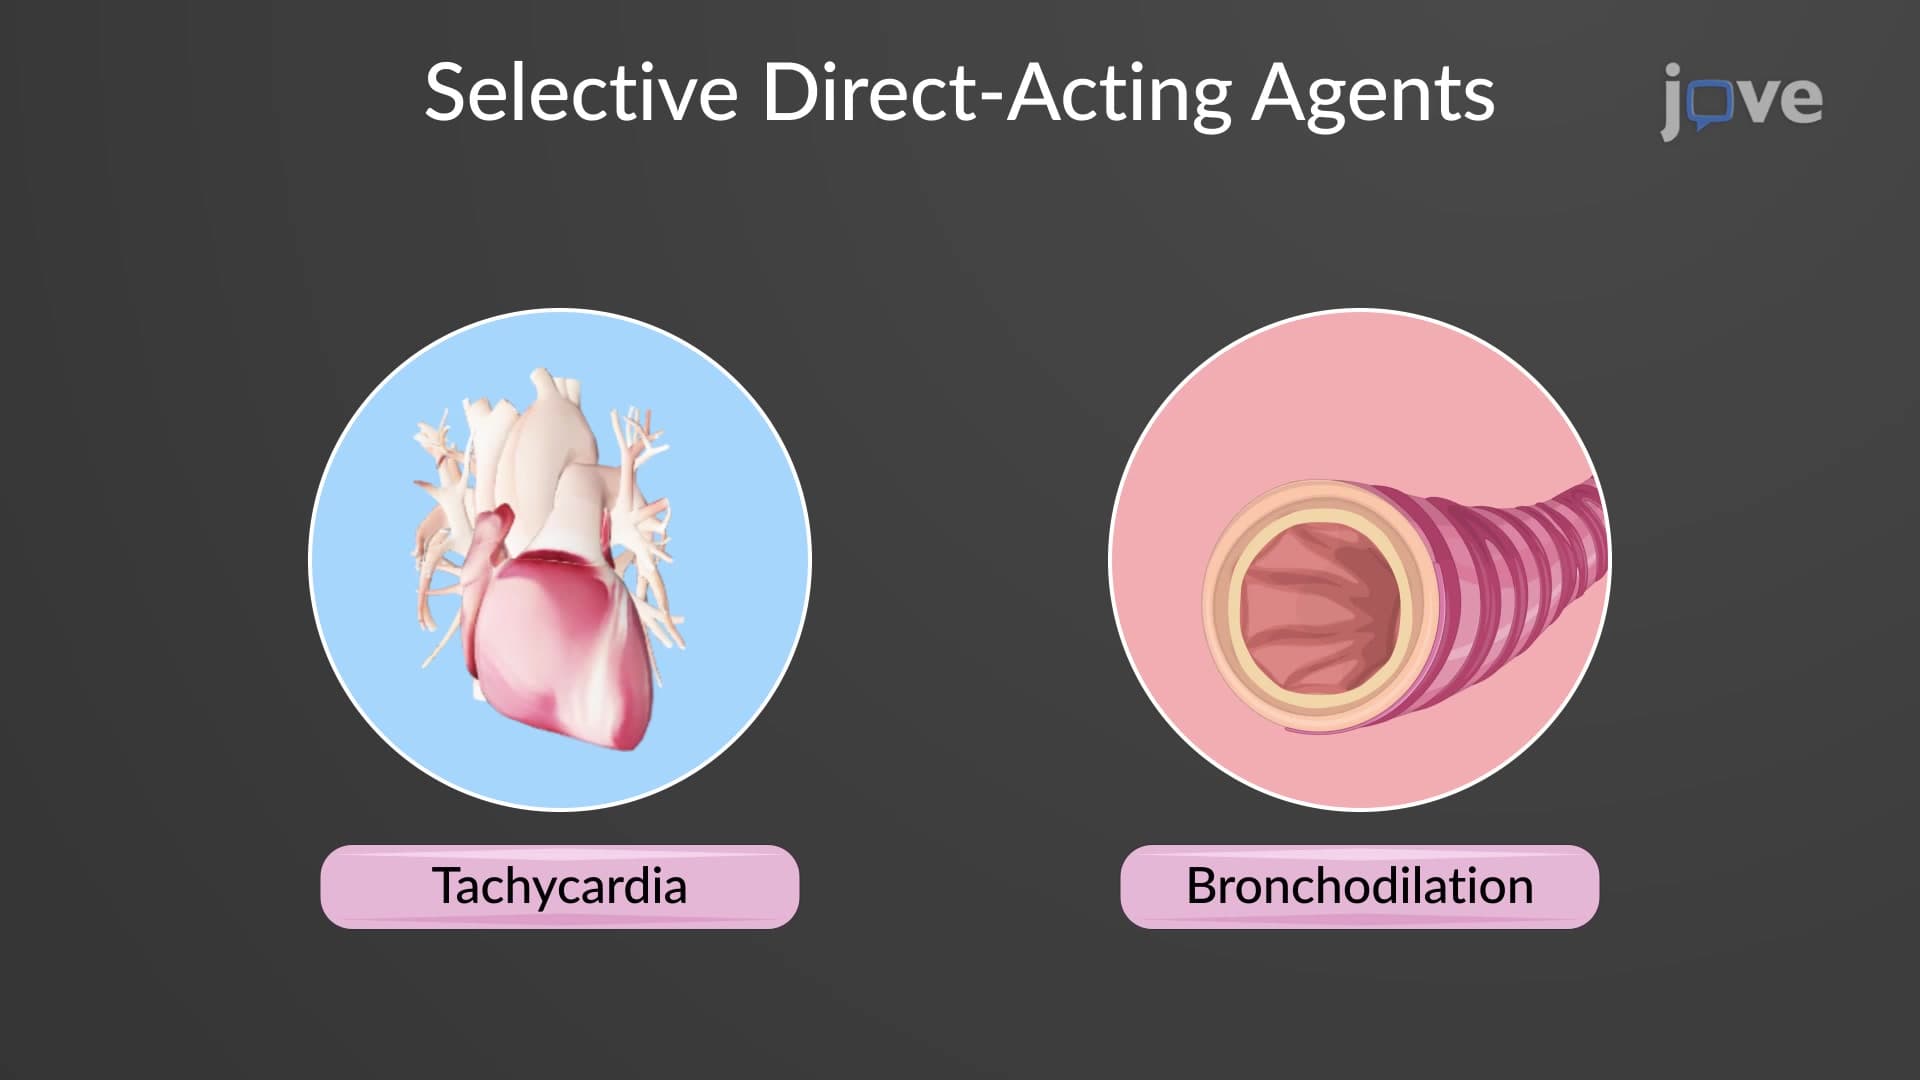
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:24
Obesity
 01:30
Regulation of Food Intake