Related Experiment Video
Updated: Jun 8, 2026
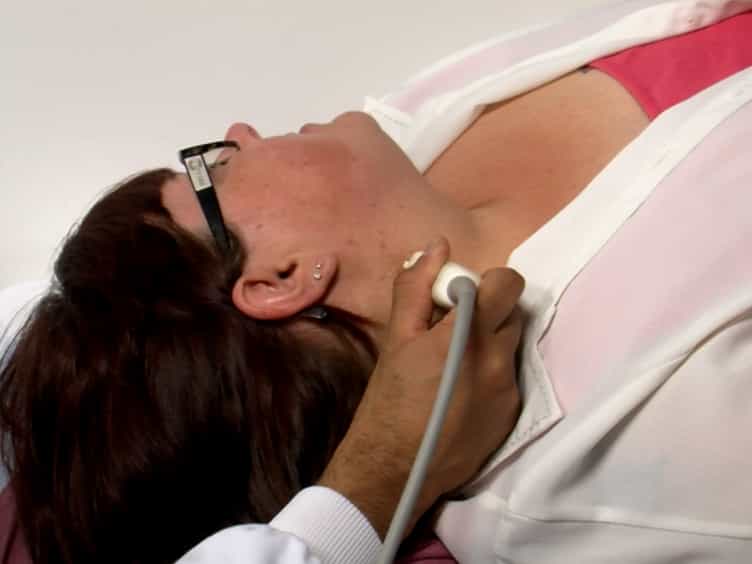

A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
The distinct relationships of carotid plaque disease and carotid intima-media thickness with left ventricular
Navtej S Chahal1, Tiong K Lim, Piyush Jain
1Department of Cardiovascular Medicine, Northwick Park Hospital, Harrow, UK.

Background:
Subclinical carotid atherosclerosis has been associated with impaired left ventricular (LV) function and the development of heart failure. Whether impaired LV function is related primarily to increased intima-media thickness (IMT) or burden of plaque disease or both remains to be determined.
Methods:
A total of 2,279 subjects without clinical cardiovascular disease recruited from the London Life Sciences Prospective Population cohort study were studied. Carotid ultrasonography and transthoracic echocardiography were performed on all subjects. Carotid IMT and plaque scores were measured, and their relationships with LV volumes, LV ejection fraction, myocardial LV longitudinal function (Sa and Ea velocities), and LV filling pressure (E/Ea ratio) were assessed before and after adjustment for covariates.
Results:
Compared with those without carotid artery disease, subjects with either increased IMT and/or presence of plaque disease had identical Sa velocities (both 9.0 cm/sec), lower Ea velocities (8.7 vs 9.9 cm/sec, P < .001) and higher E/Ea ratios (8.4 vs 7.6, P < .001). After multiple linear regression analysis, increasing IMT remained independently related to reduced Ea velocity (P < .001) but not LV ejection fraction, Sa velocity, or E/Ea ratio. In a separate adjusted analysis, subjects with severe burdens of carotid plaque disease (more than five plaques) had reduced LV ejection fractions (β = -2.9; 95% confidence interval [CI], 1.0 to 4.8, P = .003), attenuated Sa velocities (β = -0.79; 95% CI, -1.2 to -0.3, P = .003), attenuated Ea velocities 2 (β = -0.79; 95% CI, -1.3 to -0.2, P = .007), and increased E/Ea ratios (β = 0.84; 95% CI, 0.2 to 1.5, P = .009) compared to individuals without carotid plaques.
Conclusion:
These findings demonstrate that subclinical carotid plaque disease rather than IMT is more closely related to LV systolic function and LV filling pressure. These data support the application of carotid ultrasonography beyond cardiovascular disease risk prediction, while providing insight into potential mechanisms underlying the development of subclinical LV dysfunction.

Related Concept Videos
 01:30
Atherosclerosis I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:26
Coronary Artery Disease II: Pathophysiology
 01:30
Coronary Artery Disease I: Introduction
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:24
Cardiac Catheterization III: Left Heart Catheterization