Related Experiment Video
Updated: Jun 8, 2026
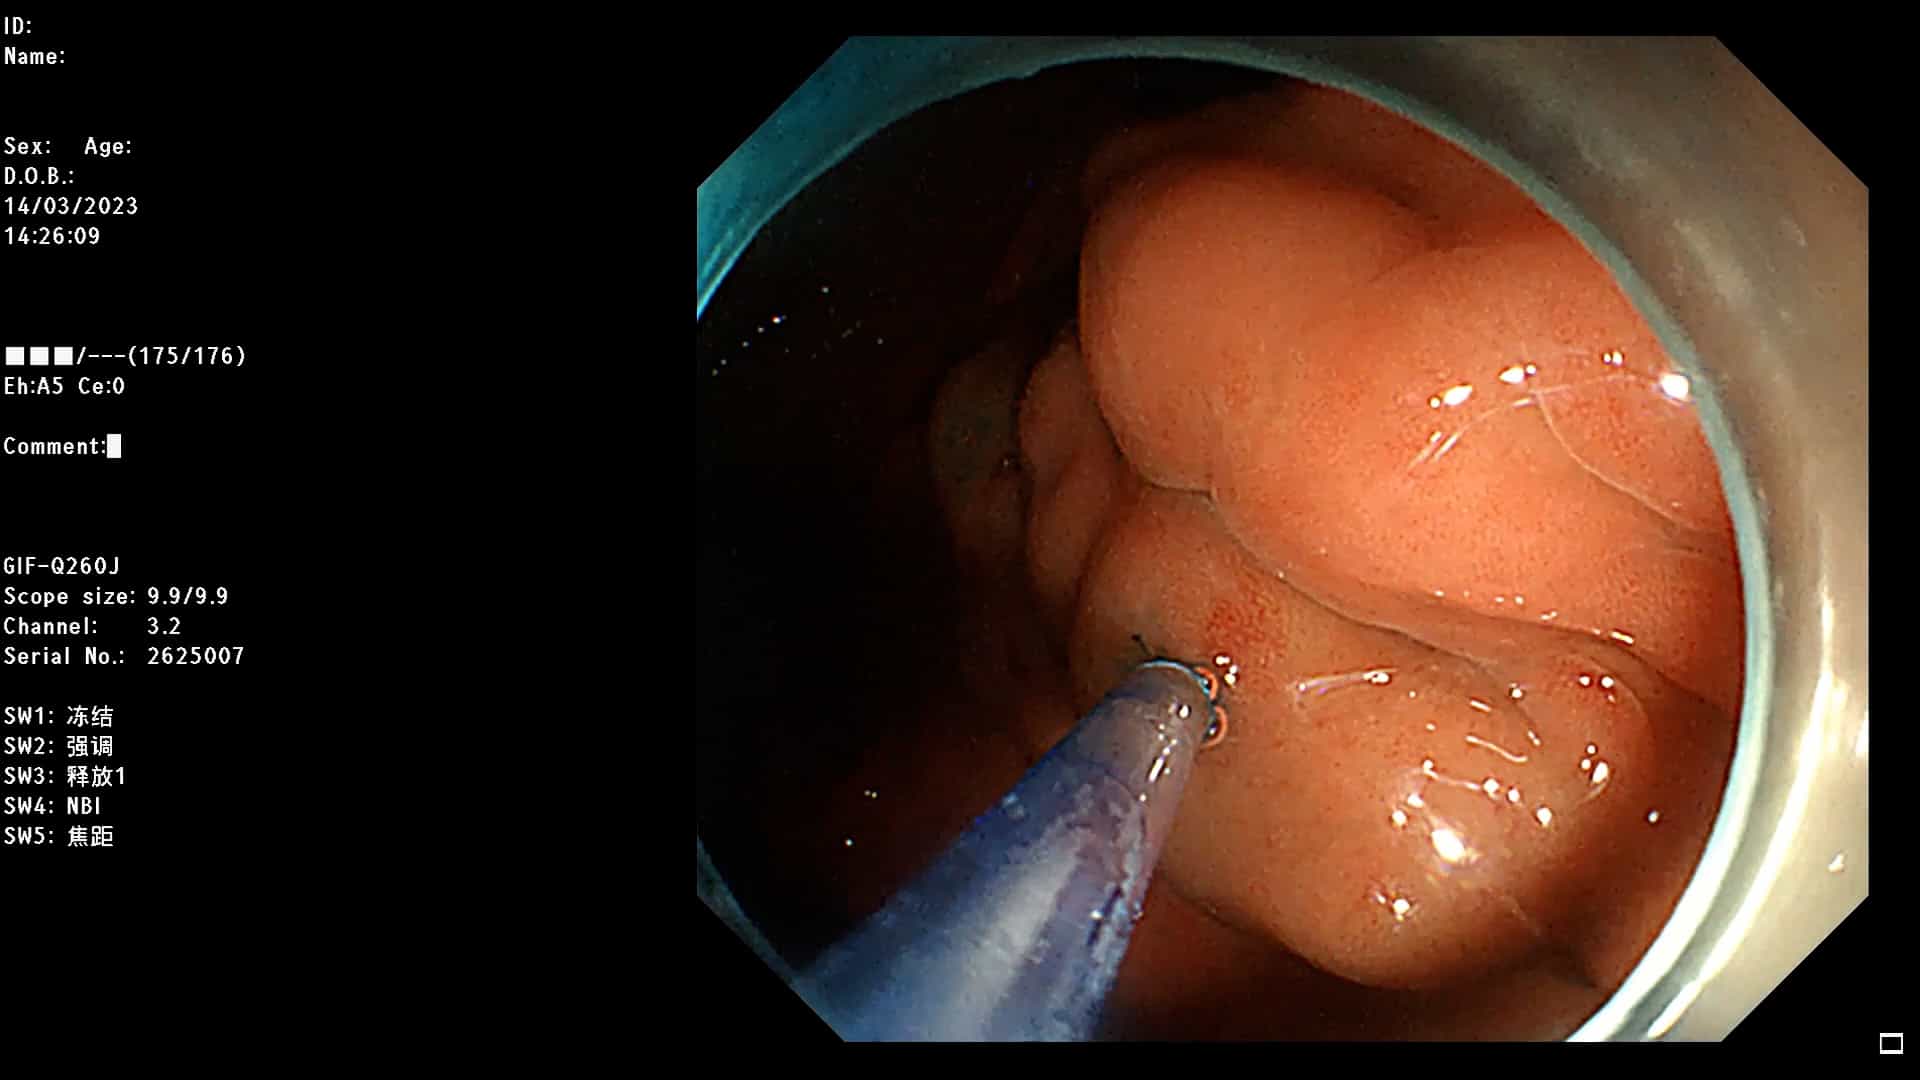
Endoscopic Injection Sclerotherapy Assisted by Cyanoacrylate and Clips for Gastroesophageal Varices
Published on: June 13, 2025
A summary of recent recommendations on the management of patients with nonvariceal upper gastrointestinal bleeding
Joshua Greenspoon1, Alan Barkun
1Division of Gastroenterology, The McGill University Health Center, Montreal General Hospital, Montreal, Canada.

Abstract:
Recommendations in managing patients with nonvariceal upper gastrointestinal bleeding were recently updated, addressing resuscitation, risk assessment and pre-endoscopic care, endoscopy, pharmacotherapy, and secondary prophylaxis. Initial adequate resuscitation and risk stratification using validated scales remain critical. Intravenous erythromycin improves visualization when likely to find blood in the stomach. Pre-endoscopic proton pump inhibition (PPI) does not improve outcomes, but downstages high-risk endoscopic lesions and may be considered. In patients on anticoagulants, correction of a coagulopathy is recommended, but should not delay early endoscopy (within 24 h), as it improves clinical outcomes. In patients with high-risk endoscopic stigmata, although better than doing nothing, epinephrine injection alone provides suboptimal efficacy and should be combined with another modality such as clips, thermal or sclerosant injection, which are also efficacious alone. Following an attempt at dislodgment, adherent clots can be treated with high-dose intravenous PPI infusion alone (80 mg bolus and 8 mg/h for 3 days) or following endoscopic hemostasis. The combination is indicated for all other patients with high-risk stigmata as there is currently a lack of high-quality generalizable data supporting other intravenous or oral PPI regimens. A second-look endoscopy is recommended only selectively after endoscopic hemostasis. A negative Helicobacter pylori test requires confirmation in the acute setting. Following appropriate discussions, acetylsalicylic acid (ASA) can soon be restarted acutely after bleeding; long-term PPI co-therapy is imperative in patients having bled on nonsteroidal anti-inflammatory drugs if still needed (preferably with a cyclooxygenase-2, if appropriate) or ASA (not clopidogrel alone). Further work is needed to implement and disseminate these recommendations.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:30
Venous Thrombosis IV: Nursing Management
 01:24
Esophageal Varices-I: Introduction