Related Experiment Video
Updated: Jun 8, 2026


Esophageal Heat Transfer for Patient Temperature Control and Targeted Temperature Management
Published on: November 21, 2017
Heated humidification versus heat and moisture exchangers for ventilated adults and children

Background:
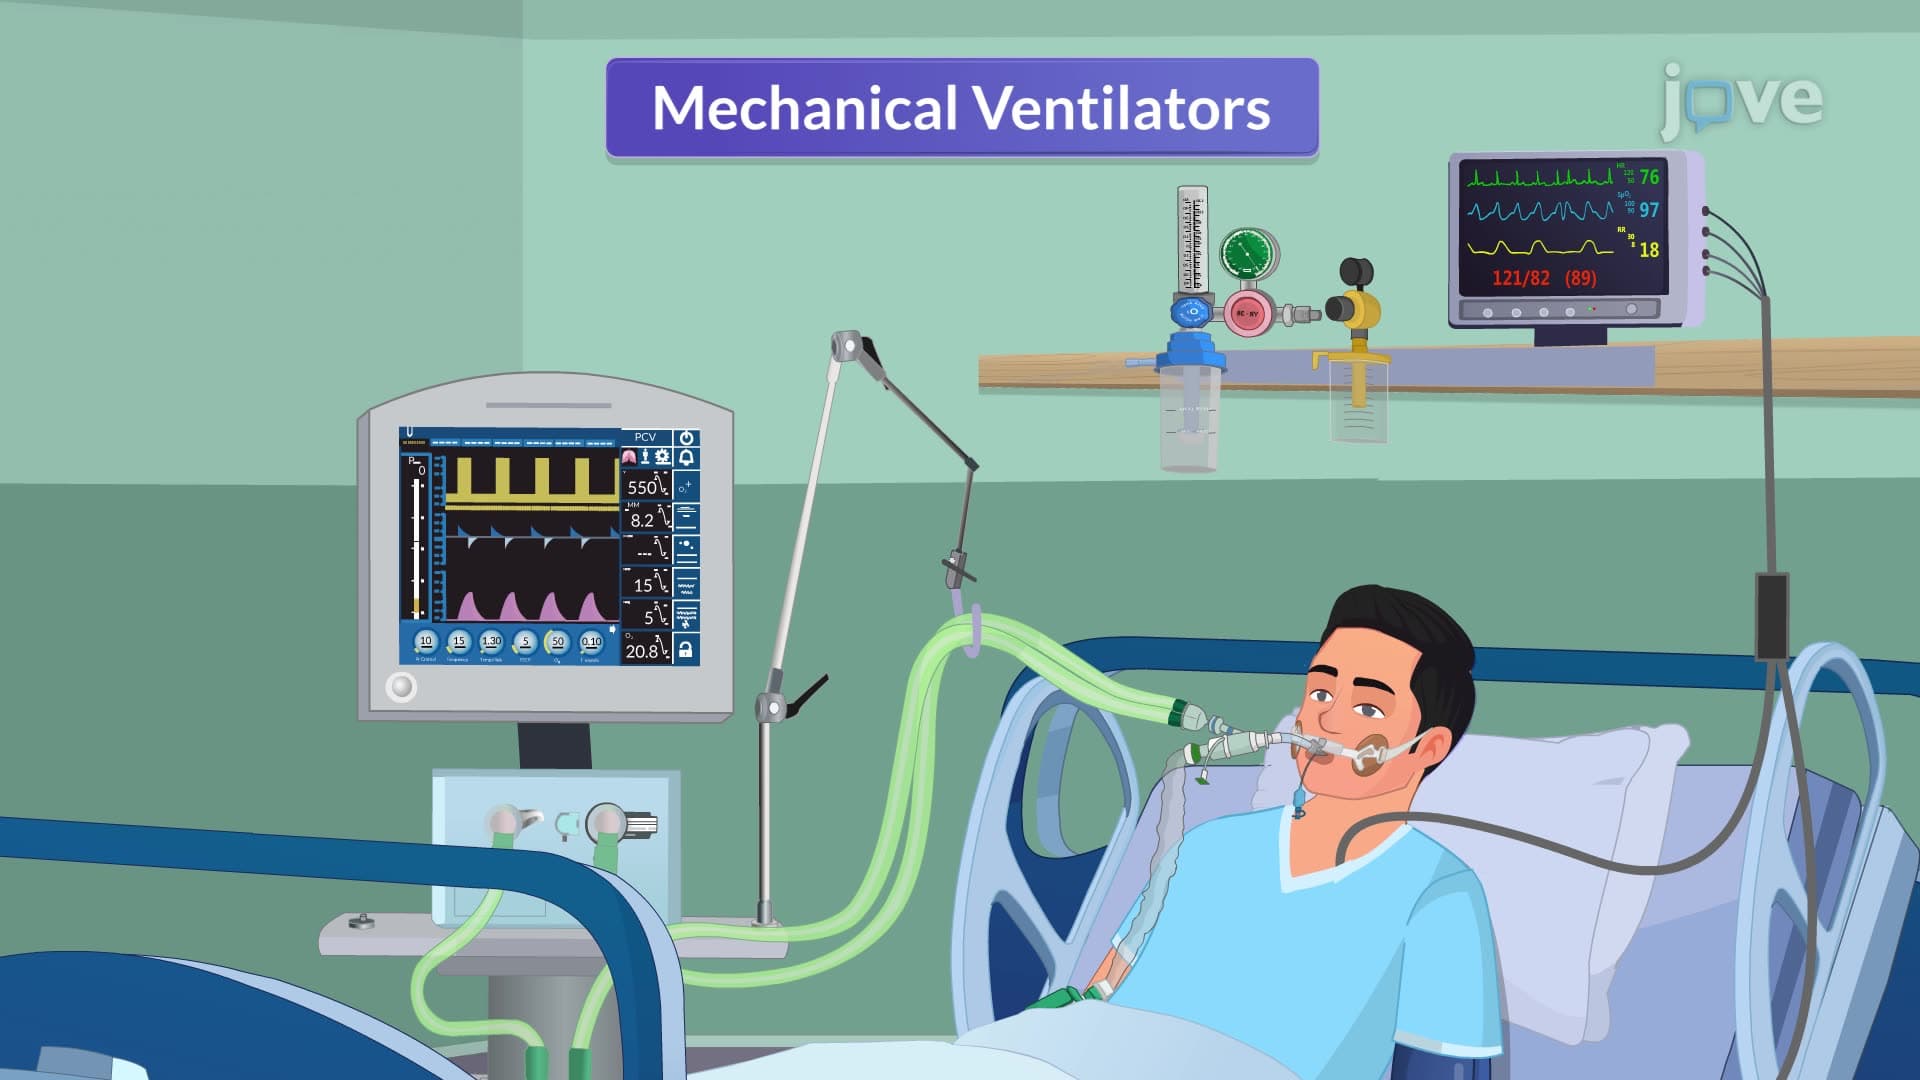
Humidification by artificial means must be provided when the upper airway is bypassed during mechanical ventilation. Heated humidification (HH) and heat and moisture exchangers (HMEs) are the most commonly used types of artificial humidification in this situation.
Objectives:
To determine whether HHs or HMES are more effective in preventing mortality and other complications in people who are mechanically ventilated.
Search Strategy:
We searched the Cochrane Central Register of Controlled Trials (The Cochrane Library 2010, Issue 4) and MEDLINE, EMBASE and CINAHL (January, 2010) to identify relevant randomized controlled trials.
Selection Criteria:
We included randomized controlled trials comparing HMEs to HHs in mechanically ventilated adults and children. We included randomized crossover studies.
Data Collection And Analysis:
We assessed the quality of each study and extracted the relevant data. Where appropriate, results from relevant studies were meta-analyzed for individual outcomes.
Main Results:
We included 33 trials with 2833 participants; 25 studies were parallel group design (n = 2710) and 8 crossover design (n = 123). Only 3 included studies reported data for infants or children. There was no overall effect on artificial airway occlusion, mortality, pneumonia, or respiratory complications; however, the PaCO(2) and minute ventilation were increased when HMEs were compared to HHs and body temperature was lower. The cost of HMEs was lower in all studies that reported this outcome. There was some evidence that hydrophobic HMEs may reduce the risk of pneumonia and that blockages of artificial airways may be increased with the use of HMEs in certain subgroups of patients.
Authors' Conclusions:
There is little evidence of an overall difference between HMEs and HHs. However, hydrophobic HMEs may reduce the risk of pneumonia and the use of an HMEs may increase artificial airway occlusion in certain subgroups of patients. Therefore, HMEs may not be suitable for patients with limited respiratory reserve or prone to airway blockage. Further research is needed relating to hydrophobic versus hygroscopic HMEs and the use of HMEs in the pediatric and neonatal populations. As the design of HMEs evolves, evaluation of new generation HMEs will also need to be undertaken.

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:29
Mechanical Ventilation I: Indication and Settings
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...