Related Experiment Video
Updated: Jun 8, 2026


Functional Assessment of Intestinal Tight Junction Barrier and Ion Permeability in Native Tissue by Ussing Chamber Technique
Published on: May 26, 2021
Diffuse abnormal layering of small intestinal smooth muscle is present in patients with FLNA mutations and x-linked
Raj P Kapur1, Stephen P Robertson, Mark C Hannibal
1Departments of Pathology, Seattle Children's Hospital, University of Washington, WA, USA. raj.kapur@seattlechildrens.org

Abstract:
X-linked intestinal pseudo-obstruction, a rare disorder caused by mutations in FLNA, the gene encoding the cytoskeletal protein filamin A, has been regarded as a hereditary enteric neuropathy largely on the basis of sparse and incomplete pathologic studies. Diffuse abnormal layering of small intestinal smooth muscle (DAL) is a rare malformation, which has only been described in 4 patients (all male, 3 in the same family) with intestinal pseudo-obstruction. We report DAL in 5 male patients (2 families) with intestinal pseudo-obstruction and mutations in FLNA. Light microscopic, ultrastructural, and immunohistochemical studies showed abnormal lamination of the small intestinal muscularis propria with associated absent or severely reduced FLNA immunoreactivity. Intestinal samples from the oldest patient in the series, a teenager, showed multinucleate myocytes in small and large intestine, along the submucosal surface of the muscularis propria. As neither DAL nor the pattern of myocyte multinucleation observed in our patients have been described outside the context of X-linked intestinal pseudo-obstruction, these histopathologic features may be specific for this hereditary disorder and suggest an underlying myopathic basis for dysmotility in affected patients.
Insights
X-linked intestinal pseudo-obstruction, caused by FLNA gene mutations, is linked to diffuse abnormal smooth muscle layering in the intestine. This study suggests a myopathic basis for the disorder, not just a neuropathy.
Area of Science:
- Gastroenterology
- Genetics
- Pathology
Background:
- X-linked intestinal pseudo-obstruction is a rare disorder linked to FLNA gene mutations.
- Previous studies suggested it's primarily a hereditary enteric neuropathy.
- Diffuse abnormal layering of small intestinal smooth muscle (DAL) has been rarely described in this condition.
Purpose of the Study:
- To investigate the histopathologic features of X-linked intestinal pseudo-obstruction.
- To determine if DAL and myocyte multinucleation are specific to this disorder.
- To explore the underlying basis of intestinal dysmotility in affected patients.
Main Methods:
- Light microscopy, ultrastructural analysis, and immunohistochemistry were used on intestinal samples.
- Histopathologic features of DAL and FLNA expression were examined.
- Clinical and genetic data from affected patients were analyzed.
Main Results:
- DAL was identified in 5 male patients from 2 families with intestinal pseudo-obstruction and FLNA mutations.
- Abnormal lamination of the small intestinal muscularis propria with reduced FLNA immunoreactivity was observed.
- Multinucleate myocytes were found in the intestinal samples of the oldest patient.
Conclusions:
- DAL and myocyte multinucleation appear to be specific histopathologic features of X-linked intestinal pseudo-obstruction.
- These findings suggest an underlying myopathic cause for intestinal dysmotility in this condition.
- This study reframes the understanding of X-linked intestinal pseudo-obstruction from a neuropathy to a myopathy.


Related Concept Videos
 01:26
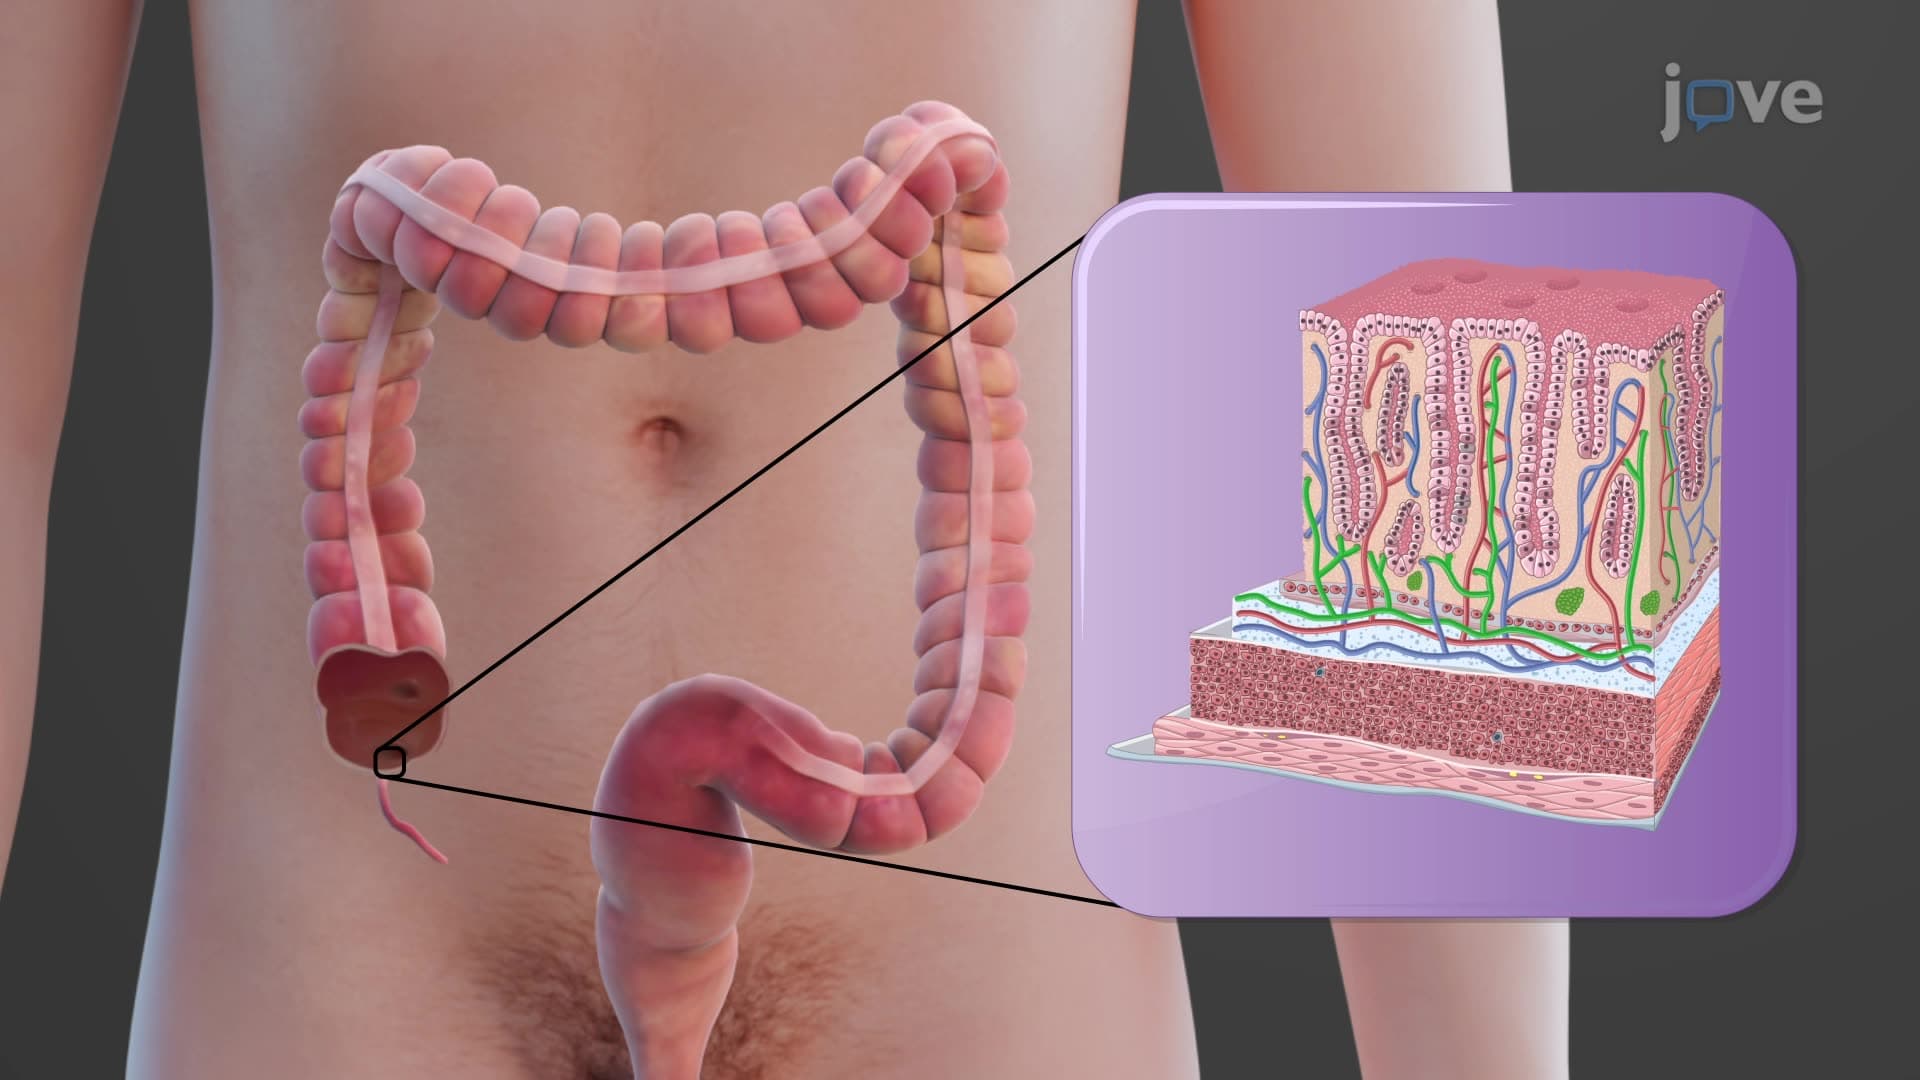
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
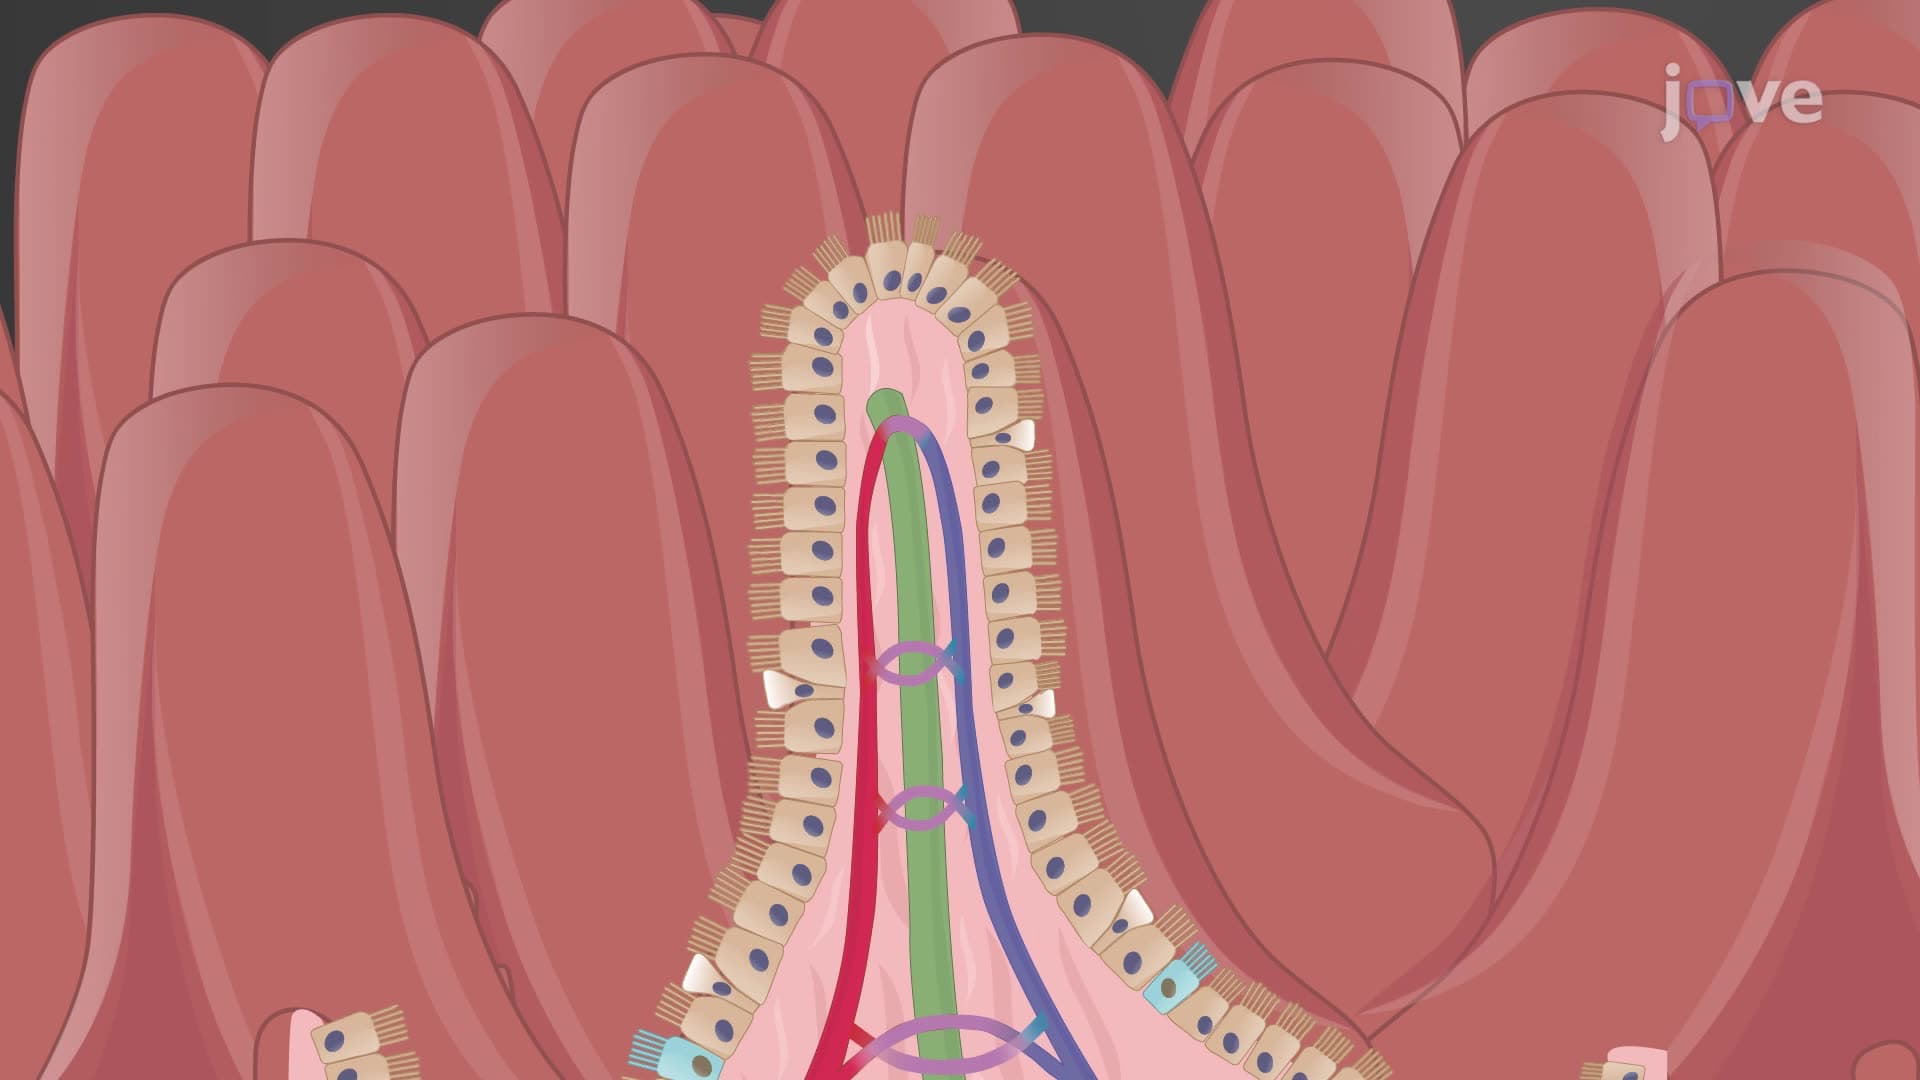
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:29
Intestinal Obstruction I: Introduction
 01:23
Renewal of Intestinal Stem Cells
 01:07
Intestinal Obstruction II: Pathophysiology
 01:20
Histology of the Gastrointestinal (GI) Tract
The mucosa is sometimes called a mucous membrane due to its mucus-secreting features. This membrane is composed of epithelium, which directly interacts with ingested substances, and the lamina propria, a layer...