Related Experiment Video
Updated: Jun 8, 2026
Characterizing Modulators of Protease-Activated Receptors with a Calcium Mobilization Assay Using a Plate Reader
Published on: May 24, 2024
Prostanoid and TP-receptors in atherothrombosis: is there a role for their antagonism?
Chiara Giannarelli1, M Urooj Zafar, Juan J Badimon
1AtheroThrombosis Research Unit, Cardiovascular Institute, Mount Sinai School of Medicine, New York, New York 10029, USA.

Insights
Inhibiting thromboxane A2/prostaglandin (TP) receptors offers anti-platelet and anti-atherosclerotic benefits. TP-receptor blockade reduces plaque burden and stabilizes plaques, showing promise for conditions like diabetes.
Area of Science:
- Cardiovascular Research
- Pharmacology
- Atherosclerosis Pathophysiology
Background:
- Atherosclerosis and its complications (myocardial infarction, stroke) are leading causes of death.
- Endothelial dysfunction initiates the cascade of coronary events.
- Thromboxane A2/prostaglandin (TP) receptors are implicated in platelet function, endothelial dysfunction, and inflammation in atherosclerosis.
Purpose of the Study:
- To investigate the role of TP-receptor inhibition beyond anti-platelet effects.
- To explore the impact of TP-receptor blockade on endothelial dysfunction and the inflammatory aspects of atherosclerosis.
- To assess the anti-atherosclerotic and plaque-stabilizing potential of TP-receptor inhibitors.
Main Methods:
- Review of pre-clinical evidence on TP-receptor involvement in atherothrombosis.
- Analysis of prostanoid synthesis and action in endothelial cells and macrophages.
- Evaluation of TP-receptor blockade effects on atherosclerotic plaque characteristics in models.
Main Results:
- Prostanoids (TxA2, F2-isoprostanes, PGG2/PGH2) promote atherosclerosis via platelet activation, leukocyte-endothelial interactions, and vasoconstriction.
- Dysfunctional endothelium and plaque macrophages contribute to prostanoid production, driving plaque progression.
- TP-receptor inhibition demonstrated anti-atherosclerotic effects, reducing plaque burden and stabilizing plaques by decreasing macrophages and increasing smooth muscle cells.
Conclusions:
- TP-receptor blockade exhibits both anti-platelet and anti-atherosclerotic effects.
- Selective TP-receptor inhibitors may offer therapeutic benefits in stabilizing atherosclerotic plaques.
- Combining anti-platelet and anti-atherosclerotic actions via TP-receptor inhibition is promising, especially for prostanoid-rich conditions like diabetes.
Abstract:
Atherosclerosis and its clinical manifestations (i.e. myocardial infarction, stroke) are major causes of mortality and morbidity in Western countries. Endothelial dysfunction is considered the first step in the cascade leading up to coronary events. Increasing evidence suggests that direct inhibition of thromboxane A2/prostaglandin (TP)-receptors may not only have anti-platelet effects but also impact endothelial dysfunction as well as inflammatory component of atherosclerosis. While TP-receptor involvement in platelet function has received the greatest attention, more recent findings support the critical role of TP-receptor in other pathophysiological aspects of atherothrombosis. Prostanoids (i.e. TxA2, F2-isoprostanes, prostaglandins endoperoxides PGG2/PGH2) are known to promote the initiation and progression of atherosclerosis, not only via platelet activation, but through leukocyte-endothelial interactions and vasoconstriction. Dysfunctional endothelium, characterised by increased COX-activity, releases prostanoids that promote endothelial exposure to adhesion molecules and induce smooth muscle cell contraction. Plaque macrophages synthesise PGH2/PGG2 via COX-2; these potent prostanoids can trigger platelet activation and aggregation despite COX-1 inhibition by aspirin. TP-receptor inhibition has been reported to exert anti-atherosclerotic effects in pre-clinical model of disease. Reduction of plaque burden was associated with plaque stabilisation documented by the reduction in the content of macrophages, apoptotic cells, MMPs and endothelin-1, and the increase in smooth muscle cells content. TP-receptor blockade might have an anti-atherosclerotic and plaque stabilisation effect. The possibility of combining anti-platelet activity with an anti-atherosclerotic effect via selective TP-receptor inhibitors could have important implications especially in clinical conditions associated with increased production of prostanoids, such as diabetes.

Related Concept Videos
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:18
Treatment for Pulmonary Arterial Hypertension: Endothelin Receptor Antagonists
ETs are synthesized through a complex sequence of enzymatic steps, primarily involving an enzyme referred to as endothelin-converting enzyme (ECE). Of...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:30
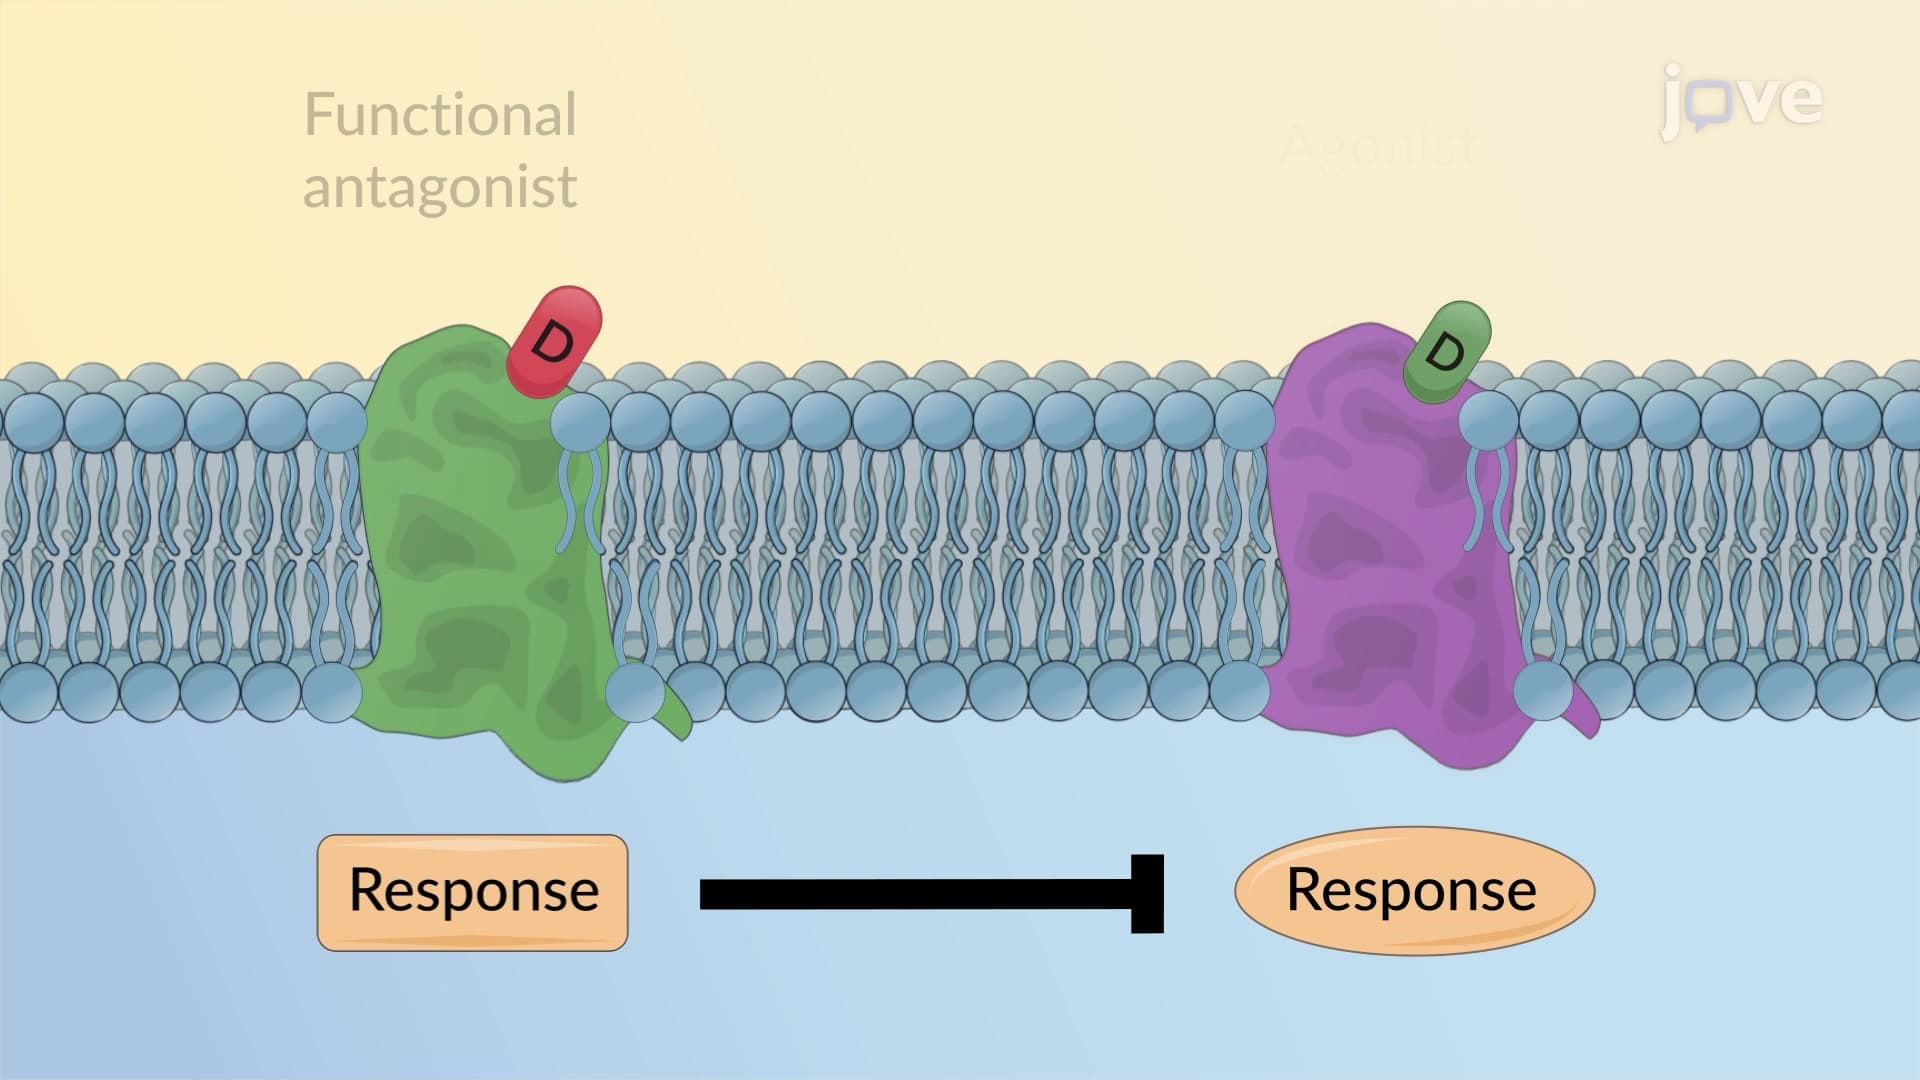
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins