Related Experiment Video
Updated: Jun 8, 2026


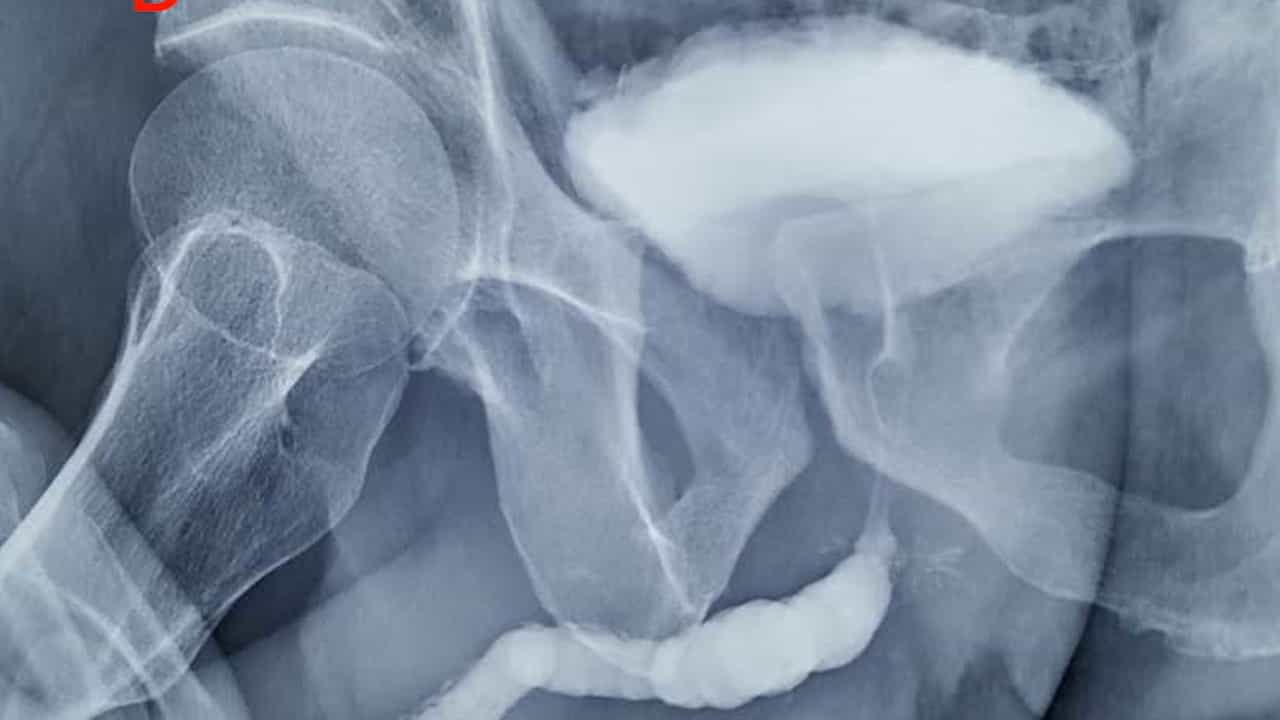
Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Prognosis of urethral strictures following pelvic fracture urethral distraction defects--a single centre study
Rajkumar Mathur1, Gaurav Aggarwal, Bhaskar Satsangi
1Department of Surgery, M.G.M Medical College & M.Y.H group of Hospitals, Indore, Madhya Pradesh 452001, India. rkmmyh60@yahoo.com

Insights
Pelvic trauma significantly impacts urethral stricture outcomes. The type and management of pelvic fractures, classified by TILE grading, influence surgical success rates and complications, highlighting the need for tailored treatment approaches.
Area of Science:
- Urology
- Trauma Surgery
- Reconstructive Surgery
Background:
- Urethral strictures present a significant reconstructive challenge with high recurrence rates.
- Pelvic trauma is a primary cause of urethral strictures, leading to considerable morbidity.
- The relationship between pelvic trauma characteristics and stricture outcomes requires further elucidation.
Purpose of the Study:
- To investigate the cause-effect relationship between pelvic trauma and urethral stricture outcomes.
- To assess the influence of pelvic fracture type, degree, and primary management on urethral stricture prognosis.
- To enhance understanding of contemporary urethral stricture management.
Main Methods:
- 163 male patients with urethral strictures secondary to pelvic trauma were evaluated.
- Preoperative assessments included retrograde urethrography, urethrosonography, and uroflowmetry.
- Pelvic radiographs were used to classify fractures using the TILE system (Grades A, B, C); patients underwent urethroplasty 6 weeks later.
Main Results:
- 80 patients were TILE Grade A, 55 Grade B, and 28 Grade C.
- The most frequent stricture location was the membranous urethra.
- Success rates were 96-98% at 1 year, declining to 93% at 2 years; TILE A and B showed better outcomes than C. Overall complication rate was 20.25%.
Conclusions:
- The type and management of pelvic fractures significantly impact urethral stricture prognosis.
- These factors are crucial for improving outcomes in reconstructive surgery for urethral strictures.
- Further research is needed to fully understand and address the "cause-effect" relationship in these complex cases.
Introduction:
Urethral strictures remain a reconstructive dilemma due to high incidence of recurrence and unsatisfactory outcomes. Pelvic trauma remains the foremost etiology leading to morbidity. We evaluated this "cause-effect" relationship of pelvic trauma to stricture outcome, to replenish our understanding of contemporary urethral strictures and highlight significance of type, degree and influence of primary management of pelvic trauma on the overall prognosis of urethral strictures.
Materials And Method:
163 male patients with urethral strictures, primary etiology being pelvic trauma, were assessed preoperatively followed by retrograde urethrogram, urethrosonogram, uroflowmetry, and then subjected to pelvic radiographs to identify presence and type of pelvic fracture, and further sub-categorize them into grades A, B and C, of TILE classification. Thereafter, 6 weeks later, these patients underwent urethroplasty.
Results:
Of 163 patients having pelvic trauma, 80 fell under category A of TILE grading, whereas 55 were under TILE B and 28 under TILE C. Most common stricture location was membranous urethra. Success rates were 96-98% till 1 year follow up, but after two years, they declined to 93%. TILE A and B had a better post operative course as compared to TILE C. Overall complication rate was 20.25%.
Conclusion:
The magnitude of the impact of the type of pelvic fracture and its management has remained unexplored. Our representative study enunciates that these parameters play a vital role in the overall prognosis of urethral strictures and command due importance, to bridge the rift in this "cause-effect" relationship.
Related Concept Videos
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:30
Urinary Tract Calculi III: Medical Management