Related Experiment Video
Updated: Jun 8, 2026
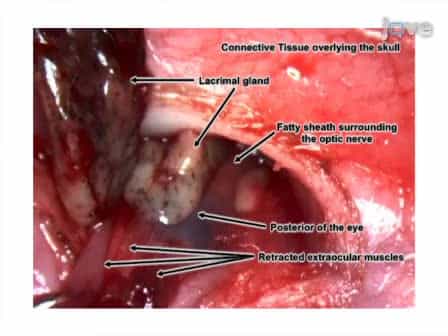

Optic Nerve Transection: A Model of Adult Neuron Apoptosis in the Central Nervous System
Published on: May 12, 2011
[Inferior nasal transposition of the lateral rectus muscle for third nerve palsy]
1Klinik und Poliklinik für Augenheilkunde, Universitätsklinikum Gießen und Marburg, Standort Gießen. michael.h.graef@augen.med.uni-giessen.de

Objective:
The choice and extent of extraocular muscle surgery in N.III palsy are based on the specific pattern and degree of the palsy. In severe paralysis the eye has to be shifted from an exotropic to a straight ahead position. Additionally, a change in vertical position may be desirable. To reach this aim, transposition of the integral lateral rectus muscle to the nasal hemisphere of the eye was performed in 3 patients.
Patients And Method:
Patient #1 (50 y, m) had vertical gaze palsy and N.III palsy RE with 35° exo-, 25° hyper- and 9° incyclotropia. Patient #2 (41 y, m) had vertical gaze palsy and asymmetric bilateral N.III palsy. The RE was 35°exo-, 8° hyper- and 8° incyclotropic. Adduction was limited to the sagittal plane in both patients. Patient #3 (61 y, f) had vertical gaze palsy together with bilateral N.III paralysis. The eyes were immobile. The RE was 40° abducted and blind. The LE was in 40° abduction. The patient could hardly use this eye for everyday demands. In all 3 patients, the lateral rectus muscle was transposed between the inferior rectus muscle and the globe to the lower margin of the medial rectus muscle, passing behind the inferior oblique muscle. During general anaesthesia, the location of the attachment site from the corneal limbus was determined such that the eye was moved into the desired position.
Results:
In all patients, the resulting eye position was slightly below primary position. As expected, incyclotropia had increased. Patient #1 had a residual deviation of 2° exo-, 9° hypo-, and 17° incyclotropia. Horizontal motility of the RE ranged from 5° adduction to 5° abduction. As a second side effect, depression occurred on attempted abduction. Patient #2 had no horizontal deviation, but 10° hypo- and 25° incyclotropia. Horizontal motility of the RE ranged from 0° to 5° adduction. Patient #3 could use her eye in a nearly straight ahead position in slight down gaze. Her RE was still 15° exotropic. These results remained stable after 18, 12 and 10 months, respectively. None of the patients was disturbed any more by either confusion or diplopia or image tilt.
Conclusions:
Transposition of the entire lateral rectus muscle to the nasal hemisphere is an efficient method to correct for exotropia associated with vertical deviation in specific cases of N.III palsy. The cyclotorsional effect of the procedure has to be considered. The vertical effect is useful to correct for hypertropia and induce a durable, slightly depressed eye position which is profitable for monocular visual demands and aesthetically appealing.
More Related Videos
 13:12
Partial Optic Nerve Transection in Rats: A Model Established with a New Operative Approach to Assess Secondary Degeneration of Retinal Ganglion Cells
Published on: October 15, 2017
 19:53
Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
Related Concept Videos
 01:20
Muscles of the Eye
Extraocular Muscles
The six extraocular muscles surround the eyeball and control its movements. They are responsible for a wide range of eye motions, including looking up, down, left, right, and rotating...
 01:17
Accessory Structures of the Eye
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...