Related Experiment Video
Updated: Jun 8, 2026

Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Acute ischemic stroke therapy
Nils Henninger1, Rajat Kumar, Marc Fisher
1Department of Neurology, University of Massachusetts Medical Center, 55 Lake Avenue, North Worcester, MA 01655, USA. nils.henninger@umassmemorial.org

Abstract:
Data from the European Cooperative Acute Stroke Study (ECASS) III trial demonstrated that tissue plasminogen activator given up to 4.5 h after stroke onset improves outcome and treatment guidelines support its use during this time window. Intra-arterial therapy with tissue plasminogen activator or devices is commonly used at large tertiary centers up to 6–8 h after stroke onset, but conclusive evidence of efficacy remains lacking. During the acute phase after stroke onset, blood pressure elevations should be reduced as should substantial elevations in blood glucose. Statins are recommended in essentially all non-cardioembolic stroke patients. The most important future directions for acute stroke therapy are to extend the therapeutic time window and to increase the proportion of patients treated within the currently documented 4.5-h time window. Imaging-guided selection of appropriate patients will likely be a key factor for extending the therapeutic time window and both diffusion/perfusion MRI and perfusion computed tomography will be useful imaging modalities in this effort.

Related Concept Videos
 01:15
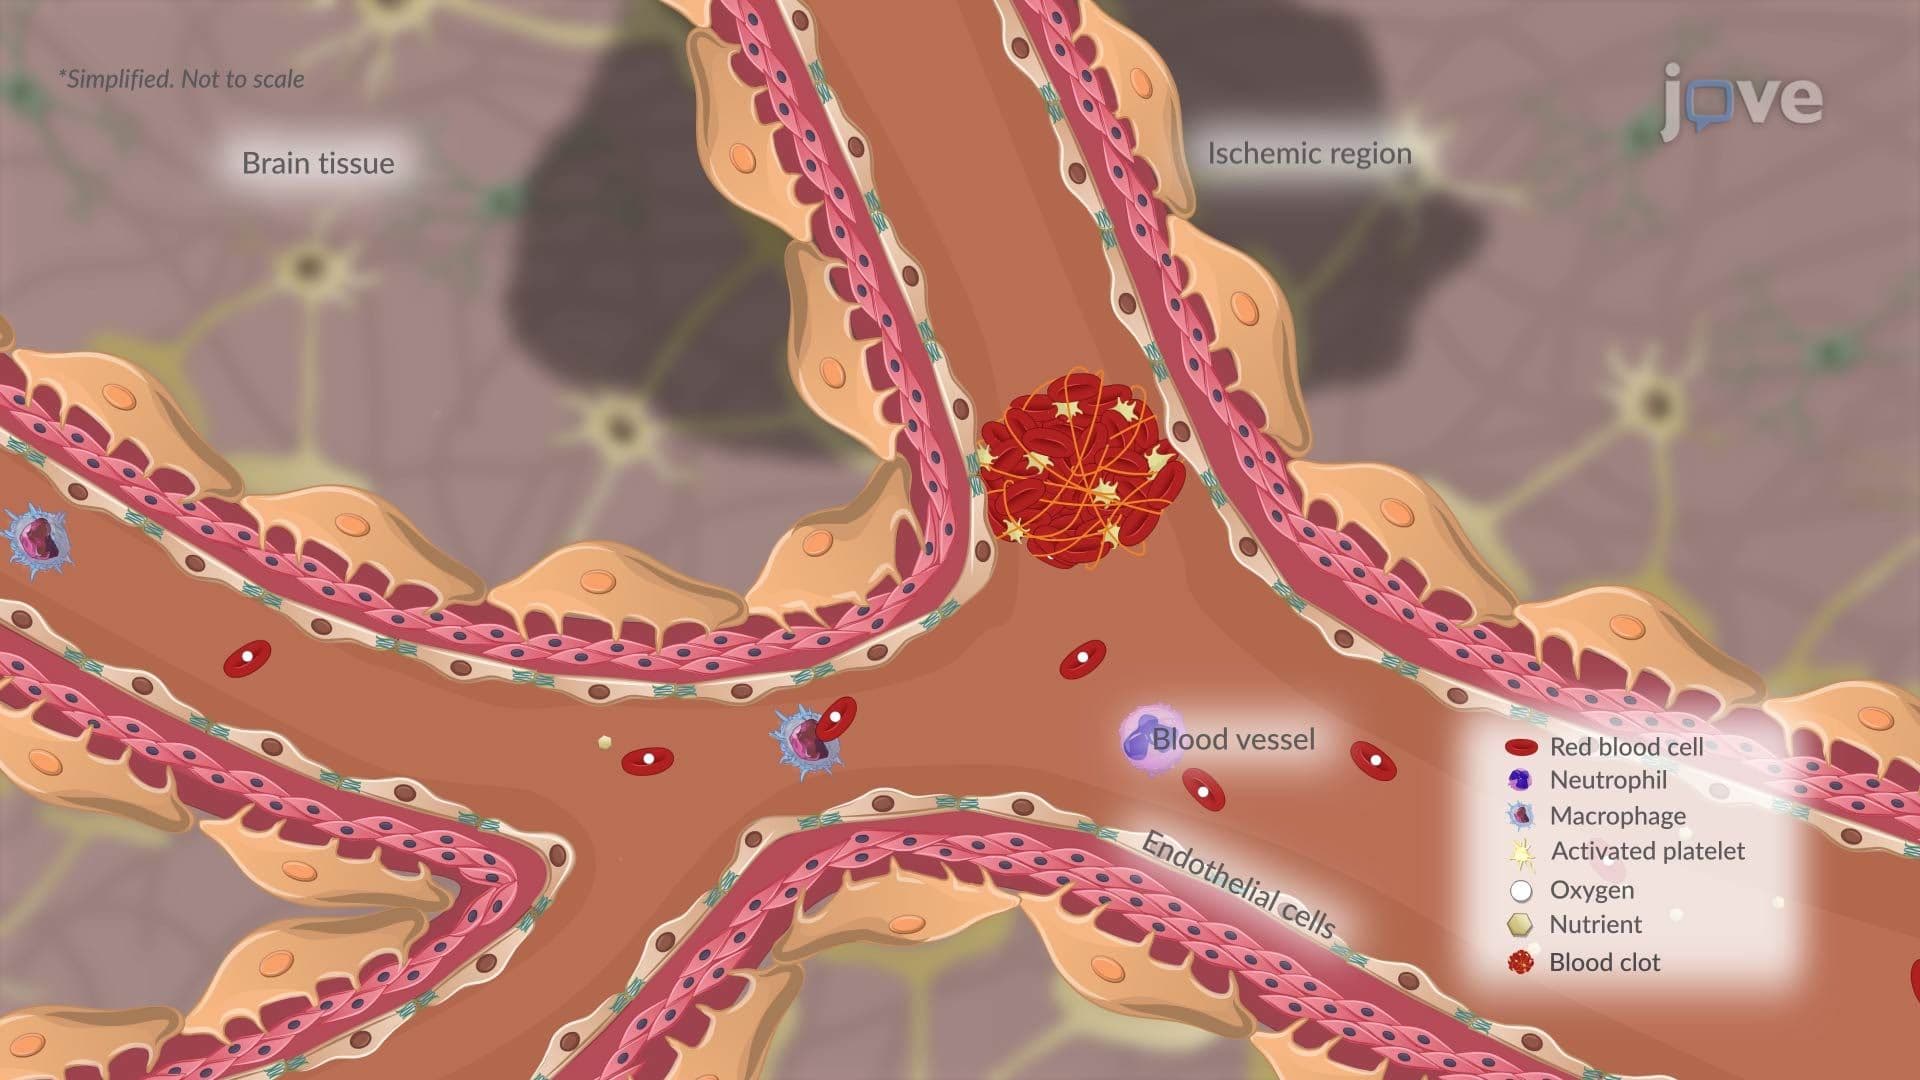
Ischemic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke l: Introduction
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Transient Ischemic Attack l: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:29
Hemorrhagic Stroke ll: Pathophysiology