Related Experiment Video
Updated: Jun 8, 2026


Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Hyperostosing meningiomas of the cranial vault with and without tumor mass
Andrea Talacchi1, Francesco Corsini, Massimo Gerosa
1Department of Neurological Sciences and Vision, Section of Neurosurgery, University of Verona, P. Stefani 1, 37126 Verona, Italy. andrea.talacchi@univr.it

Objective:
This study represents the first clinical series in the reported literature exclusively concentrating on the clinicoradiological features of non-sphenoidal hyperostosing meningiomas. It attempts to identify the factors that may have an impact on the surgical strategy and results of this unique subgroup of meningiomas.
Methods:
In the vault, we distinguished between meningiomas with and without tumor mass according to their thickness (<1.5 vs ≥ 1.5 cm) and between convexity (lateral) and calvarial (midline) meningiomas according to their location. The clinical, radiological, surgical and prognostic characteristics of the tumors were examined.
Results:
Over a 10-year period, we observed 24 cases, 18 of which in the convexity (nine without and nine with tumor mass) and six calvarial (one without and five with tumor mass). Six patients presented with neurological signs, while the majority showed bony hyperostosis (n = 19). Brain edema (n = 7) was found only in cases with tumor mass, in all neurologically impaired patients, and only in one intact patient. Total removal was obtained in 92% patients. Small residual tumors attached to the superior sagittal sinus and perisinusal dura were coagulated in situ and not excised. Morbidity occurred in three symptomatic patients with tumor mass and brain edema (mental confusion in one case and hemiparesis in two cases). Mortality was nil. After a mean follow-up of 4.8 years, three cases relapsed, all of which had initially presented with atypical meningiomas.
Conclusions:
The rare hyperostosing cranial vault meningiomas may be classified as being with and without tumor mass. A number of categorical differences exist in their distribution, pattern of hyperostosis, surrounding arachnoidal plane, and their prognosis. Careful preoperative planning aimed at tailoring the extent of tumor removal and reconstruction in the neighboring infiltrated structures enables a good outcome to be achieved.


Related Concept Videos
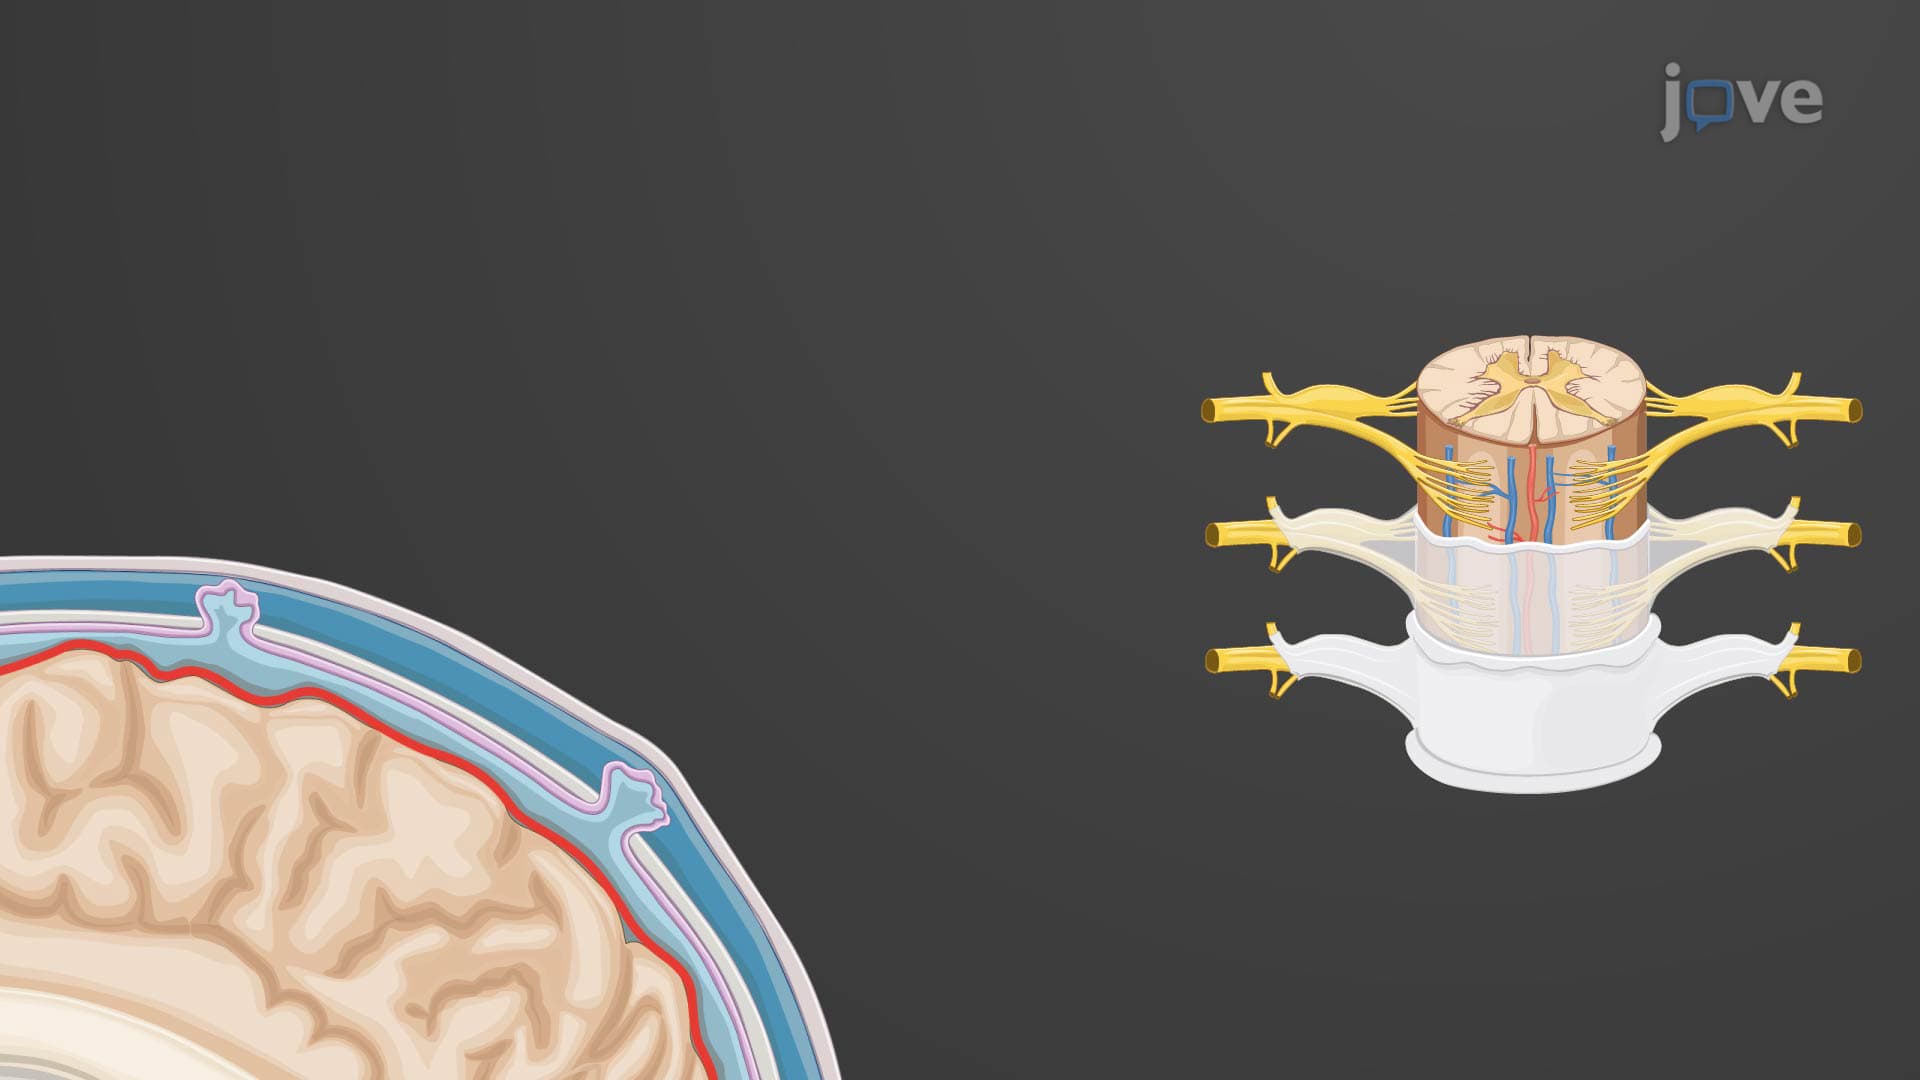 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...
 01:27
Cryptococcal Meningitis
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...