Related Experiment Video
Updated: Jun 7, 2026
10:10

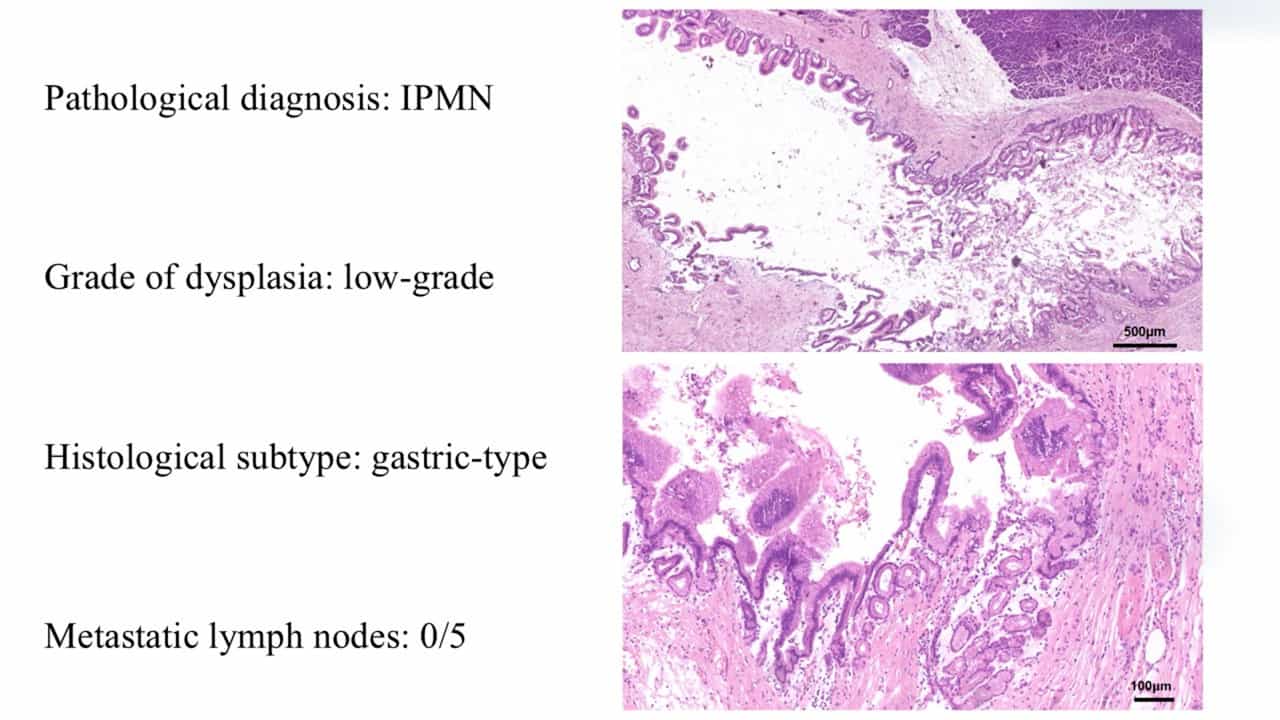
Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Megaduodenum secondary to an intrinsic duodenal diaphragm; report of case
The American Journal of Roentgenology and Radium Therapy
|October 29, 2010

Abstract
No abstract available in PubMed .
Keywords:
DUODENUM/diaphragm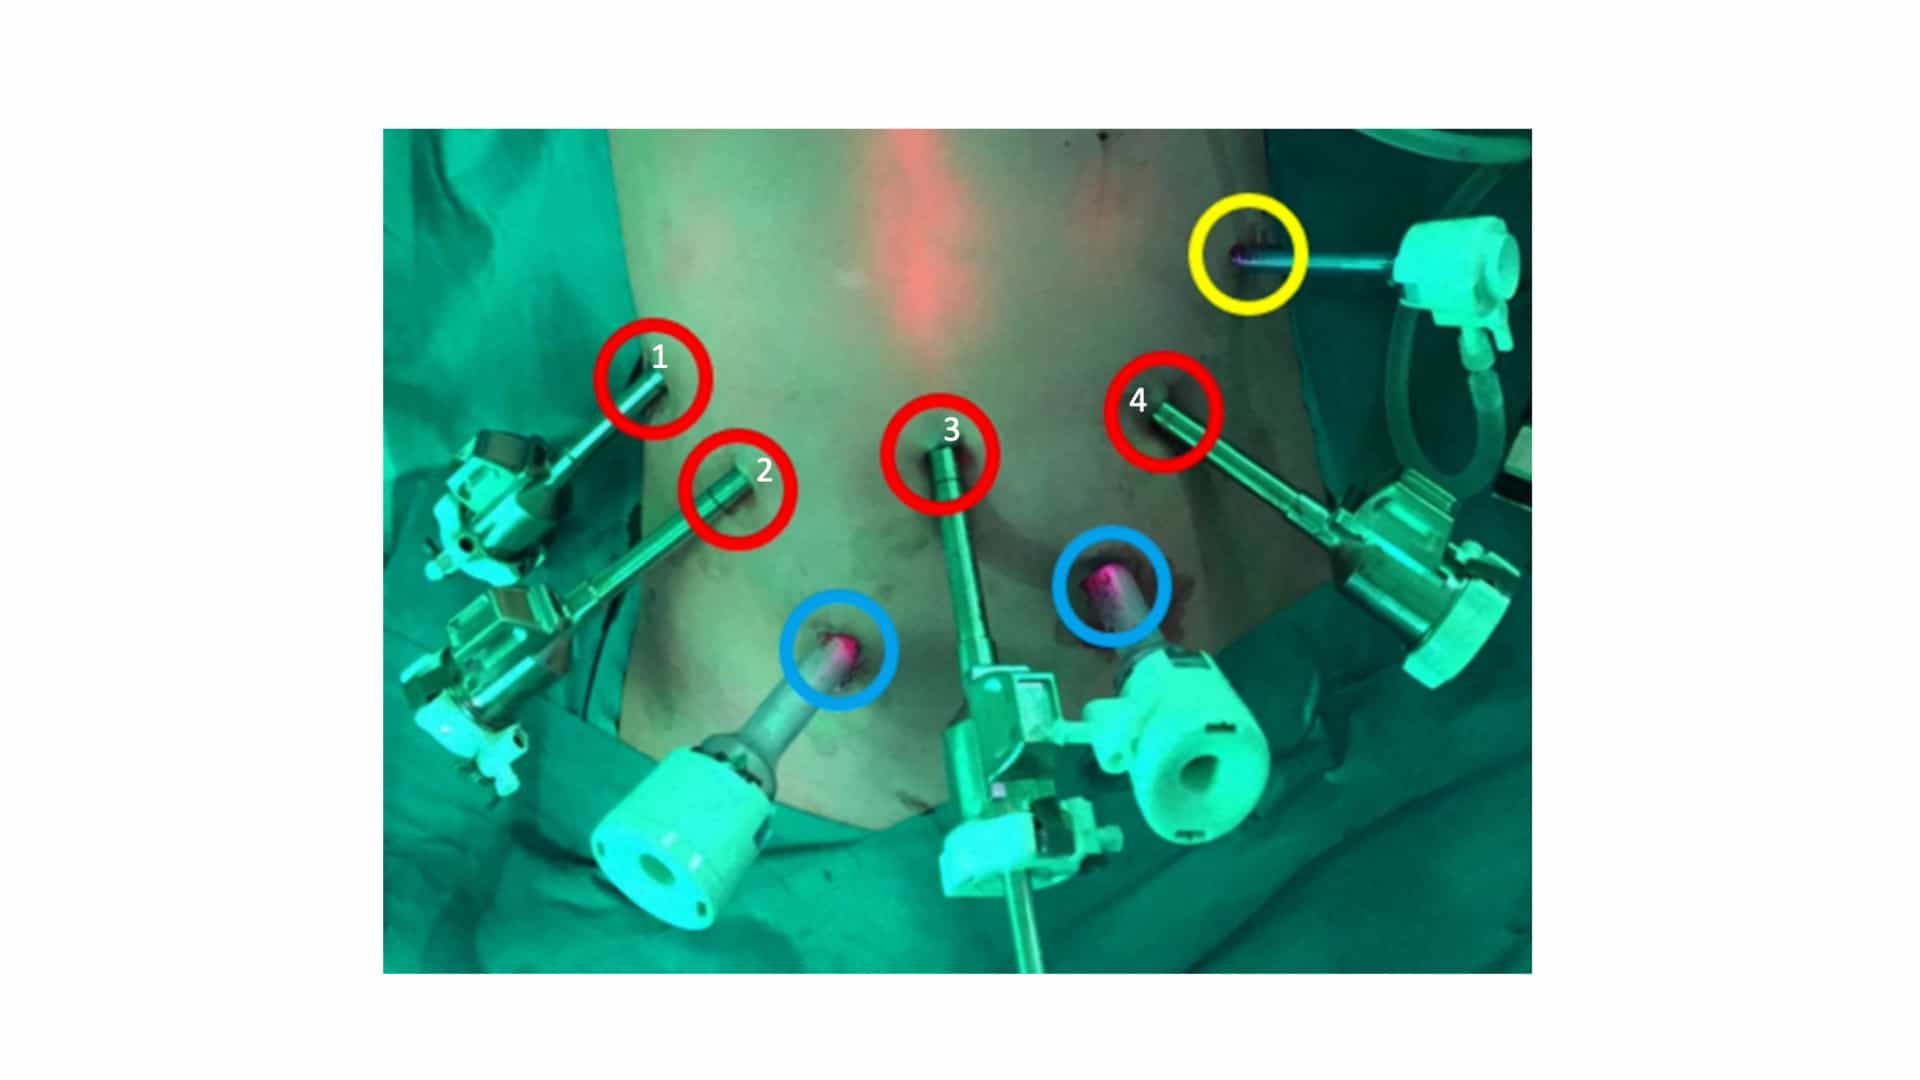
Related Concept Videos
 01:07
Intestinal Obstruction II: Pathophysiology
Intestinal obstruction triggers a series of physiological responses, starting with gas and fluid accumulation in the bowel segment proximal to the obstruction, leading to distension. This distended intestine compresses the diaphragm, hindering lung expansion and potentially leading to reduced respiratory effort, atelectasis, and pneumonia.To overcome the blockage, the gut intensifies contractions, causing colicky abdominal pain, nausea, and vomiting, which reduces fluid and food intake and...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
Duodenal UlcersDuodenal ulcers are the most common form of peptic ulcer disease, presenting with chronic, intermittent epigastric pain. Pain typically appears 2–3 hours after meals, especially when the stomach is empty, often waking patients at night. It is characteristically relieved by food or antacids (“pain–food–relief”). Some patients remain asymptomatic until complications like bleeding or perforation emerge, particularly with NSAID or anticoagulant use.Gastric UlcersGastric ulcers share...
 01:27
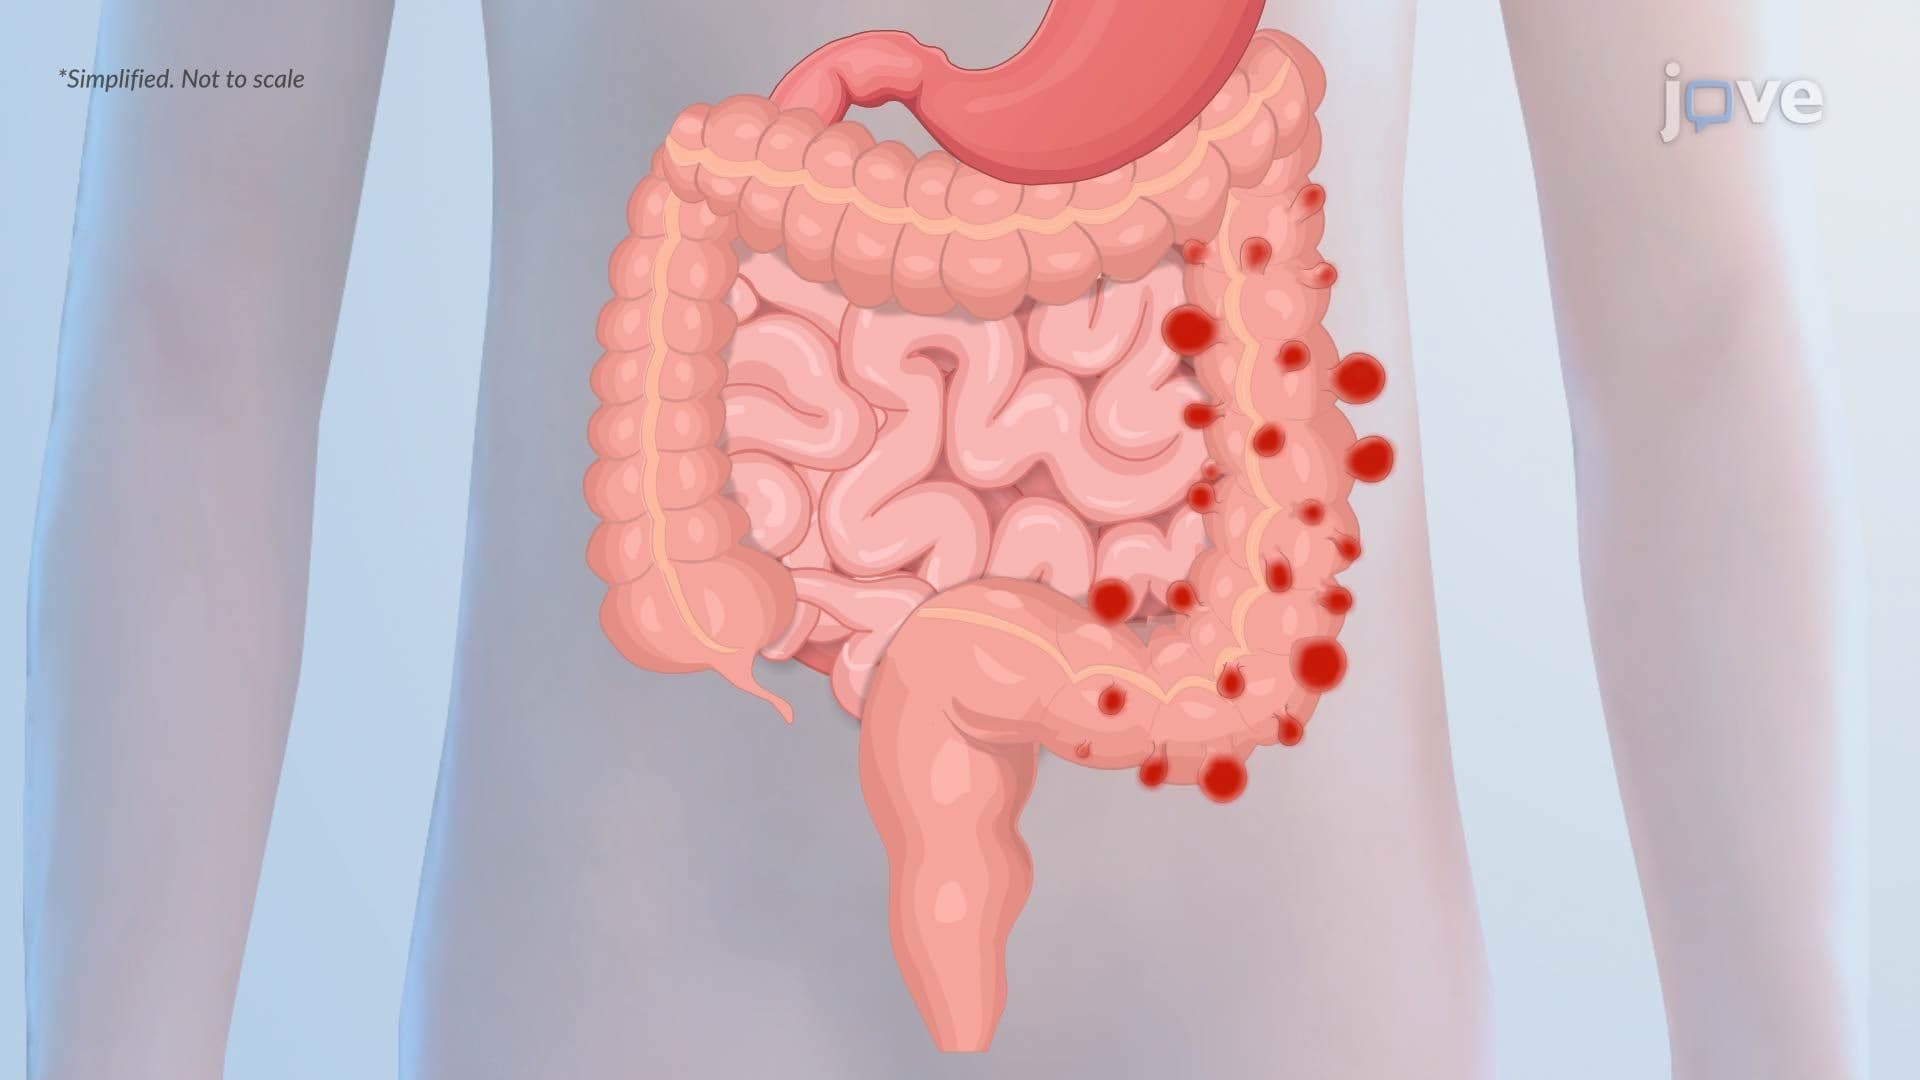
Diverticular Disease of the Colon
Diverticular disease involves the formation of diverticula—small sac-like outpouchings of the colonic wall—and their complications. It most commonly affects the sigmoid colon due to higher intraluminal pressure and structural vulnerability. It results from structural weakness and increased pressure in the colon, producing pseudodiverticula that may remain silent or progress to inflammation and serious complications.Structure of DiverticulaIn diverticulosis, these outpouchings are...
 01:24
Peptic Ulcer Disease II: Pathophysiology
Peptic ulcer disease develops when protective mechanisms of the gastrointestinal mucosa are overwhelmed by harmful factors, leading to localized erosions in the stomach or proximal duodenum. The main causes are Helicobacter pylori infection and chronic use of nonsteroidal anti-inflammatory drugs (NSAIDs).Helicobacter pylori–Induced InjuryBacterial Adaptation and Colonization:H. pylori is a spiral, Gram-negative bacterium adapted to the acidic stomach. and transmitted through oral-oral or...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Peptic Ulcer Disease (PUD) is characterized by the development of ulcers in the stomach or duodenal mucosa. Its pathophysiology is complex, involving a balance between damaging and protective elements.
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Peptic ulcer disease (PUD) presents with diverse symptoms depending on the location and severity of the ulcer. Clinical manifestations of peptic ulcer include dull pain and a burning sensation in the mid-epigastric region.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.