Related Experiment Video
Updated: Aug 6, 2026
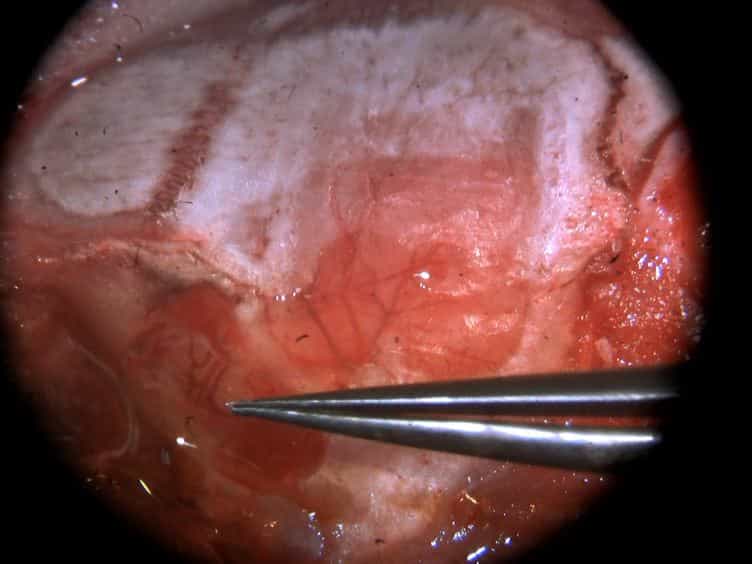

Permanent Cerebral Vessel Occlusion via Double Ligature and Transection
Published on: July 21, 2013
Extracranial-intracranial bypass to reduce the risk of ischemic stroke
1Agency for Health Care Policy and Research (AHCPR), Center for Research Dissemination and Liaison, Rockville, MD 20857.

Insights
Extracranial-intracranial bypass surgery (EC-IC) shows insufficient evidence of reduced stroke rates compared to other treatments. A controlled trial found no benefit, making it the best available evidence for stroke prevention.
Area of Science:
- Neurosurgery
- Vascular Surgery
- Neurology
Background:
- Extracranial-intracranial (EC-IC) bypass surgery connects the superficial temporal artery to the middle cerebral artery.
- This procedure was developed to address atherosclerotic lesions in the internal carotid or middle cerebral arteries.
- The EC-IC bypass was first described in 1969.
Purpose of the Study:
- To compare the outcomes of EC-IC bypass surgery from multiple surgical series with a prospective, randomized, cooperative trial.
- To evaluate the efficacy of EC-IC bypass in reducing stroke rates.
Main Methods:
- Comparative analysis of 13 surgical series (1,464 patients) reporting EC-IC bypass outcomes.
- Comparison with data from a single prospective, randomized, cooperative trial (1,377 patients).
Main Results:
- Analysis of the 1,464 patients in surgical series yielded insufficient evidence to conclude lower post-EC-IC bypass stroke rates.
- Stroke rates in EC-IC bypass patients were not demonstrably lower than medically or surgically treated groups in the controlled trial.
Conclusions:
- There is a lack of reliable evidence supporting the superiority of EC-IC bypass surgery over medical treatment for stroke reduction.
- The results of the controlled clinical trial, showing no benefit from EC-IC bypass, represent the best current evidence.
Abstract:
Extracranial-intracranial bypass surgery is an operative procedure in which the superficial temporal artery is anastomosed to the middle cerebral artery. The operation, first described in 1969, was employed to circumvent otherwise surgically inaccessible atherosclerotic lesions high in the internal carotid system or in the middle cerebral artery. This assessment compares the findings from 13 surgical series of EC-IC (1,464 patients) with those reported in the only prospective, randomized, cooperative trial of this procedure (1,377 patients). Analysis of the outcomes in the 1,464 patients included in the surgical series produced insufficient evidence to support a conclusion that post-EC-IC bypass stroke rates were lower than the rates of either the medically or surgically treated groups in the controlled clinical trial. In the absence of reliable, objective evidence of the existence of a group of patients in whom surgical intervention is superior to medical treatment in reducing the frequency of stroke, the results of the single controlled clinical trial, which demonstrated no benefit of bypass, must be accepted as the best evidence currently available.

Related Concept Videos
 01:15
Ischemic Stroke l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology