Related Experiment Video
Updated: Jun 7, 2026


Noninvasive Sampling of Mucosal Lining Fluid for the Quantification of In Vivo Upper Airway Immune-mediator Levels
Published on: August 7, 2017
Residential air pollution and otitis media during the first two years of life
Elaina A MacIntyre1, Catherine J Karr, Mieke Koehoorn
1School of Environmental Health, University of British Columbia, Vancouver, British Columbia, Canada. elaina1@interchange.ubc.ca

Insights
Childhood otitis media, a common reason for doctor visits, is linked to air pollution. Exposure to nitrogen oxides (NO) and woodsmoke increases the risk of middle ear infections in young children.
Area of Science:
- Environmental Health
- Pediatrics
- Epidemiology
Background:
- Otitis media is a primary cause of antibiotic prescriptions and physician visits among young children.
- Investigating environmental factors like air pollution is crucial for understanding otitis media prevalence.
Purpose of the Study:
- To assess the impact of ambient air pollution on outpatient physician visits for otitis media.
- To analyze this relationship within a population-based birth cohort.
Main Methods:
- A cohort of 45,513 children born in 1999-2000 in British Columbia was followed to age 2.
- Air pollution exposure (CO, NO, NO2, O3, PM2.5, PM10, SO2, black carbon, woodsmoke) was estimated using monitor data, land-use regression, and proximity data.
- Generalized estimating equations were used to link physician visits for otitis media with prior pollutant exposure.
Main Results:
- 42% of children experienced at least one physician visit for otitis media.
- Elevated risks were associated with nitrogen oxides (NO) and woodsmoke exposure.
- Specific pollutants like PM10 and black carbon did not show increased risk for otitis media.
Conclusions:
- A modest but consistent association exists between certain air pollutants and otitis media in children.
- Findings highlight the potential role of air quality in pediatric middle ear infections, even at lower pollution levels.
Background:
: Otitis media is the leading reason young children receive antibiotics or visit a physician. We evaluated the impact of ambient air pollution on outpatient physician visits for otitis media in a population-based birth cohort.
Methods:
: All children born in southwestern British Columbia during 1999-2000 were followed until the age of 2 years. Residential air pollution exposures were estimated for the first 24 months of life by inverse-distance weighting of monitor data (CO, NO, NO2, O3, PM2.5, PM10, SO2), temporally adjusted land-use regression models (NO, NO2, PM2.5, black carbon, woodsmoke), and proximity to roads and point sources. We used generalized estimating equations to longitudinally assess the relationship between physician visits for otitis media (ICD-9) and average pollutant exposure in the 2 months prior to the visit, after adjustment for covariates.
Results:
: Complete exposure and risk-factor data were available for 45,513 children (76% of all births). A total of 42% of subjects had 1 or more physician visits for otitis media during follow-up. Adjusted estimates for NO, PM2.5, and woodsmoke were consistently elevated (eg, relative risk of 1.10 [95% confidence interval = 1.07-1.12] per interquartile range [IQR] increase in NO; 1.32 [1.27-1.36] per IQR increase in days of woodsmoke exposure). No increased risks were observed for the remaining pollutants (eg, 1.00 [0.98-1.03] per IQR increase in PM10; 0.99 [0.97-1.01] per IQR increase in black carbon).
Conclusions:
: Modest but consistent associations were found between some measures of air pollution and otitis media in a large birth cohort exposed to relatively low levels of ambient air pollution.
Related Concept Videos
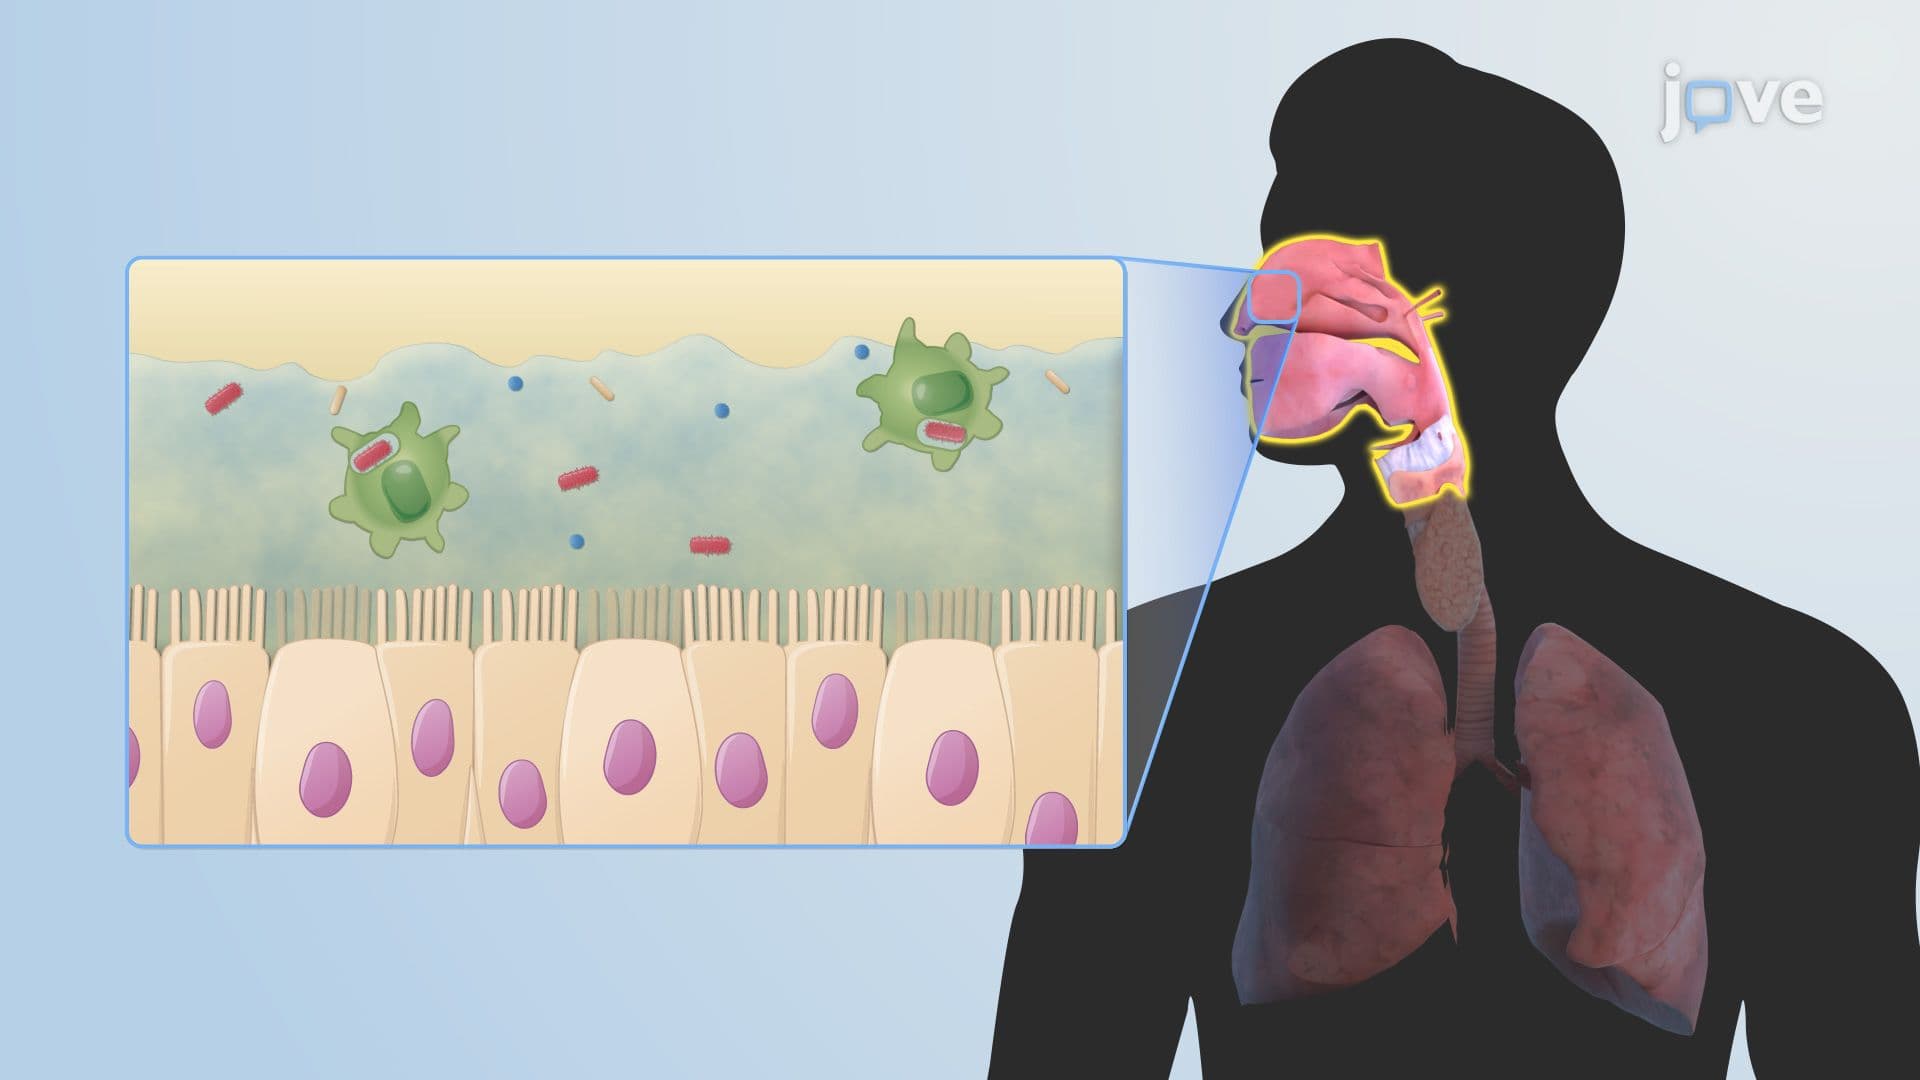 01:29
Microbiota of the Respiratory Tract
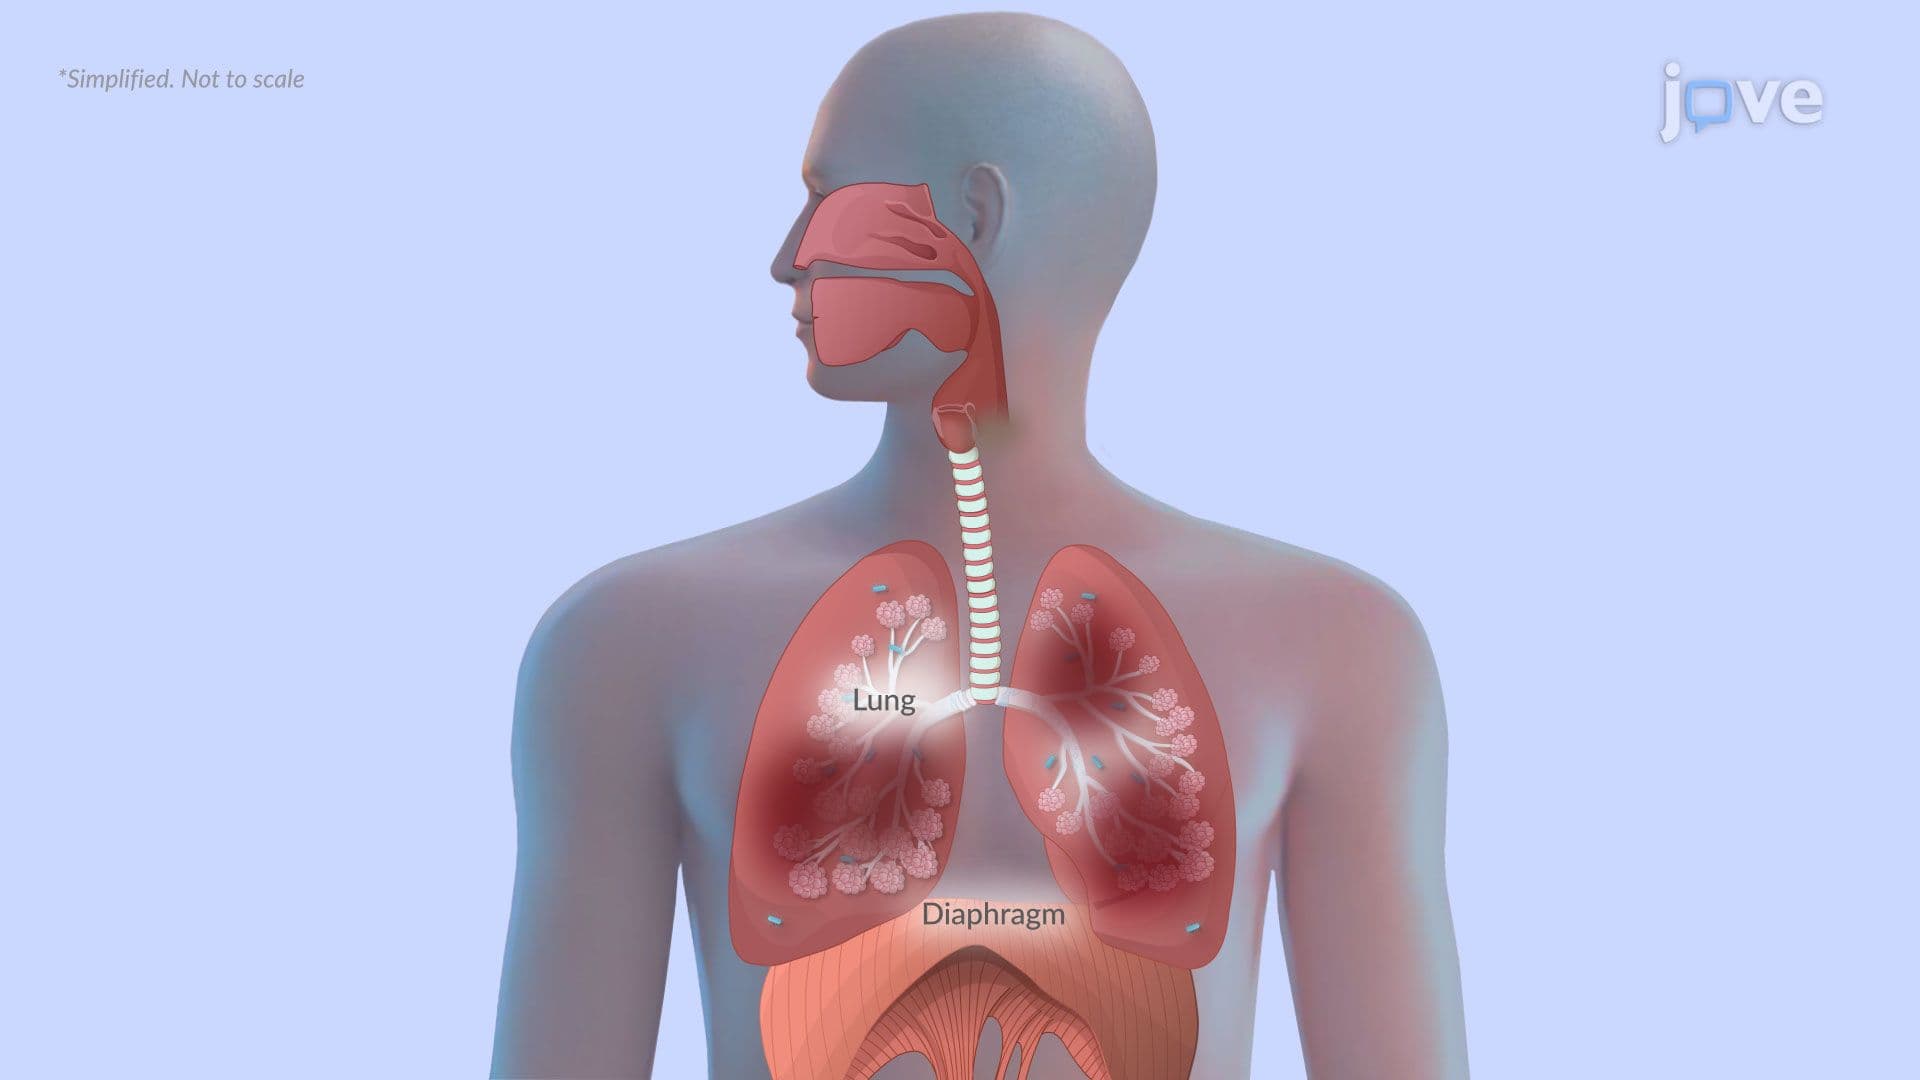 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:28
Asthma I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:29
Asthma-I: Introduction
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...