Related Experiment Video
Updated: Jun 7, 2026

Evaluating the Function of the Foot Core System in the Elderly
Published on: March 11, 2022
Peroneal nerve dysfunction in patients with complex clubfeet
Shinji Yoshioka1, Nickolas J Huisman, Jose A Morcuende
1The Ponseti Clubfoot Treatment Center, University of Iowa, USA.

Insights
Complex clubfeet treatment using a modified Ponseti technique shows success. Careful cast application is crucial to minimize peroneal nerve dysfunction, a rare complication in complex clubfoot cases.
Area of Science:
- Orthopedics
- Pediatric Orthopedics
- Podiatry
Background:
- Complex clubfeet present unique challenges in treatment.
- Traditional Ponseti casting may require modifications for complex cases.
- Potential complications, including nerve dysfunction, are a concern.
Purpose of the Study:
- To evaluate the effectiveness and complications of a modified Ponseti casting technique for complex clubfeet.
- To assess the incidence of peroneal nerve dysfunction in this patient cohort.
- To determine the need for surgical intervention in complex clubfeet treated with modified casting.
Main Methods:
- Retrospective review of a clubfeet patient database (2001-2009).
- Analysis of patients with complex clubfoot deformities treated with modified Ponseti casting.
- Documentation of casting, tenotomies, orthotic use, relapses, and neurological complications.
Main Results:
- 13% of treated clubfeet (182/1376) were classified as complex.
- Peroneal nerve dysfunction occurred in 0.7% of complex cases (10/182 feet).
- Average casts needed were 5; 2 patients had Achilles tenotomy; no surgical releases were required; 37% relapsed but responded to casting.
Conclusions:
- The modified Ponseti technique is effective for complex clubfeet, avoiding extensive surgery.
- Close neurological monitoring and meticulous cast application are essential.
- While peroneal nerve dysfunction is a risk, it is infrequent with careful management.
Abstract:
Complex clubfeet represent a subset of clubfeet with unique features. Their correction requires a modification of the Ponseti casting technique and good short term results have been reported. However, these clubfeet are very difficult to treat and there is a higher chance for potential complications. We reviewed the database of patients with clubfeet treated from January 2001 to December 2009. There were 837 patients (1376 feet) with 111 (182 feet) (13%) having complex deformity. Of these, 8 patients (10 complex clubfeet) (0.7%) experienced a peroneal nerve dysfunction. Severity of the dysfunction varied from no active dorsiflexion (2 patients) to weakness for active dorsiflexion or foot eversion (6 patients). Deformity correction required an average of 5 casts (range, 1 to 8). Two patients required an Achilles tenotomy and the average ankle dorsiflexion at last follow up was 14 degrees (range: 5 to 25). No surgical releases have been required. Two patients required an ankle foot orthosis to improve gait. There were three relapses (37%) that responded to casting and 1 patient required a tibialis anterior tendon transfer. Only 3 feet have recovered the nerve dysfunction. In conclusion, repeated neurological evaluations and very careful cast placement should be performed during the treatment of complex clubfeet. The modified Ponseti technique, if applied properly, is successful in correcting these feet and avoids extensive surgical releases.
Related Concept Videos
 01:28
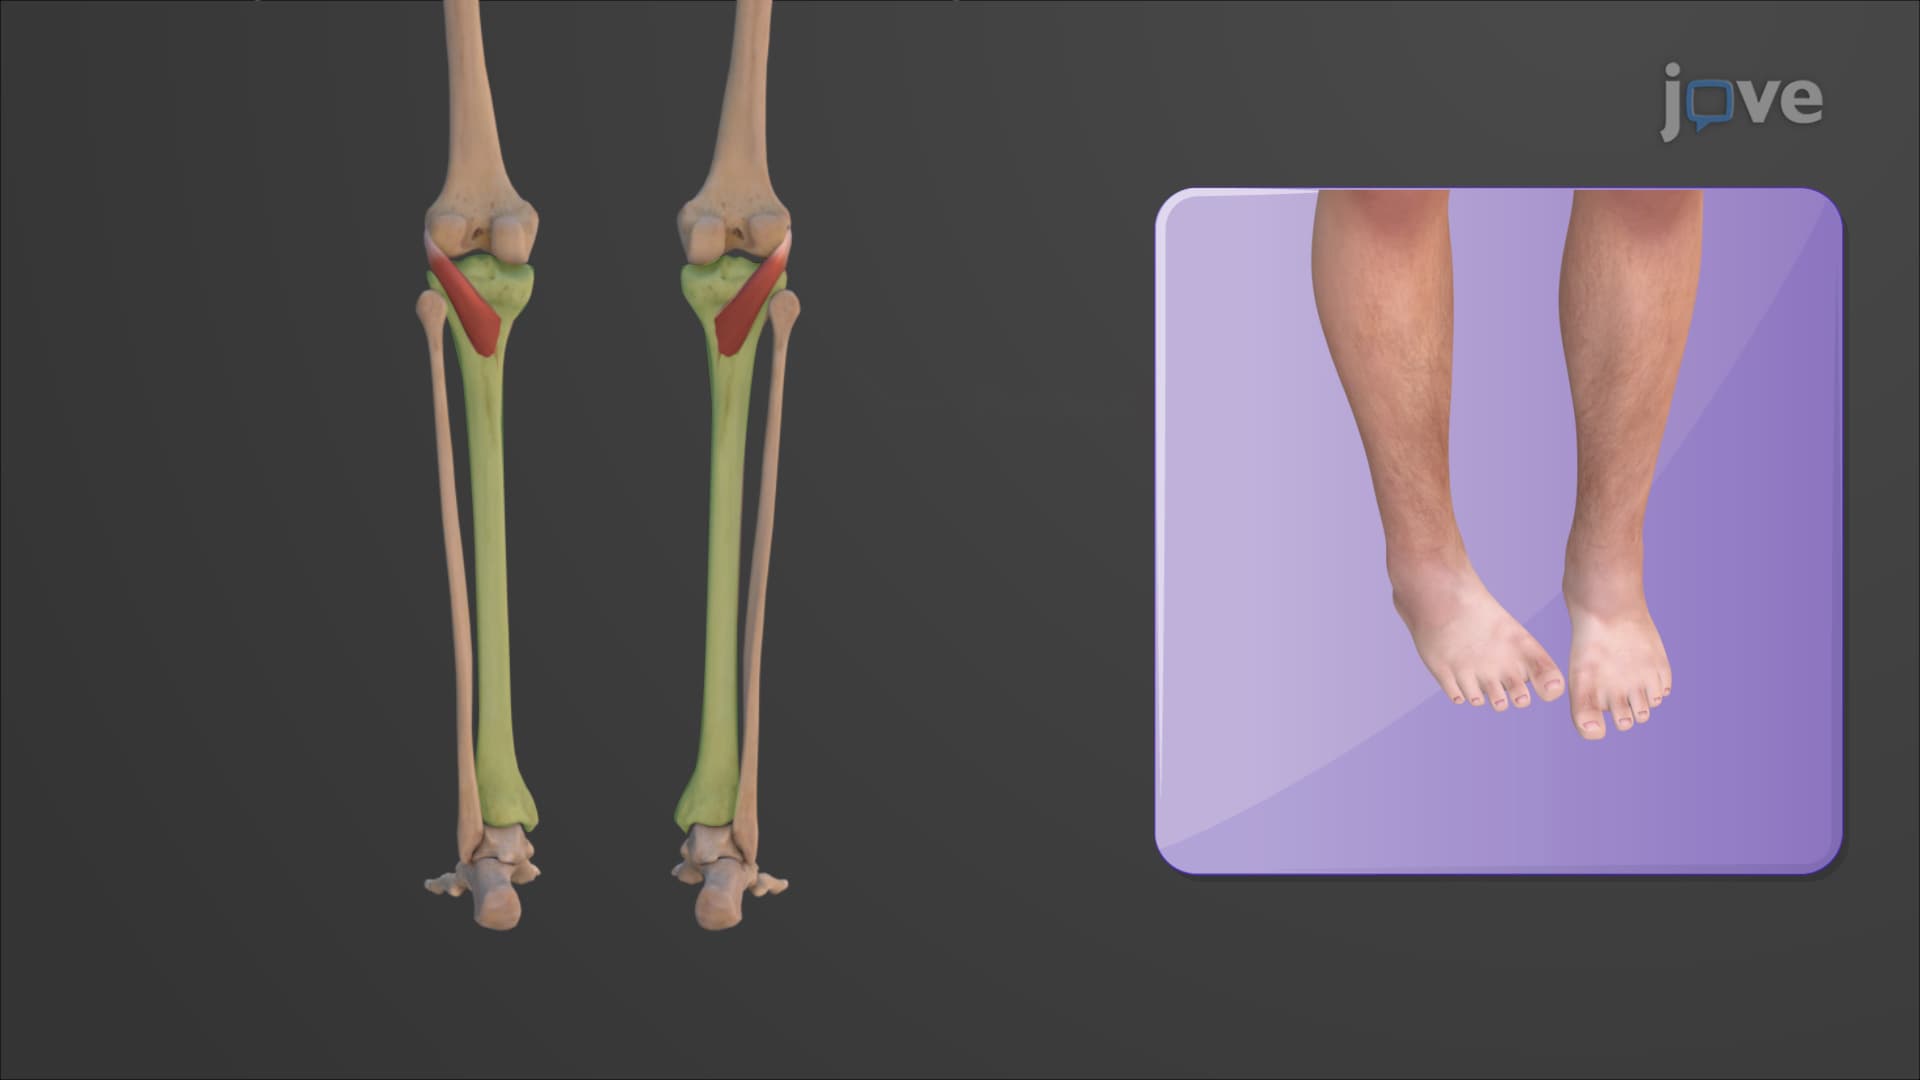
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles.
 01:31
Diabetic Foot Ulcer
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:11
Pulse Assessment Sites
 01:22
Diabetic Neuropathy
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management