Related Experiment Video
Updated: Jun 7, 2026


Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
Complications of clavicle fractures treated with intramedullary fixation
Peter J Millett1, Jason M Hurst, Marilee P Horan
1Steadman Clinic & Steadman Philippon Research Institute, Vail, CO, USA. drmillett@steadmanclinic.net

Hypothesis:
Recent studies have demonstrated better outcomes with operative fixation of displaced midshaft clavicle fractures. We hypothesize that the risk of major complication with intramedullary fixation for clavicle fractures will be low.
Materials And Methods:
Clavicle fractures in 58 patients were treated with intramedullary fixation. Patients were excluded for concomitant pathologies and prior surgery status. Data collected included age, gender, treatment, fracture location, time of pin removal, type of complication, dates of further surgery, and American Shoulder and Elbow Surgeons (ASES) score. Complications were grouped into major (infection, nonunion, malunion) and minor (skin erosion, painful hardware, hardware breakage without consequence) categories. The mean age at surgery was 38 years (range, 18-67 years). All pins were removed at an average of 67 days (95% confidence interval, 54-85).
Results:
Of the 58 patients, 15 (25.8%) complications occurred in 14 patients (24.1%). Five (8.6%) were classified as major (5 nonunions requiring revision surgery). Ten (17.2%) were classified as minor (1 delayed union, 2 superficial wound infections, 2 hardware failures after union, 5 skin erosions with pin exposure but without significant infection). Postoperative ASES scores average 89 at a mean follow-up of 7 years.
Discussion:
Complete union and function were achieved in most patients, with an 8.6% risk of major complication. Intramedullary fixation has the potential for early but temporary hardware prominence, hardware exposure, and a slightly higher incidence of nonunion.
Conclusion:
Patients with intramedullary fixation can expect smaller scars, no long-term hardware complications, and small potential for refracture or further hardware-related complications after hardware removal.
More Related Videos
 11:21
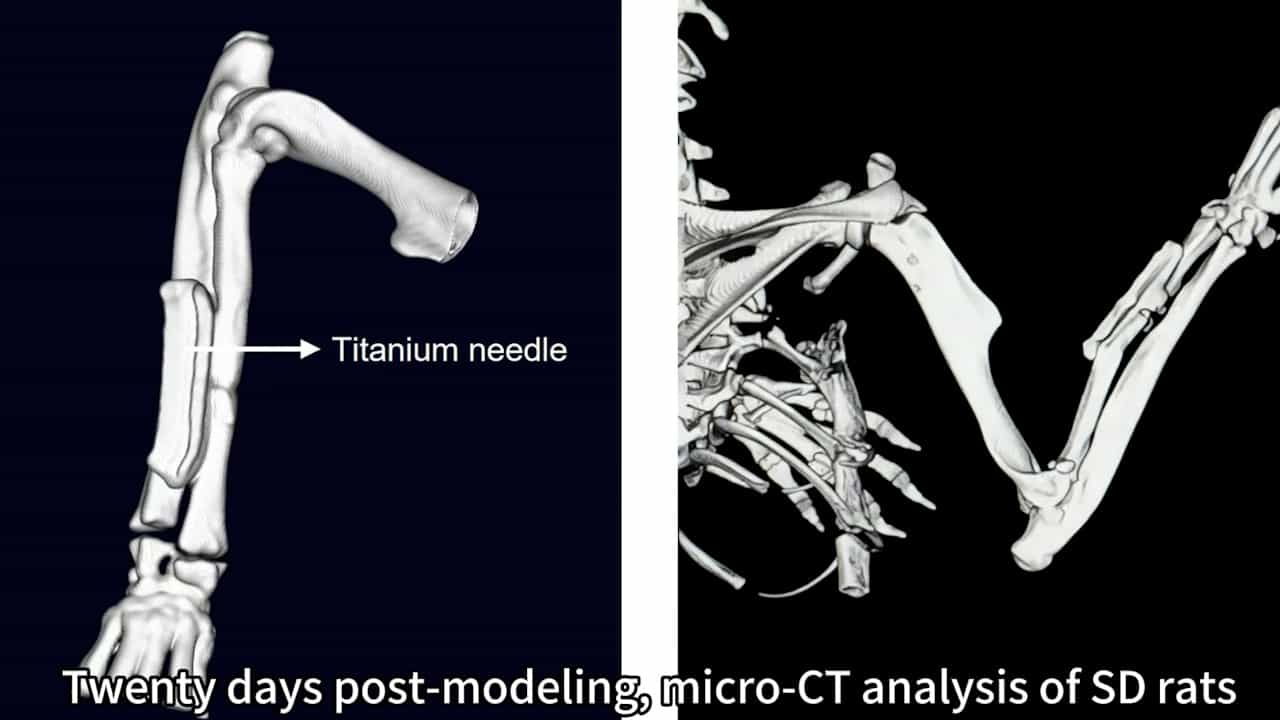
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Healing II: Complications
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...