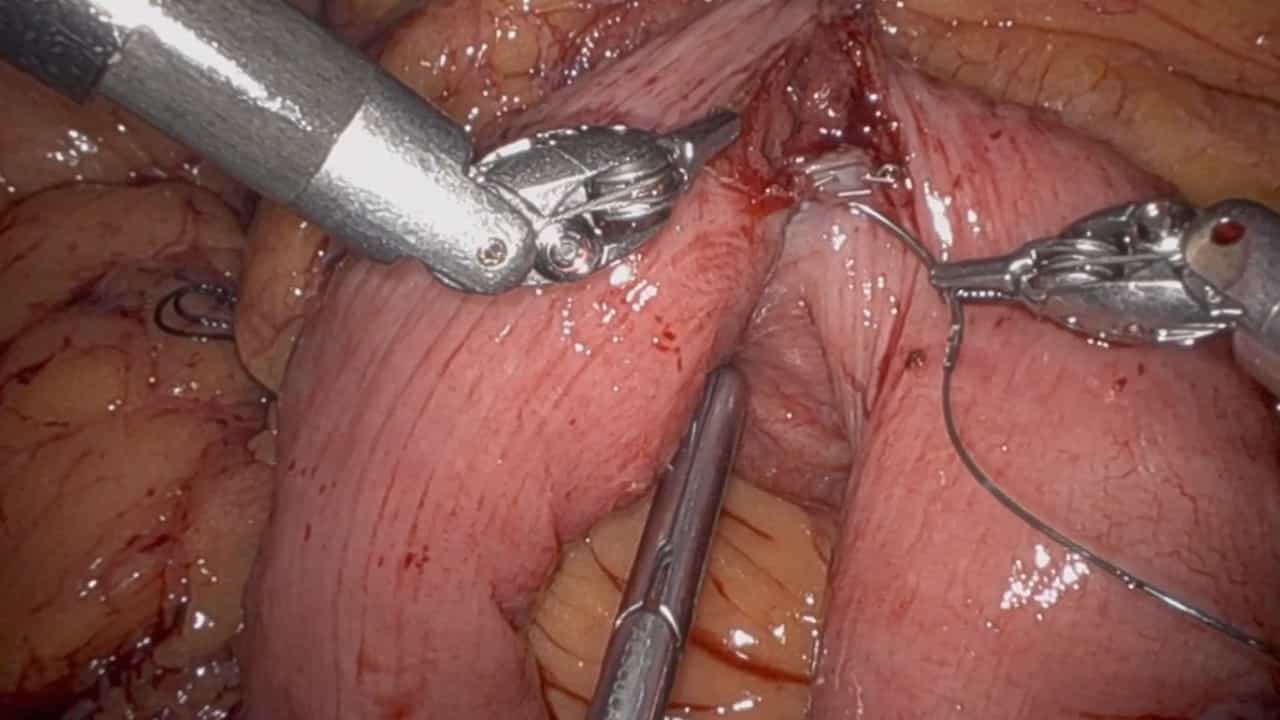
Related Experiment Video
Updated: Jun 6, 2026

Laparoscopic Common Bile Duct Exploration Followed by Primary Suture Using a Modified Bile Duct Incision
Published on: May 2, 2025
How valuable is ductal plate malformation as a predictor of clinical course in postoperative biliary atresia
Rumi Arii1, Hiroyuki Koga, Atsushi Arakawa
1Department of Pediatric General and Urogenital Surgery, Juntendo University School of Medicine, 2-1-1 Hongo, Bunkyo-ku, Tokyo, Japan.

Insights
Ductal plate malformation (DPM) in biliary atresia patients post-hepatoportoenterostomy (HPE) was associated with higher bilirubin levels and increased steroid use. However, DPM did not significantly impact long-term complication rates.
Area of Science:
- Pediatric Surgery
- Hepatology
- Gastroenterology
Background:
- Biliary atresia is a severe neonatal liver disease requiring surgical intervention.
- Hepatoportoenterostomy (HPE) is a surgical procedure to treat biliary atresia.
- Ductal plate malformation (DPM) is a histopathological finding in liver diseases.
Purpose of the Study:
- To evaluate ductal plate malformation (DPM) as a prognostic indicator for mid- to long-term outcomes in patients who underwent hepatoportoenterostomy (HPE) for biliary atresia.
Main Methods:
- Analysis of biopsy specimens from 43 patients who underwent HPE between 1989 and 2009.
- Identification of DPM using Cytokeratin 19 staining.
- Comparison of clinical outcomes including postoperative bilirubin, jaundice-free period, steroid usage, complications, and need for reoperation or transplantation between DPM-positive and DPM-negative groups.
Main Results:
- Ductal plate malformation (DPM) was identified in 48.8% of patients.
- DPM-positive patients exhibited higher maximum postoperative serum total bilirubin levels (12.28 vs. 9.67 mg/dL).
- While overall steroid usage was not significantly different, DPM-positive patients who became jaundice-free required higher steroid doses (75.3 vs. 48.1 mg/kg).
- Mean follow-up duration was significantly shorter in DPM-positive patients (60.9 vs. 113.8 months).
- No significant differences were observed in the incidence of complications such as cholangitis, bile lakes, or varices.
Conclusions:
- Postoperative hyperbilirubinemia was more pronounced in DPM-positive biliary atresia patients, necessitating higher steroid dosages.
- Ductal plate malformation (DPM) did not appear to adversely affect the incidence of mid- to long-term complications after HPE.
- DPM may indicate a need for closer monitoring due to potentially shorter follow-up durations observed in this study.
Purpose:
We assessed ductal plate malformation (DPM) as a prognostic factor for mid-/long-term outcome in post-hepatoportoenterostomy (HPE) biliary atresia patients.
Methods:
Of 78 cases of HPE performed between 1989 and 2009, biopsy specimens were available for 43. Cytokeratin 19 was used to identify DPM and preoperative status, postoperative serum total bilirubin, time taken to become jaundice-free, duration of jaundice-free period, steroid usage, incidences of cholangitis, bile lakes, and varices, and requirement for reoperation and liver transplantation were compared.
Results:
DPM was detected in 21/43 (48.8%) subjects [DPM-positive (DPM+)]. Differences were identified for maximum postoperative serum total bilirubin: DPM+ (12.28 ± 1.00 mg/dL) versus DPM-negative (DPM-) (9.67 ± 0.71 mg/dL) (P < 0.05) and total steroid usage: DPM+ (98.3 ± 11.8 mg/kg) versus DPM- (83.4 ± 15.9 mg/kg) (P = NS). However, total steroid dose in jaundice-free cases was significantly higher in DPM+ [75.3 ± 10.0 mg/kg (n = 14) vs. 48.1 ± 6.4 mg/kg (n = 19); P < 0.05)]. There were no differences for complications. Mean duration of follow-up was significantly shorter for DPM+ (60.9 ± 38.4 vs. 113.8 ± 56.9 months; P < 0.05).
Conclusion:
Postoperative total bilirubin was higher in DPM+ cases, thus higher doses of steroids were required. However, DPM+ did not appear to influence the incidence of complications mid-/long-term.