Related Experiment Video
Updated: Jun 6, 2026

Effects of Allogeneic Platelet-Rich Plasma (PRP) on the Healing Process of Sectioned Achilles Tendons of Rats: A Methodological Description
Published on: March 19, 2018
Effects of platelet-rich plasma on intestinal anastomotic healing in rats: PRP concentration is a key factor
Ryushiro Yamaguchi1, Hideo Terashima, Satoshi Yoneyama
1Department of Surgery, Graduate School of Comprehensive Human Sciences, University of Tsukuba, Tsukuba, Ibaraki, Japan. h-tera@md.tsukuba.ac.jp

Insights
Low-concentrated platelet-rich plasma (PRP) significantly enhanced intestinal anastomotic healing in rats. High-concentrated PRP, however, inhibited healing, indicating PRP concentration is critical for its effects.
Area of Science:
- Regenerative Medicine
- Surgical Innovation
- Gastrointestinal Surgery
Background:
- Limited research exists on platelet-rich plasma (PRP) effects on intestinal anastomotic healing.
- Varied PRP preparation methods and concentrations in prior studies create uncertainty regarding its efficacy.
- This study investigates the impact of different PRP concentrations on intestinal anastomotic healing.
Purpose of the Study:
- To evaluate the influence of varying platelet-rich plasma (PRP) concentrations on the healing of intestinal anastomoses.
- To determine the optimal concentration of PRP for promoting anastomotic wound healing.
- To assess potential inhibitory effects of high PRP concentrations on healing.
Main Methods:
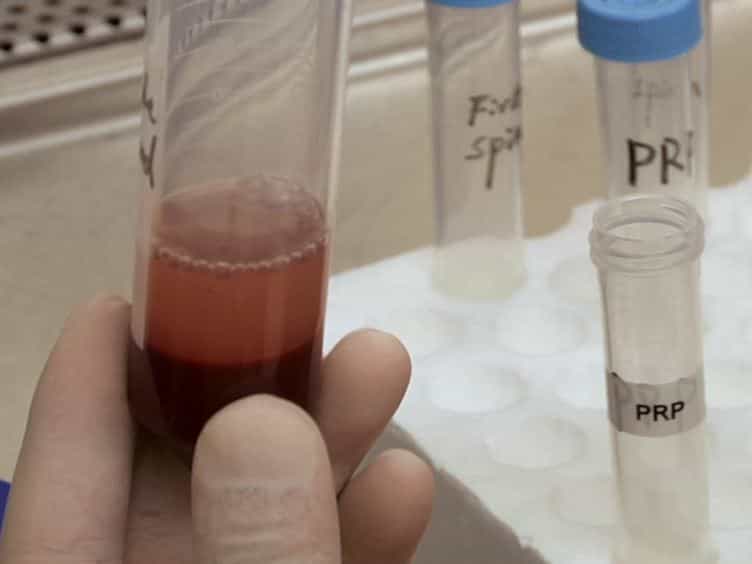
- Preparation of three plasma concentrations: high-concentrated PRP (H-PRP), low-concentrated PRP (L-PRP), and platelet-poor plasma (PPP) from SD rat blood.
- Surgical induction of proximal jejunal anastomosis in male SD rats, divided into control, PPP, L-PRP, and H-PRP groups.
- Application of PRP/PPP to anastomoses, administration of total parenteral nutrition, and evaluation of anastomotic bursting pressure (ABP) and hydroxyproline (HYP) concentration on postoperative day 5.
Main Results:
- Low-concentrated PRP (L-PRP) significantly increased anastomotic bursting pressure (ABP) and hydroxyproline (HYP) concentration compared to controls.
- High-concentrated PRP (H-PRP) significantly decreased both ABP and HYP values, suggesting an inhibitory effect on healing.
- Platelet-poor plasma (PPP) showed no significant difference in healing parameters compared to the control group.
Conclusions:
- Platelet-rich plasma (PRP) concentration is a critical factor determining its effect on intestinal anastomotic healing.
- PRP demonstrates a dose-dependent effect, promoting healing up to a certain concentration, beyond which it can be inhibitory.
- The therapeutic action of PRP in anastomotic healing appears to be primarily mediated by its platelet content.
Background:
Few studies have examined the effects of platelet-rich plasma (PRP) on intestinal anastomotic healing. The applied preparation methods and PRP concentrations used in the few studies that have been carried out varied markedly. Therefore, the positive effects of PRP on the anastomotic healing process remain unclear. The aim of this study is to examine the effects of different concentrations of PRP on intestinal anastomotic healing.
Material And Methods:
From SD rat blood, three different concentrations of plasma were prepared: high-concentrated PRP (H-PRP: platelet count 5 × 10(6)/mm(3)), low-concentrated PRP (L-PRP: 2 × 10(6)/mm(3)), and platelet-poor plasma (PPP). Male SD rats underwent proximal jejunal anastomosis and central venous catheterization. Rats were divided into four groups (n = 12 for each group): control, PPP, L-PRP, and H-PRP groups. Two types of PRP and PPP (0.21 mL) were applied to each anastomosis line, with the exception of the control group. Total parenteral nutrition (TPN) solutions were administered (151 kcal/kg/d). Five days after surgery, anastomotic bursting pressure (ABP) in situ and hydroxyproline concentration (HYP) in anastomotic tissue were evaluated.
Results:
The ABP values of control, PPP, L-PRP, and H-PRP groups were 171 ± 20, 174 ± 23, 189 ± 17, and 148 ± 25 mmHg, respectively. The HYP values of each group were 516 ± 130, 495 ± 123, 629 ± 120, and 407 ± 143 μg/g dry tissue. Compared with the other groups, the L-PRP group exhibited a significant increase in both ABP and HYP, while the H-PRP group exhibited a significant decrease in these two variables. As a result, L-PRP was considered to promote anastomotic wound healing, but H-PRP was considered to inhibit it. There was no significant difference between the PPP group and the control group.
Conclusions:
PRP concentration plays a crucial role in the efficacy of PRP. PRP might exert positive effects on intestinal anastomotic healing in a dose-dependent manner up to a certain level, but adverse effects occur when it is highly concentrated. The essential PRP action appears to be driven by the platelets themselves.