Related Experiment Video
Updated: Jun 6, 2026

Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Clinical outcome of cranial neuropathy in patients with pituitary apoplexy
Hyun-Jin Woo1, Jeong-Hyun Hwang, Sung-Kyoo Hwang
1Department of Neurosurgery, Kyungpook National University School of Medicine, Daegu, Korea.

Objective:
Pituitary apoplexy (PA) is described as a clinical syndrome characterized by sudden headache, vomiting, visual impairment, and meningismus caused by rapid enlargement of a pituitary adenoma. We retrospectively analyzed the clinical presentation and surgical outcome in PA presenting with cranial neuropathy.
Methods:
Twelve cases (3.3%) of PA were retrospectively reviewed among 359 patients diagnosed with pituitary adenoma. The study included 6 males and 6 females. Mean age of patients was 49.0 years, with a range of 16 to 74 years. Follow-up duration ranged from 3 to 20 months, with an average of 12 months. All patients were submitted to surgery, using the transsphenoidal approach (TSA).
Results:
Symptoms included abrupt headache (11/12), decreased visual acuity (12/12), visual field defect (11/12), and cranial nerve palsy of the third (5/12) and sixth (2/12). Mean height of the mass was 29.0 mm (range 15-46). Duration between the ictus and operation ranged from 1 to 15 days (mean 7.0). The symptom duration before operation and the recovery period of cranial neuropathy correlated significantly (p = 0.0286). TSA resulted in improvement of decreased visual acuity in 91.6%, visual field defect in 54.5%, and cranial neuropathy in 100% at 3 months after surgery.
Conclusion:
PA is a rare event, complicating 3.3% in our series. Even in blindness following pituitary apoplexy cases, improvement of cranial neuropathy is possible if adequate management is initiated in time. Surgical decompression must be considered as soon as possible in cases with severe visual impairment or cranial neuropathy.
Related Concept Videos
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:21
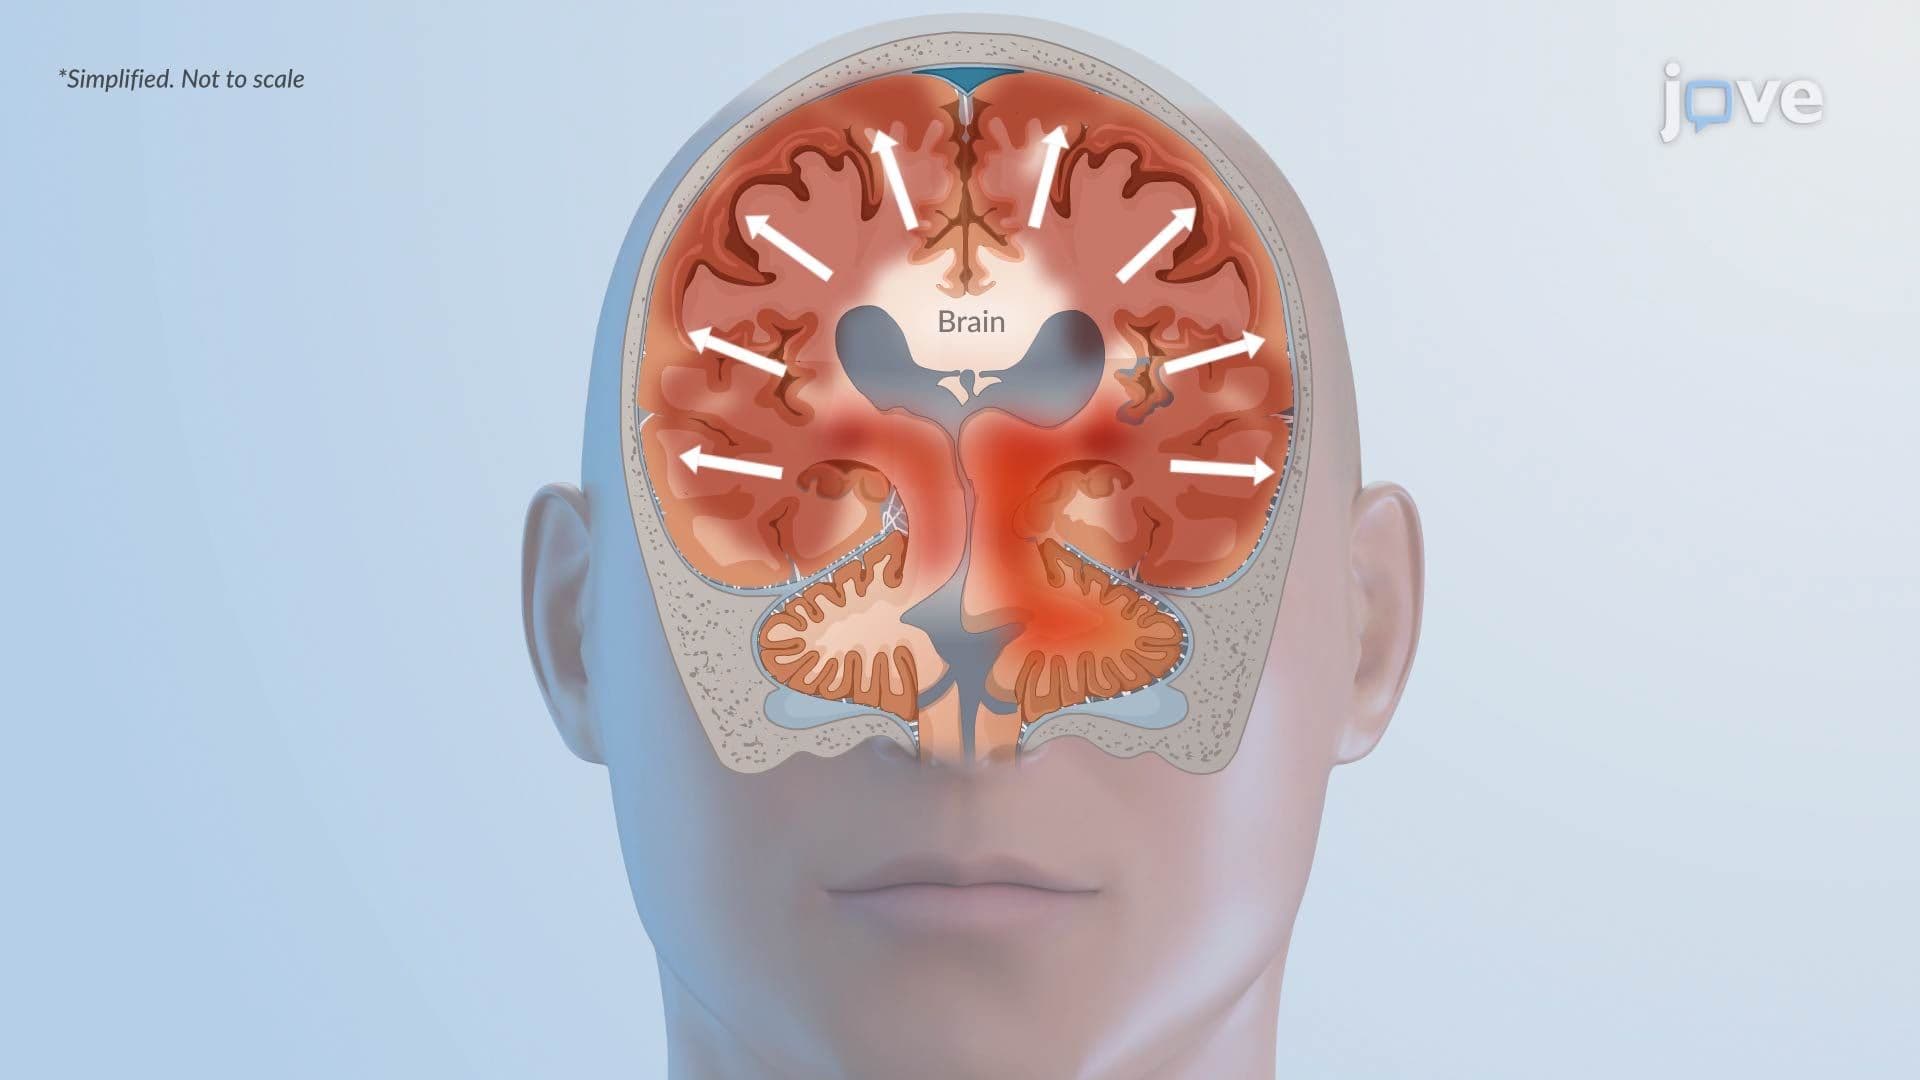
Cytotoxic Edema: Pathophysiology
 01:19
Cushing Syndrome II: Pathophysiology
 01:22
Cerebral Edema ll: Pathophysiology