Related Experiment Video
Updated: Jun 6, 2026


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Rectal intussusception is associated with abnormal levator ani muscle structure and morphometry
N Rodrigo1, K L Shek, H P Dietz
1Sydney Medical School Nepean, Nepean Hospital, Penrith, NSW 2750, Australia.

Background:
Anorectal symptoms are common in urogynaecological patients, and so are anatomical abnormalities of the anorectum associated with such symptoms. One such abnormality is rectal intussusception (RI). The aim of this retrospective study was to determine the prevalence of RI in a tertiary urogynaecological population and to describe the associated symptoms, signs and ultrasound findings, in particular those relating to pelvic floor function and anatomy. It was hypothesized that RI is associated with abnormal levator ani muscle anatomy and function.
Methods:
The electronic records and volume imaging datasets of 967 women who presented to a tertiary urogynaecological clinic between May 2005 and March 2009 were analysed. Rectal intussusception was diagnosed on translabial ultrasound and findings were analysed against symptoms and hiatal area in the levator ani muscle.
Results:
Rectal intussusception was found in 38 women (3.9%) and was more prevalent with increasing age (p = 0.014) and vaginal parity (p = 0.037). It was associated with symptoms of prolapse (p = 0.005), incomplete bowel emptying (p < 0.001), vaginal digitation (p < 0.001), and faecal incontinence (p = 0.022). RI was more common in patients with a clinical diagnosis of enterocele (p = 0.03) and rectocele (p = 0.002). On imaging, RI was associated with an increased hiatal area on valsalva (p < 0.001) and levator ani avulsion (p = 0.003).
Conclusion:
Rectal intussusception is not an uncommon finding in urogynaecological patients. While often asymptomatic, it is associated with symptoms of vaginal prolapse, incomplete bowel emptying, vaginal digitation and faecal incontinence, and with abnormal levator ani structure and morphometry.

Related Concept Videos
 01:29
Intestinal Obstruction I: Introduction
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
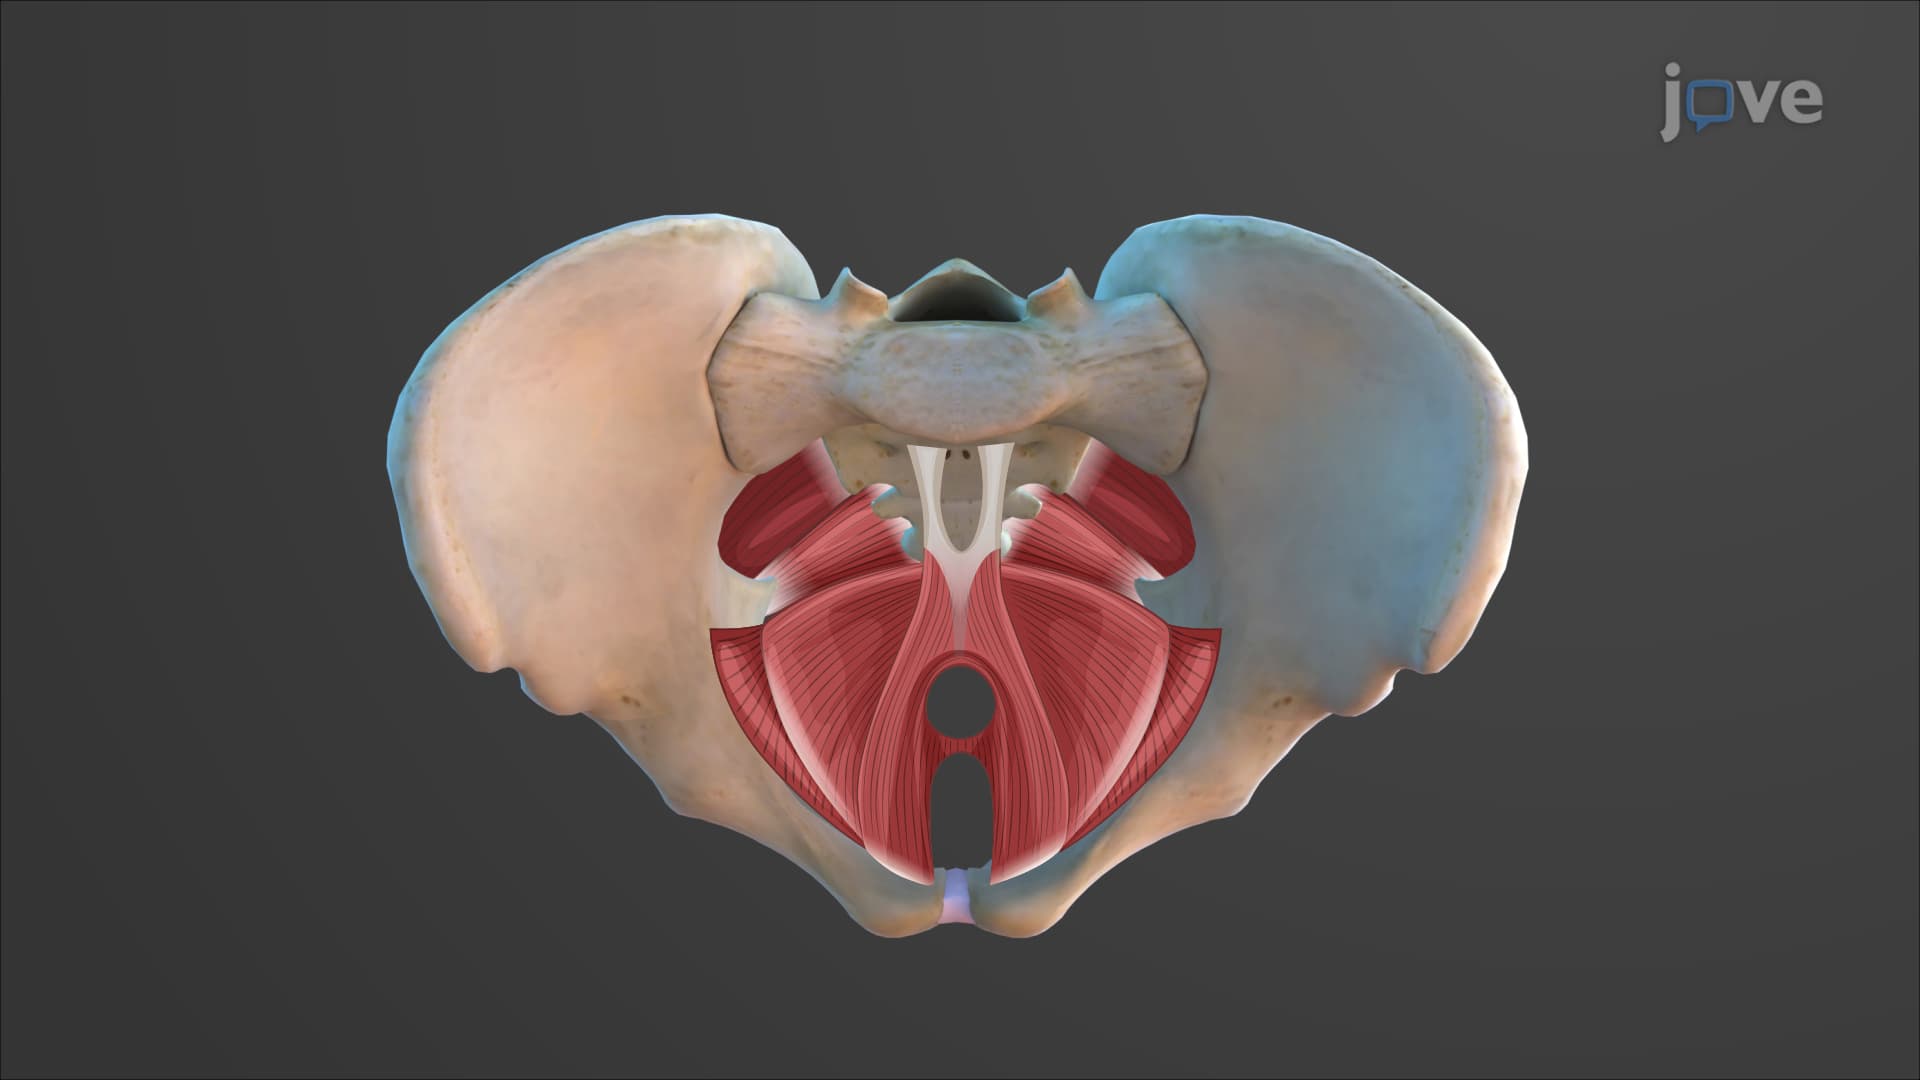
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:27
Diverticular Disease of the Colon
 01:26
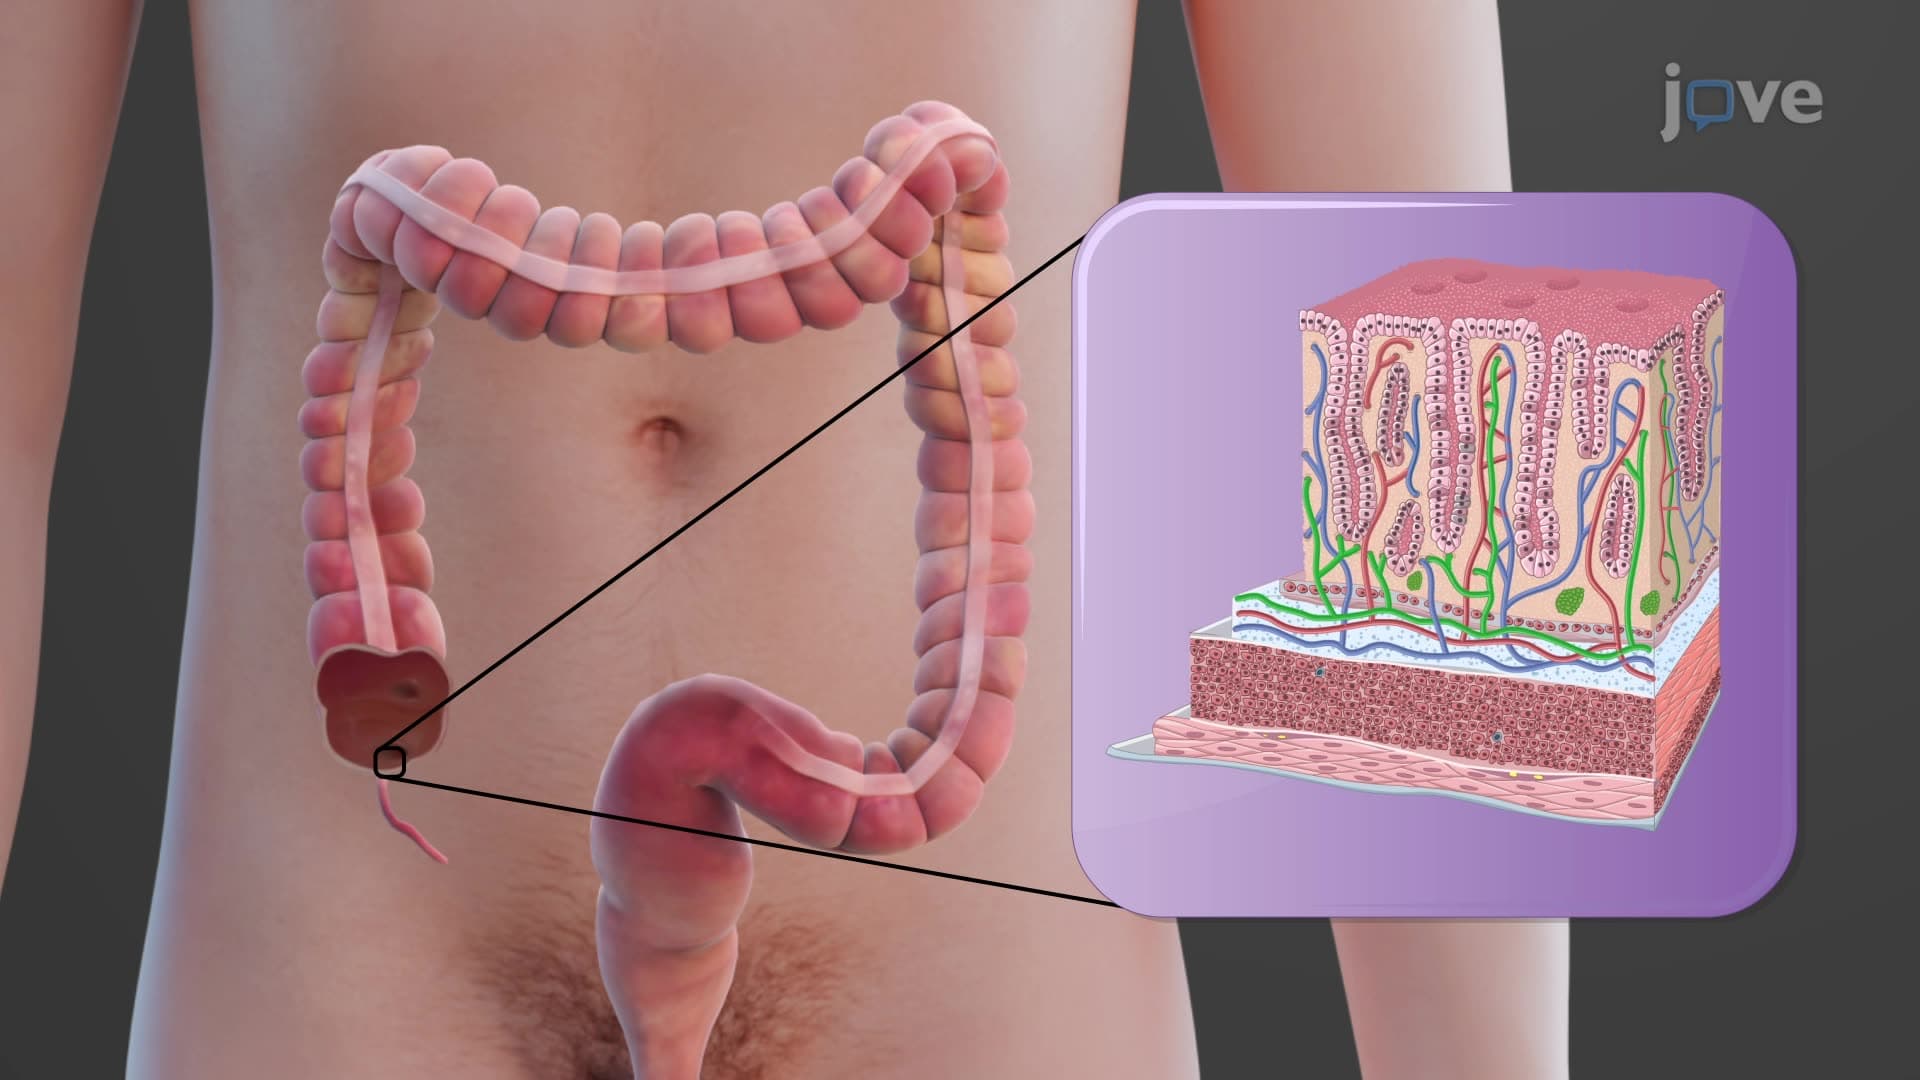
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:09
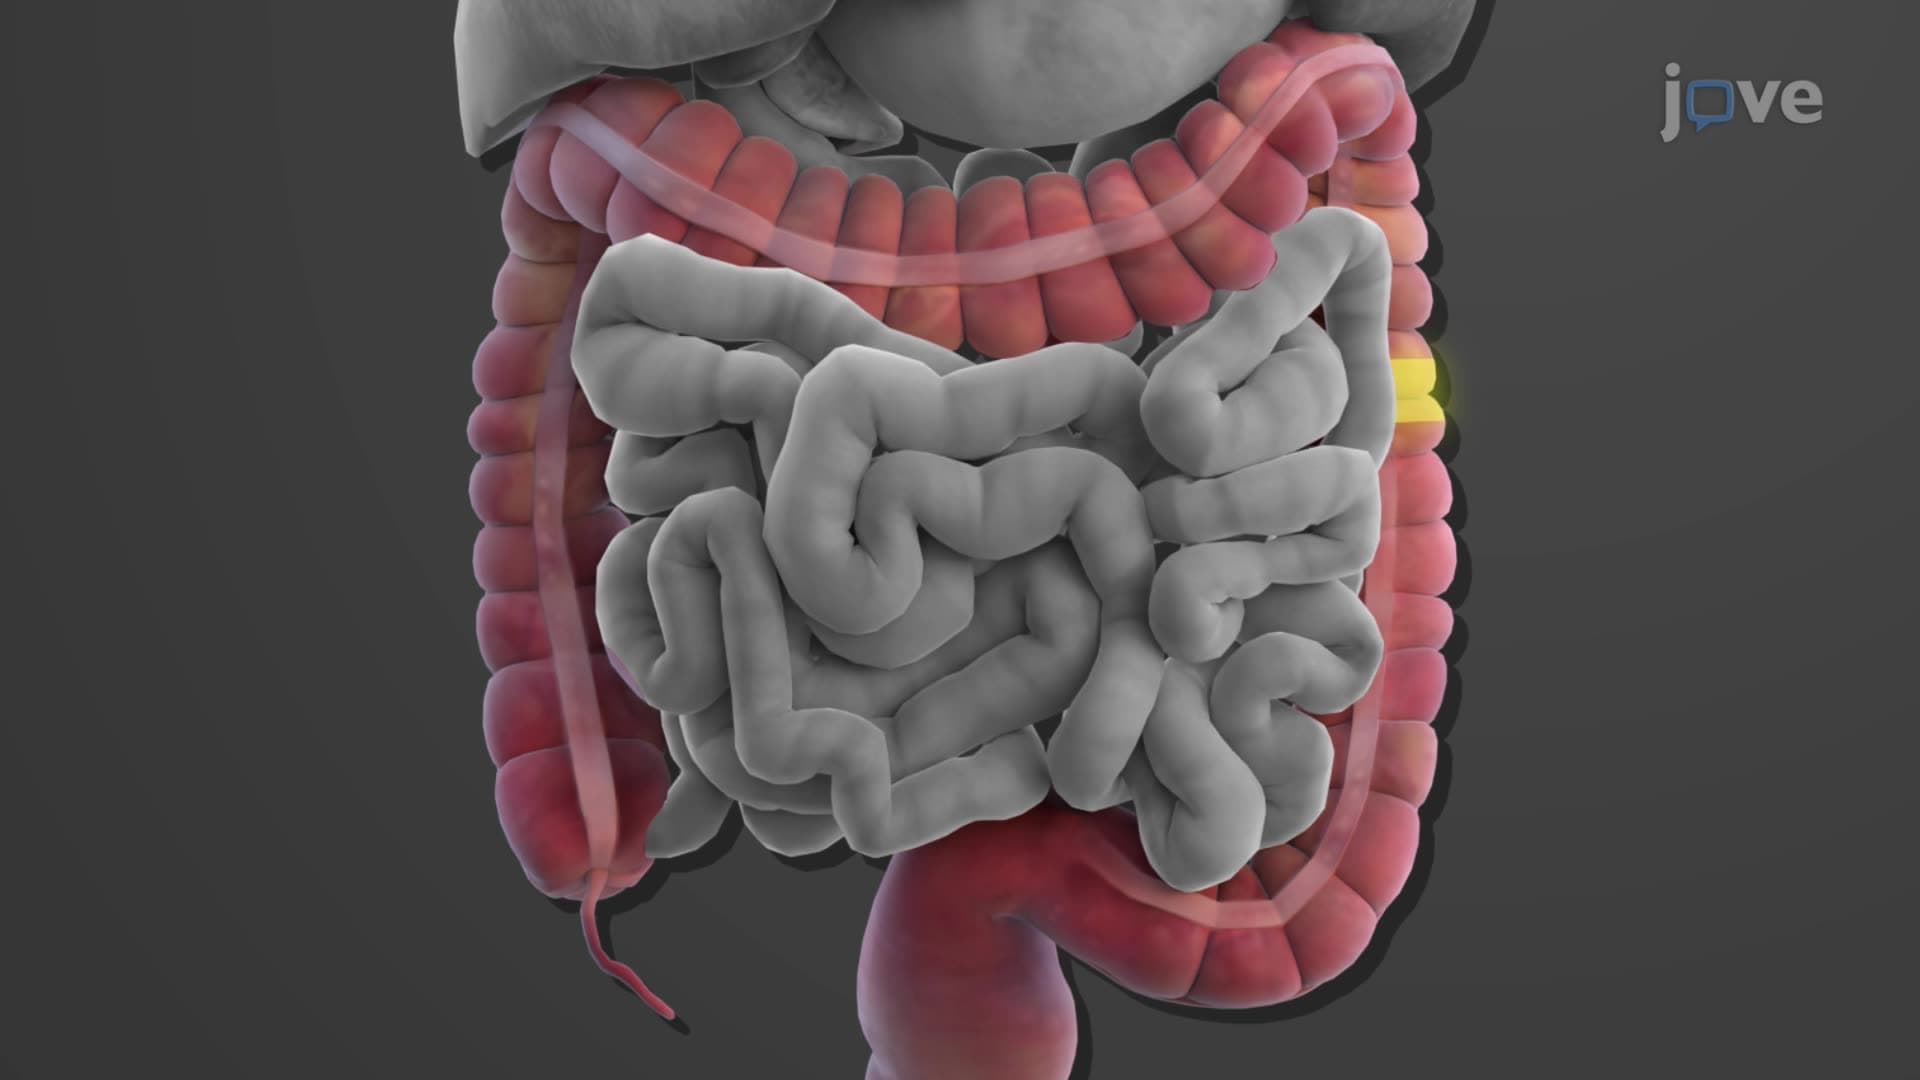
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...