Related Experiment Video
Updated: Jun 6, 2026
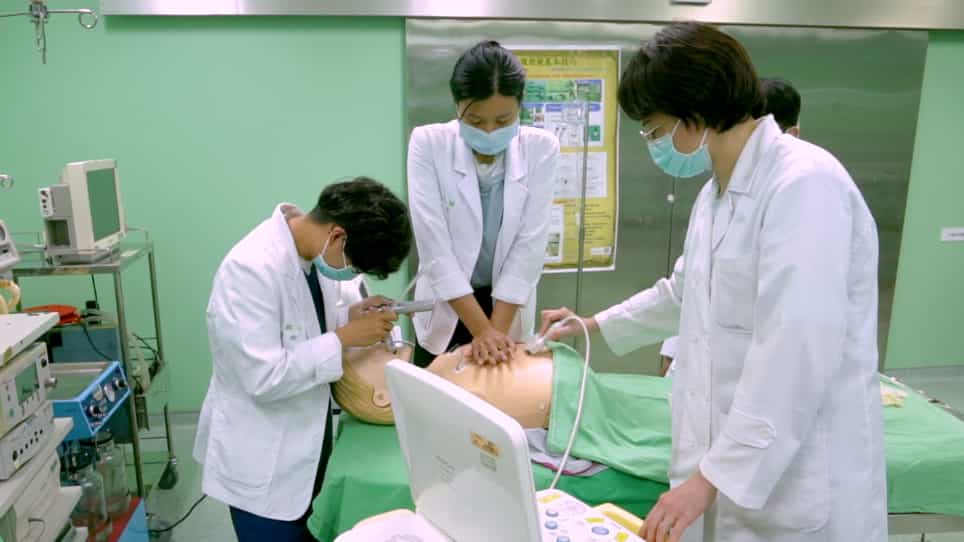

Ultrasonographic Assessment During Cardiopulmonary Resuscitation
Published on: October 24, 2020
[Assistenza cardiocircolatoria. (Cardio-circulatory care)]

Insights
Early recognition and prompt resuscitation are vital for improving outcomes in critically ill children experiencing shock. Tailored management strategies, guided by continuous assessment, are essential for successful treatment.
Area of Science:
- Pediatric Critical Care Medicine
- Neonatology
- Pediatric Cardiology
Background:
- Pediatric cardiovascular failure mortality has significantly decreased due to advances in neonatal and pediatric intensive care.
- Established clinical practice guidelines, such as those from the American College of Critical Care Medicine, report low mortality rates (0%-5%) for pediatric septic shock when best practices are implemented.
- Shock in critically ill children often involves myocardial dysfunction or acute lung injury, necessitating prompt recognition and management.
Purpose of the Study:
- To emphasize the critical role of early shock recognition in successful resuscitation of critically ill children.
- To highlight the importance of managing co-existing myocardial dysfunction and acute lung injury.
- To underscore the need for individualized treatment approaches in pediatric shock management, especially for those with congenital heart disease.
Main Methods:
- Focus on early recognition of shock through continuous assessment of vital parameters.
- Utilization of global indices of tissue oxygen delivery to guide therapy.
- Administration of isotonic fluids as the primary resuscitation measure.
- Simultaneous initiation of targeted history, clinical evaluation, and management of co-morbidities.
Main Results:
- Early recognition and appropriate management of shock, myocardial dysfunction, and acute lung injury are crucial for successful outcomes.
- Repeated assessments are necessary due to unpredictable physiological responses to resuscitation.
- Isotonic fluids are the cornerstone of treatment, with quantities determined by etiology and response.
- Protocol-based management requires individualization based on suspected etiology and therapeutic response.
Conclusions:
- Successful resuscitation in pediatric shock hinges on early recognition, restoration of tissue perfusion, and normalization of cardiac and respiratory function.
- Addressing the underlying cause of shock and managing co-morbidities are urgent priorities.
- Individualized treatment, particularly for children with congenital heart disease, is paramount despite protocol-based approaches.
Abstract:
Mortality in pediatric cardiovascular failure is markedly improved with the advent of neonatal and pediatric intensive care and with the implementation of treatment guidelines. In 2002 the American College of Critical Care Medicine Clinical Practice Parameters for Hemodynamic Support of Pediatric and Neonatal Shock reported mortality rates of 0%-5% in previously healthy and 10% in chronically ill children with septic shock associated with implementation of "best clinical practices". Early recognition of shock is the key to successful resuscitation in critically ill children. Often, shock results in or co-exists with myo-cardial dysfunction or acute lung injury. Recognition and appropriate management of these insults is crucial for successful outcomes. Resuscitation should be directed to restoration of tissue perfusion and normalization of cardiac and respiratory function. The underlying cause of shock should also be addressed urgently. The physiological response of individual children to shock resuscitation varies and is often unpredictable. Therefore, repeated assessments of vital parameters are needed for taking appropriate decisions. Global indices of tissue oxygen delivery help in targeting therapies more accurately. Isotonic fluids form the cornerstone of treatment and the amount required for resuscitation is based on etiologies and therapeutic response. After resuscitation has been initiated, targeted history and clinical evaluation must be performed to ascertain the cause of shock and management of co-morbidities should be implemented simultaneously. While the management of shock can be protocol based, the treatment needs to be individualized depending on the suspected etiology and therapeutic response particularly for children who suffer from congenital heart disease.
More Related Videos


Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:27
Peripheral Artery Disease III: Interprofessional Care