Related Experiment Video
Updated: Jun 6, 2026

Antibiotic Efficacy Testing in an Ex vivo Model of Pseudomonas aeruginosa and Staphylococcus aureus Biofilms in the Cystic Fibrosis Lung
Published on: January 22, 2021
Pharmacokinetics of colistin in an adolescent boy with extensive burn injury
Daniel P Healy1, Amy D Sombun, Jason C Gardner
1Shriners Hospitals for Children, Cincinnati, Ohio, USA.

Abstract:
Multidrug resistance in Gram-negative bacteria has led to a resurgence in colistin use. No pharmacokinetic data exist for burn patients. A 17-year-old boy suffered a 71% TBSA full-thickness burn with deep necrosis and compartment syndrome. He developed multidrug-resistant Acinetobacter baumannii burn wound sepsis/septic shock with acute renal failure requiring dialysis. The organism was resistant to all tested antibiotics except colistin. He received colistin 2.5 mg/kg every 24 hours. Peak and trough serum concentrations, area under the concentration-time curve, and elimination half-lives of colistin were 3.6 ± 1.0 μg/ml, 0.9 ± 0.5 μg/ml, 47.1 ± 14.4 mg · hr/L, and 12.3 ± 9.4 hours (mean ± SD), respectively. Serum levels were at or above the minimum inhibitory concentration for >90% of therapy. Nevertheless, salvage therapy with colistin proved futile as the patient developed acidosis, coagulopathy, and was vasopressor-dependent without any wound healing. He died on hospital day 52. Microbiologically, the serum levels of colistin were seemingly adequate, as repeat cultures were negative. Given the peak and trough levels of colistin relative to the minimum inhibitory concentration for the organism (0.5 μg/ml), it would seem that the dosage of 2.5 mg/kg administered every 24 hours for this patient on dialysis was appropriate. Patients on dialysis infected with an organism possessing a higher inhibitory concentration (≥1 μg/ml) should probably receive the same dosage every 12 hours to avoid subtherapeutic concentrations. Large-scale study of the pharmacokinetics of colistin in patients with burn injury is urgently needed.
More Related Videos


Related Concept Videos
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:15
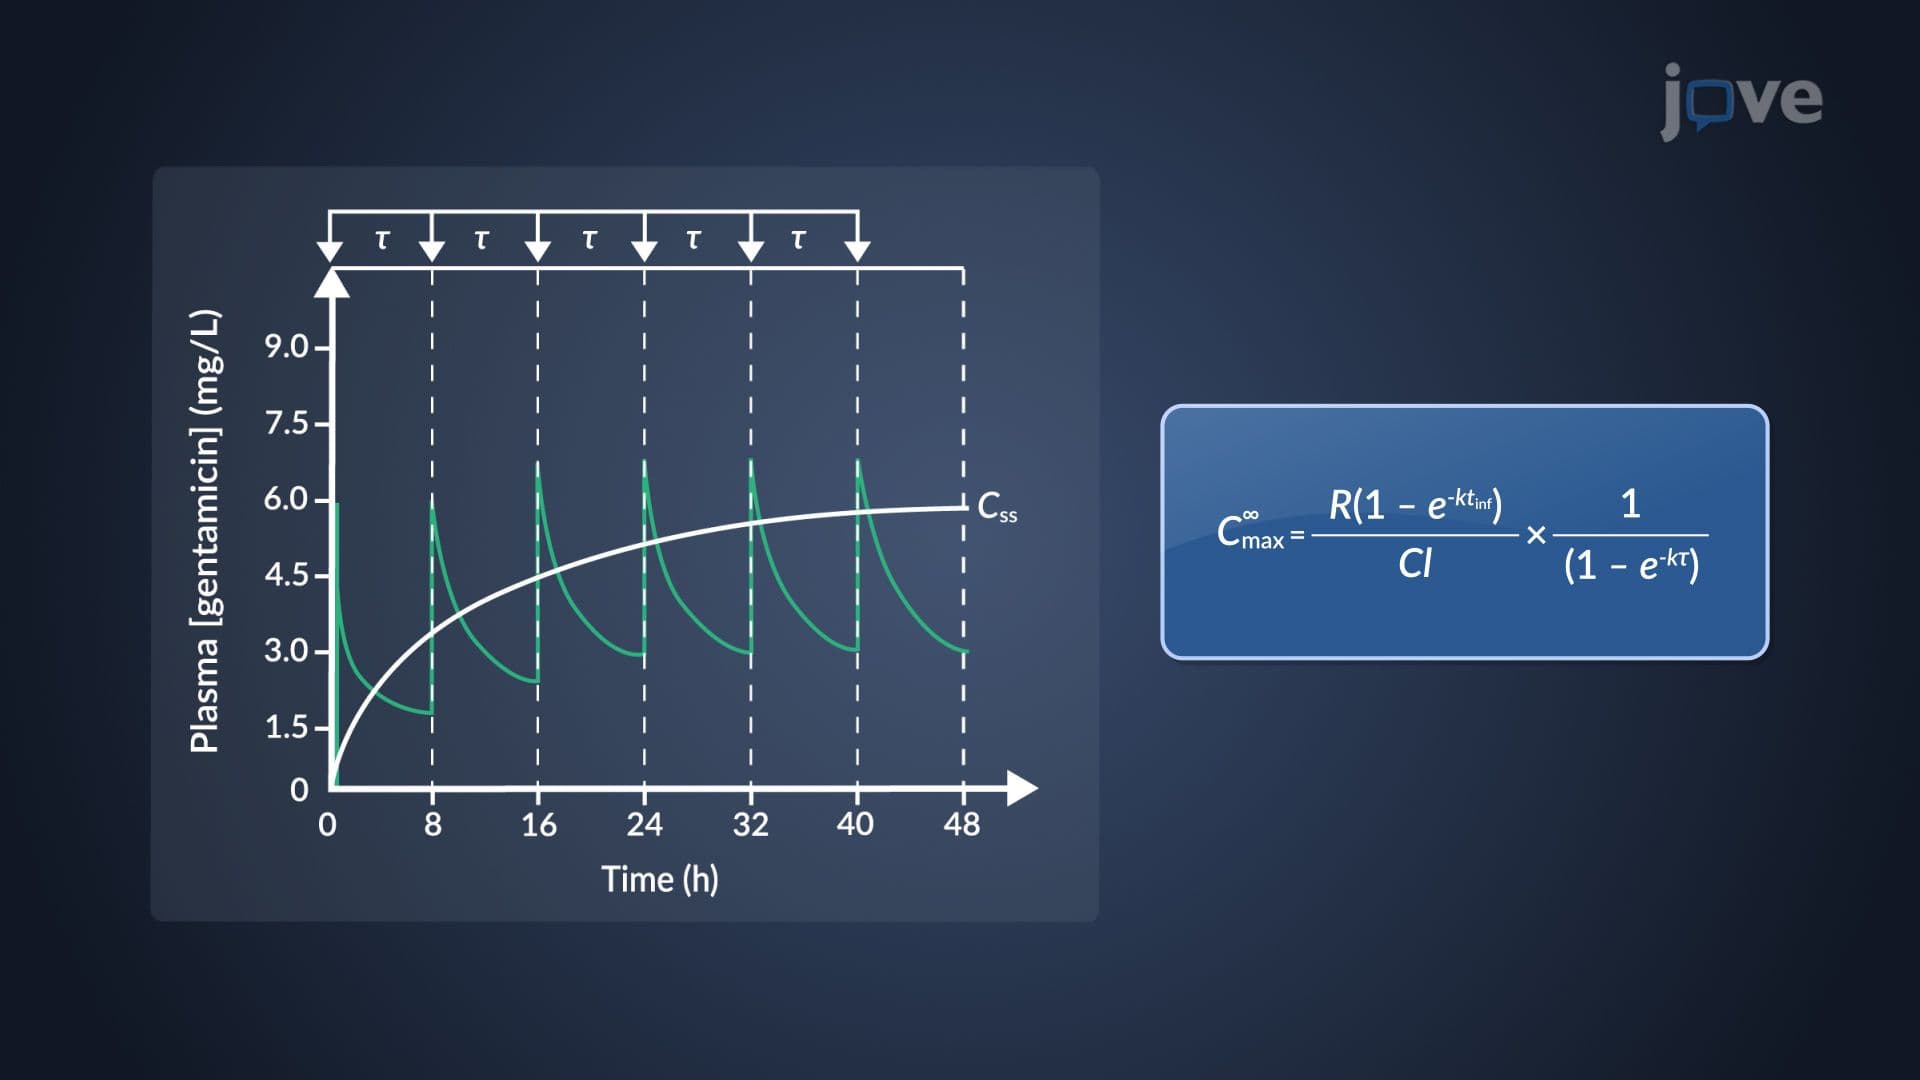
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...