Related Experiment Video
Updated: Jun 6, 2026
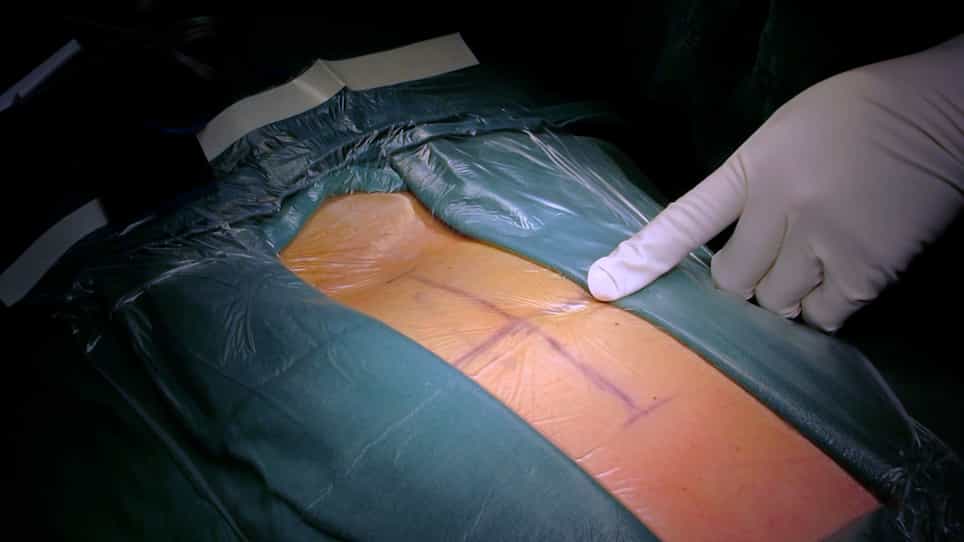

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Management of severe spinal deformity: scoliosis and kyphosis
1Texas Scottish Rite Hospital for Children, Dallas, TX, USA. dan.sucato@tsrh.org

Study Design:
Review of the literature and author';s experience with the treatment of severe spinal deformity.
Objective:
To define the anatomic and physiologic challenges in treating severe spinal deformity and to describe the preoperative, intraoperative, and postoperative strategies to achieve the optimal safe result.
Summary Of Background Data:
Severe pediatric spinal deformity is a relatively uncommon condition that often arises following treatment of early onset scoliosis. Patients most often present with severe clinical and radiographic deformity with poor pulmonary function. In contrast to the more common adolescent idiopathic scoliosis which is a primary spinal deformity, patients with severe spine deformity have the added chest wall deformity which may need to be addressed at the time of treatment. Previous literature has identified the challenges in the treatment of these patients and the higher risk for complications.
Methods:
A literature review and review of the author's personal experience in the treatment of these patients was performed. An assessment of the preoperative, intraoperative, and postoperative factors leading to an optimal result was analyzed and reported.
Results:
The early evaluation should include a multidisciplinary approach from the orthopaedic surgeon, pulmonologist, anesthesiologist, and perhaps the neurologist to provide a baseline assessment. Advanced imaging of the spine with computed tomography is useful especially when previous surgery has been performed and/or when plain radiography is limited. Magnetic resonance imaging of the spinal cord and brain stem is important to ensure that no neural axis abnormalities are present and can determine if spinal cord compression is present. Severe spinal deformity should be distinguished from the more common adolescent idiopathic scoliosis deformity in that both the spine and the chest wall are affected. Preoperative halo-gravity traction is an invaluable tool to improve the flexibility of the spine and chest, to improve pulmonary function, and to stress the spinal cord while the patient is awake and provides feedback as to the neurologic assessment. Surgical treatment should be divided into 3 phases. First, anchor placement which should be predominantly pedicle screws placed in a segmental fashion and also use of reduction screws when performing vertebral column resections. Second, steps should be performed to increase the flexibility of the spine and chest with incremental releases from simple posterior soft tissue releases to posterior facet resections, to vertebral column resections for the most severe deformity. The third phase is the correction of the spine and chest wall deformity. Many strategies can be used to correct these deformities and relies on good anchor point fixation and good releases of the spine and chest wall. Provisional rod fixation is critical when performing resection of the spine to allow for safe correction of the deformity. Improvements in the clinical and radiographic appearance, pulmonary function, and self image are often dramatic.
Conclusion:
The treatment of severe spinal deformity is challenging and requires careful assessment of the patient by the orthopaedic surgeon, anesthesiologist, pulmonologist, and neurologist especially when neurologic deficits are present. Proper planning and execution of the correct surgical procedure for the surgeon provides an outstanding life-changing result in these patients.
More Related Videos
 07:12
Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...