Related Experiment Video
Updated: Jun 6, 2026

Generation of Hypoparathyroid Rats via Carbon-Nanoparticle-Assisted Parathyroidectomy
Published on: July 14, 2023
Time-dependent changes in skeletal response to teriparatide: escalating vs. constant dose teriparatide (PTH 1-34) in
Elaine W Yu1, Robert M Neer, Hang Lee
1Massachusetts General Hospital Department of Medicine, Endocrine Unit, Boston, MA 02114, USA. ewyu@partners.org

Abstract:
Once-daily injections of teriparatide initially increase biochemical markers of bone formation and resorption, but markers peak after 6-12 months and then decline despite continued treatment. We sought to determine whether increasing teriparatide doses in a stepwise fashion could prolong skeletal responsiveness. We randomized 52 postmenopausal women with low spine and/or hip bone mineral density (BMD) to either a constant or an escalating subcutaneous teriparatide dose (30 microg daily for 18months or 20 microg daily for 6 months, then 30 microg daily for 6 months, and then 40 microg daily for 6 months). Serum procollagen I N-terminal propeptide, osteocalcin, and C-terminal telopeptide of type I collagen were assessed frequently. BMD of the spine, hip, radius, and total body was measured every 6 months. Acute changes in urinary cyclic AMP in response to teriparatide were examined in a subset of women in the constant dose group. All bone markers differed significantly between the two treatment groups. During the final six months, bone markers declined in the constant dose group but remained stable or increased in the escalating dose group (all markers, p<0.017). Nonetheless, mean area under the curve did not differ between treatments for any bone marker, and BMD increases were equivalent in both treatment groups. Acute renal response to teriparatide, as assessed by urinary cyclic AMP, did not change over 18 months of teriparatide administration. In conclusion, stepwise increases in teriparatide prevented the decline in bone turnover markers that is observed with chronic administration without altering BMD increases. The time-dependent waning of the response to teriparatide appears to be bone-specific.
Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:40
Bone Remodeling
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
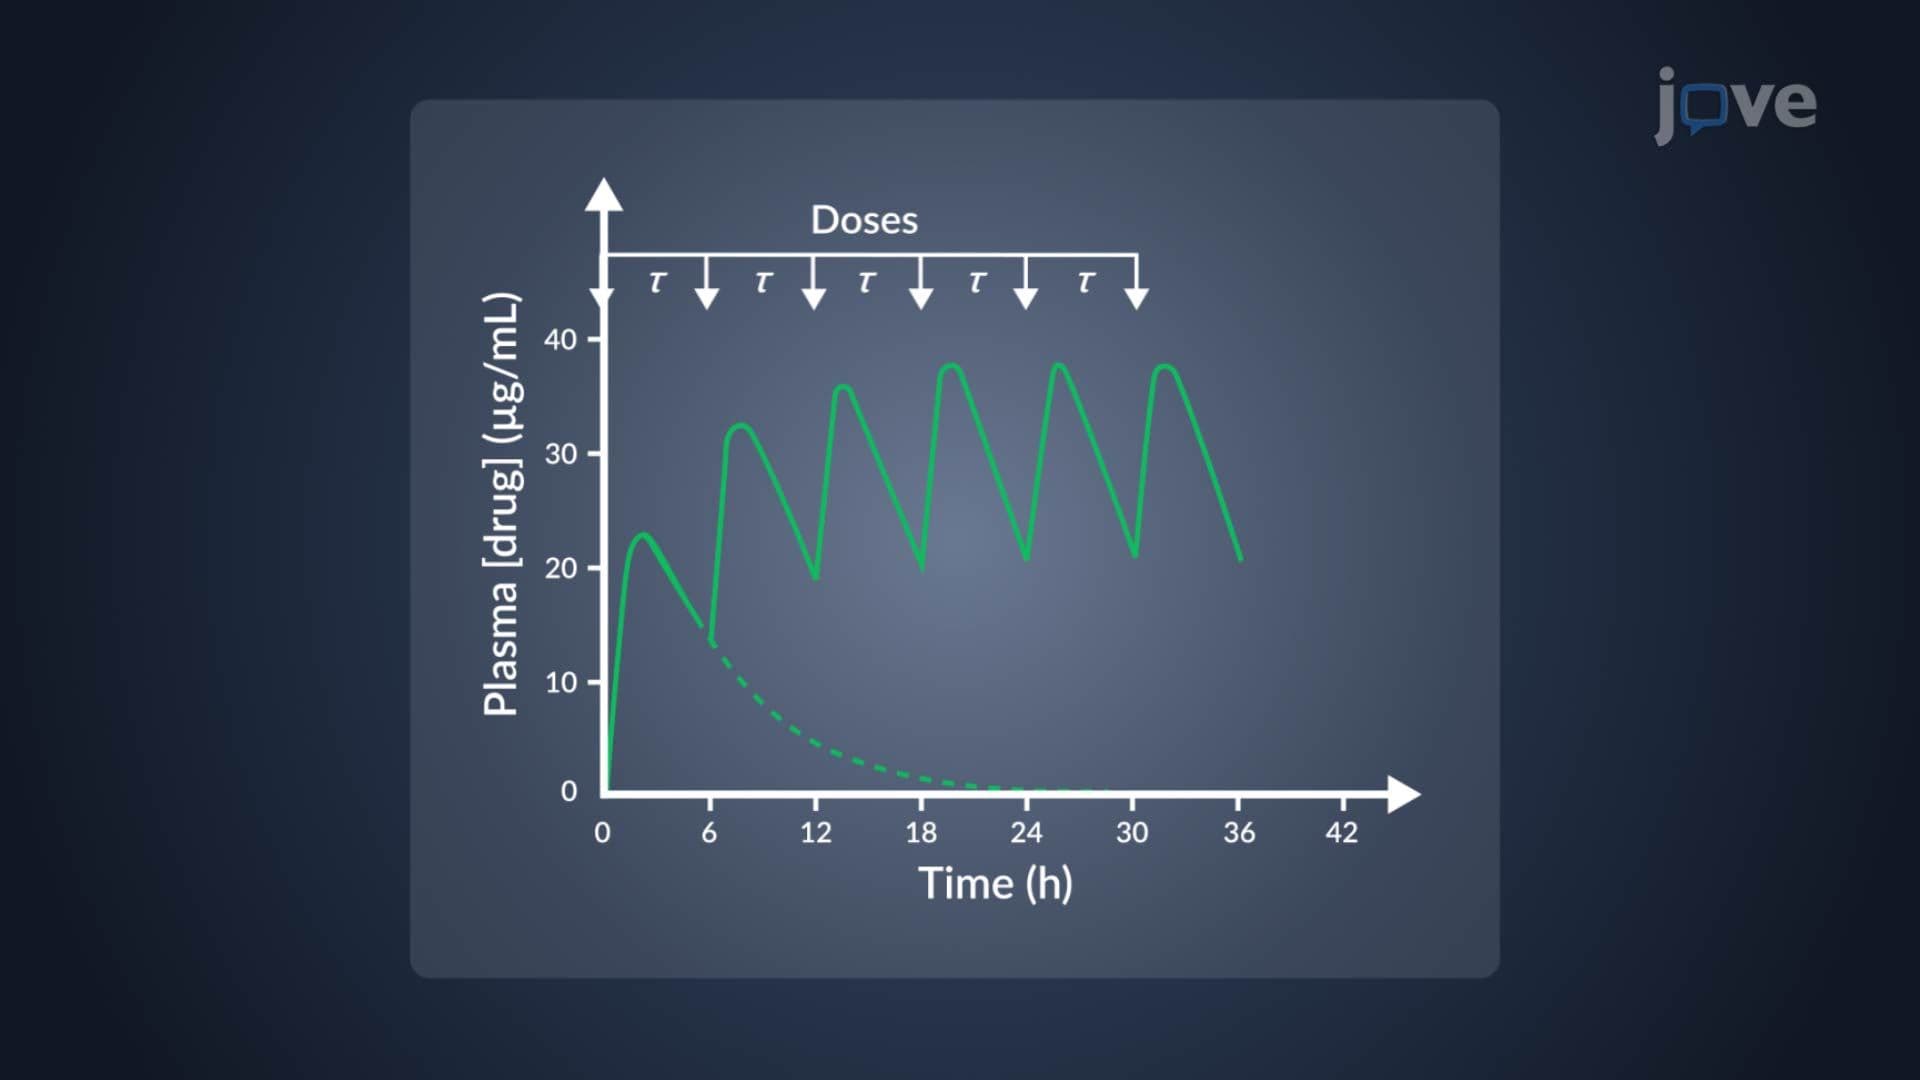
Dosage Regimen: Multiple Oral Dosage
 01:01
Dosage Regimen: Fixed Dose
Fixed-dose regimens can be used for various routes of administration, including intravenous (IV) injections and oral medications. For IV administration, a predetermined amount of the drug is...
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Duration of Dose-Effect Relationship