

Posterior cranial vault distraction osteogenesis in craniosynostosis: estimated increases in intracranial volume
Willy S Serlo1, Leena P Ylikontiola, Niina Lähdesluoma
1Pediatric Surgery, University of Oulu, Oulu, Finland.

Insights
Cranial distraction osteogenesis effectively expands the posterior cranial vault in children with craniosynostosis, achieving significant intracranial volume increases with minimal complications.
Area of Science:
- Craniofacial Surgery
- Pediatric Neurosurgery
- Orthognathic Surgery
Background:
- Craniosynostosis necessitates increased intracranial volume in pediatric patients.
- Posterior cranial vault expansion is crucial for managing elevated intracranial pressure.
Purpose of the Study:
- To evaluate the efficacy of distraction osteogenesis for posterior cranial vault expansion in children.
- To assess the safety and outcomes of this technique in a pediatric cohort.
Main Methods:
- Ten pediatric patients underwent posterior cranial vault distraction osteogenesis using cranial distractors.
- Expansion ranged from 20-30 mm, with a daily distraction rate of 1 mm over 2-4 weeks.
- Patients had various conditions including scaphocephaly, Saether-Chotzen syndrome, Muenke syndrome, and Apert syndrome.
Main Results:
- All patients tolerated the procedure well, with parents managing home distraction.
- A mean increase in intracranial volume of 20.2% was achieved.
- Minor cutaneous issues occurred in two patients but were managed effectively with no long-term adverse effects on the cosmetic outcome.
Conclusions:
- Cranial bone distraction is a safe and effective method for cranial expansion in children with craniosynostosis.
- The technique demonstrates low morbidity and achieves satisfactory cosmetic and volumetric results.
- This preliminary study supports distraction osteogenesis as a valuable treatment option.
Purpose:
To study distraction osteogenesis of the posterior cranial vault in children requiring increased intracranial volume.
Materials And Methods:
Ten patients were treated with cranial distractors. Five children had previously been operated for scaphocephaly and one child for Saether-Chotzen syndrome. Two patients had bilateral coronal suture synostosis with Muenke syndrome and two patients had Apert syndrome. At surgery, the cranial bones were mobilized, the head was widened during surgery, and the segments fixed to each other with distractors. Further expansion at a rate of 1 mm/day was performed over 2-4 weeks. The cranium was distracted posteriorly from 20 to 30 mm.
Results:
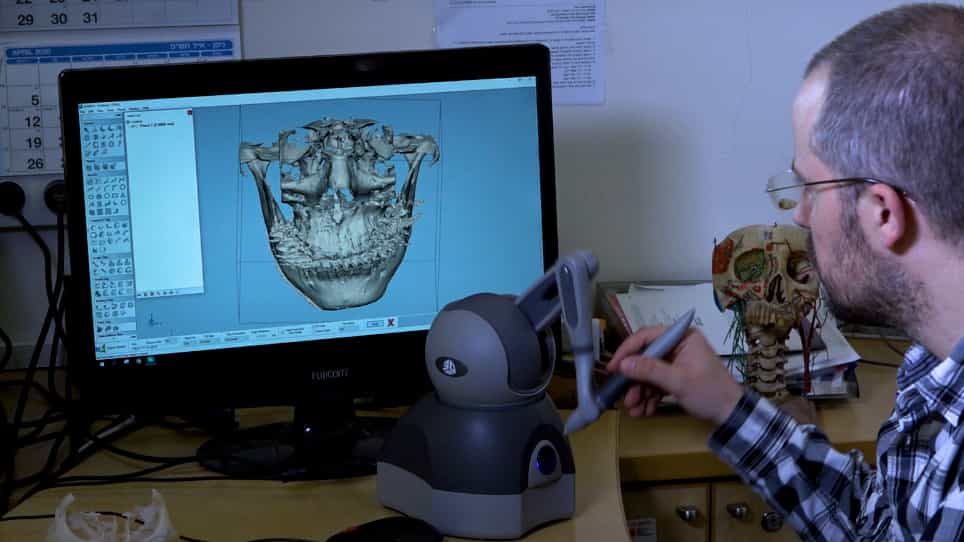
The patients all tolerated surgery and distraction well. In all cases, the parents were able to perform the distraction at home. There were no technical problems with the distraction devices. Two cases had minor cutaneous problems, where the distractor penetrated the skin. These cases responded to gentle local wound care measures. At the time of distractor removal, ossification had occurred sufficiently in one of these two cases. In the other case, the device was removed and replaced with a resorbable plate, without any harmful effect on the result. In all cases, sufficient expansion was achieved without causing more cosmetic deformity. Ossification occurred in all cases. This method seems effective, as the calculated increase in intracranial volume was a mean of 20.2% (range 10.2-28.5%).
Conclusions:
This preliminary series shows that cranial bone distraction is a useful method for cranial expansion with low morbidity in children with craniosynostosis.
Related Concept Videos
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:08
Overview of the Skull
The cranial vault surrounds and protects the brain and houses the middle and inner ear structures. This cavity is bounded superiorly by the rounded top of the skull, which...