Related Experiment Video
Updated: Jun 6, 2026
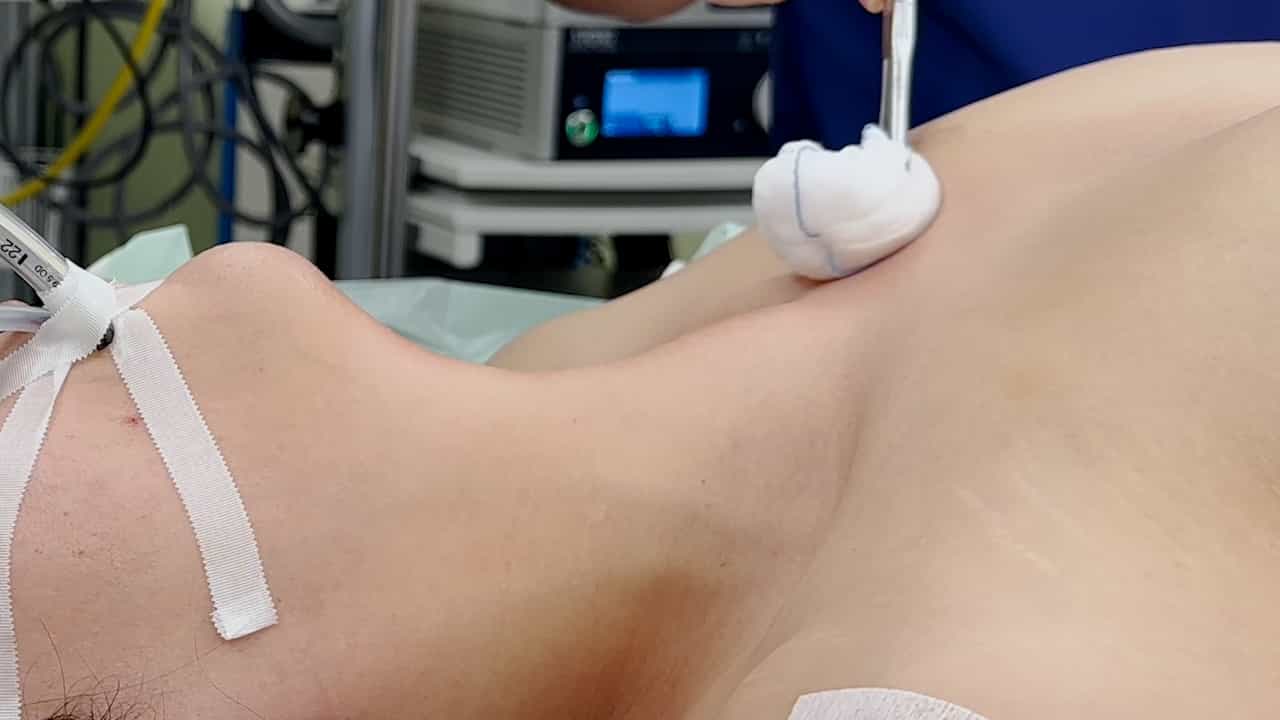

Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
Approach to management of the patient with primary or secondary intrathoracic goiter
Laszlo Hegedüs1, Steen J Bonnema
1Department of Endocrinology and Metabolism, Odense University Hospital, Kløvervænget 6, 3, DK-5000 Odense, Denmark. laszlo.hegedus@ouh.regionsyddanmark.dk

Intrathoracic (substernal) goiter, depending on definition, is seen in up to 45% of all patients operated for goiter. It can either be primary (ectopic thyroid tissue detached from a cervical thyroid mass), which is very rare (1%), or (more commonly) secondary, where a portion of the goiter extends retrosternally. There is no consensus on diagnostic or therapeutic management, partly because many are asymptomatic. Classification involves functional characterization with serum TSH and morphological characterization with diagnostic imaging and cytology to rule out malignancy, which is not more common than in cervical goiters. Pulmonary function is often affected in asymptomatic individuals also. Therefore, but also because natural history is continuous growth and evolution from euthyroidism to hyperthyroidism, most experts recommend therapy. In primary as well as secondary intrathoracic goiter, the therapy of choice is total/near-total thyroidectomy and subsequent levothyroxine substitution. Data suggest that complications are only slightly more prevalent than in cervical goiters. Although levothyroxine is not recommended for goiter shrinkage, there is increasing focus on radioactive iodine as an alternative to surgery in secondary intrathoracic goiters. Here it can reduce thyroid size by on average 40% after 1 yr and improve respiratory function and quality of life. Recent studies show that recombinant human TSH, currently used off-label, can augment the radioiodine-related goiter shrinkage by 30-50%. With currently used doses of recombinant human TSH, the side effects, besides hypothyroidism, are rare and mild. Future studies should also explore the use of radioiodine in primary intrathoracic goiter and compare surgery and radioiodine, head to head.
Intrathoracic (substernal) goiter, depending on definition, is seen in up to 45% of all patients operated for goiter. It can either be primary (ectopic thyroid tissue detached from a cervical thyroid mass), which is very rare (1%), or (more commonly) secondary, where a portion of the goiter extends retrosternally. There is no consensus on diagnostic or therapeutic management, partly because many are asymptomatic. Classification involves functional characterization with serum TSH and morphological characterization with diagnostic imaging and cytology to rule out malignancy, which is not more common than in cervical goiters. Pulmonary function is often affected in asymptomatic individuals also. Therefore, but also because natural history is continuous growth and evolution from euthyroidism to hyperthyroidism, most experts recommend therapy. In primary as well as secondary intrathoracic goiter, the therapy of choice is total/near-total thyroidectomy and subsequent levothyroxine substitution. Data suggest that complications are only slightly more prevalent than in cervical goiters. Although levothyroxine is not recommended for goiter shrinkage, there is increasing focus on radioactive iodine as an alternative to surgery in secondary intrathoracic goiters. Here it can reduce thyroid size by on average 40% after 1 yr and improve respiratory function and quality of life. Recent studies show that recombinant human TSH, currently used off-label, can augment the radioiodine-related goiter shrinkage by 30-50%. With currently used doses of recombinant human TSH, the side effects, besides hypothyroidism, are rare and mild. Future studies should also explore the use of radioiodine in primary intrathoracic goiter and compare surgery and radioiodine, head to head.

Related Concept Videos
 01:27
Goiter
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:26
Angina IV: Management
 01:28
Graves' Disease I: Introduction
 01:23
Hypothyroidism II: Pathophysiology