Related Experiment Video
Updated: Jun 6, 2026

A Bioluminescent and Fluorescent Orthotopic Syngeneic Murine Model of Androgen-dependent and Castration-resistant Prostate Cancer
Published on: March 6, 2018
Reduction in physician reimbursement and use of hormone therapy in prostate cancer
Sean P Elliott1, Stephanie L Jarosek, Timothy J Wilt
1Department of Urologic Surgery, University of Minnesota, 420 Delaware St SE, MMC 394, Minneapolis, MN 55455, USA. selliott@umn.edu

Background:
Use of androgen suppression therapy (AST) in prostate cancer increased more than threefold from 1991 to 1999. The 2003 Medicare Modernization Act reduced reimbursements for AST by 64% between 2004 and 2005, but the effect of this large reduction on use of AST is unknown.
Methods:
A cohort of 72,818 men diagnosed with prostate cancer in 1992-2005 was identified from the Surveillance, Epidemiology, and End Results database. From Medicare claims data, indicated AST was defined as 3 months or more of AST in the first year in men with metastatic disease (n = 8030). Non-indicated AST was defined as AST given without other therapies such as radical prostatectomy or radiation in men with low-risk disease (n = 64,788). The unadjusted annual proportion of men receiving AST was plotted against the median Medicare AST reimbursement. A multivariable model was used to estimate the odds of AST use in men with low-risk and metastatic disease, with the predictor of interest being the calendar year of the payment change. Covariates in the model included age in 5-year categories, clinical tumor stage (T1-T4), World Health Organization grade (1-3, unknown), Charlson comorbidity (0, 1, 2, ≥ 3), race, education, income, and tumor registry site, all as categorical variables. The models included variations in the definition of AST use (≥ 1, ≥ 3, and ≥ 6 months of AST). All statistical tests were two-sided.
Results:
AST use in the low-risk group peaked at 10.2% in 2003, then declined to 7.1% in 2004 and 6.1% in 2005. After adjusting for tumor and demographic covariates, the odds of receiving non-indicated primary AST decreased statistically significantly in 2004 (odds ratio [OR] = 0.70, 95% confidence interval = 0.61 to 0.80) and 2005 (OR = 0.61, 95% confidence interval = 0.53 to 0.71) compared with 2003. AST use in the metastatic disease group was stable at 60% during the payment change, and the adjusted odds ratio of receiving AST in this group was unchanged in 2004-2005.
Conclusions:
In this example of hormone therapy for prostate cancer, decreased physician reimbursement was associated with a reduction in overtreatment without a reduction in needed services.

Related Concept Videos
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra. Symptoms...
 01:28
Menopause
 01:22
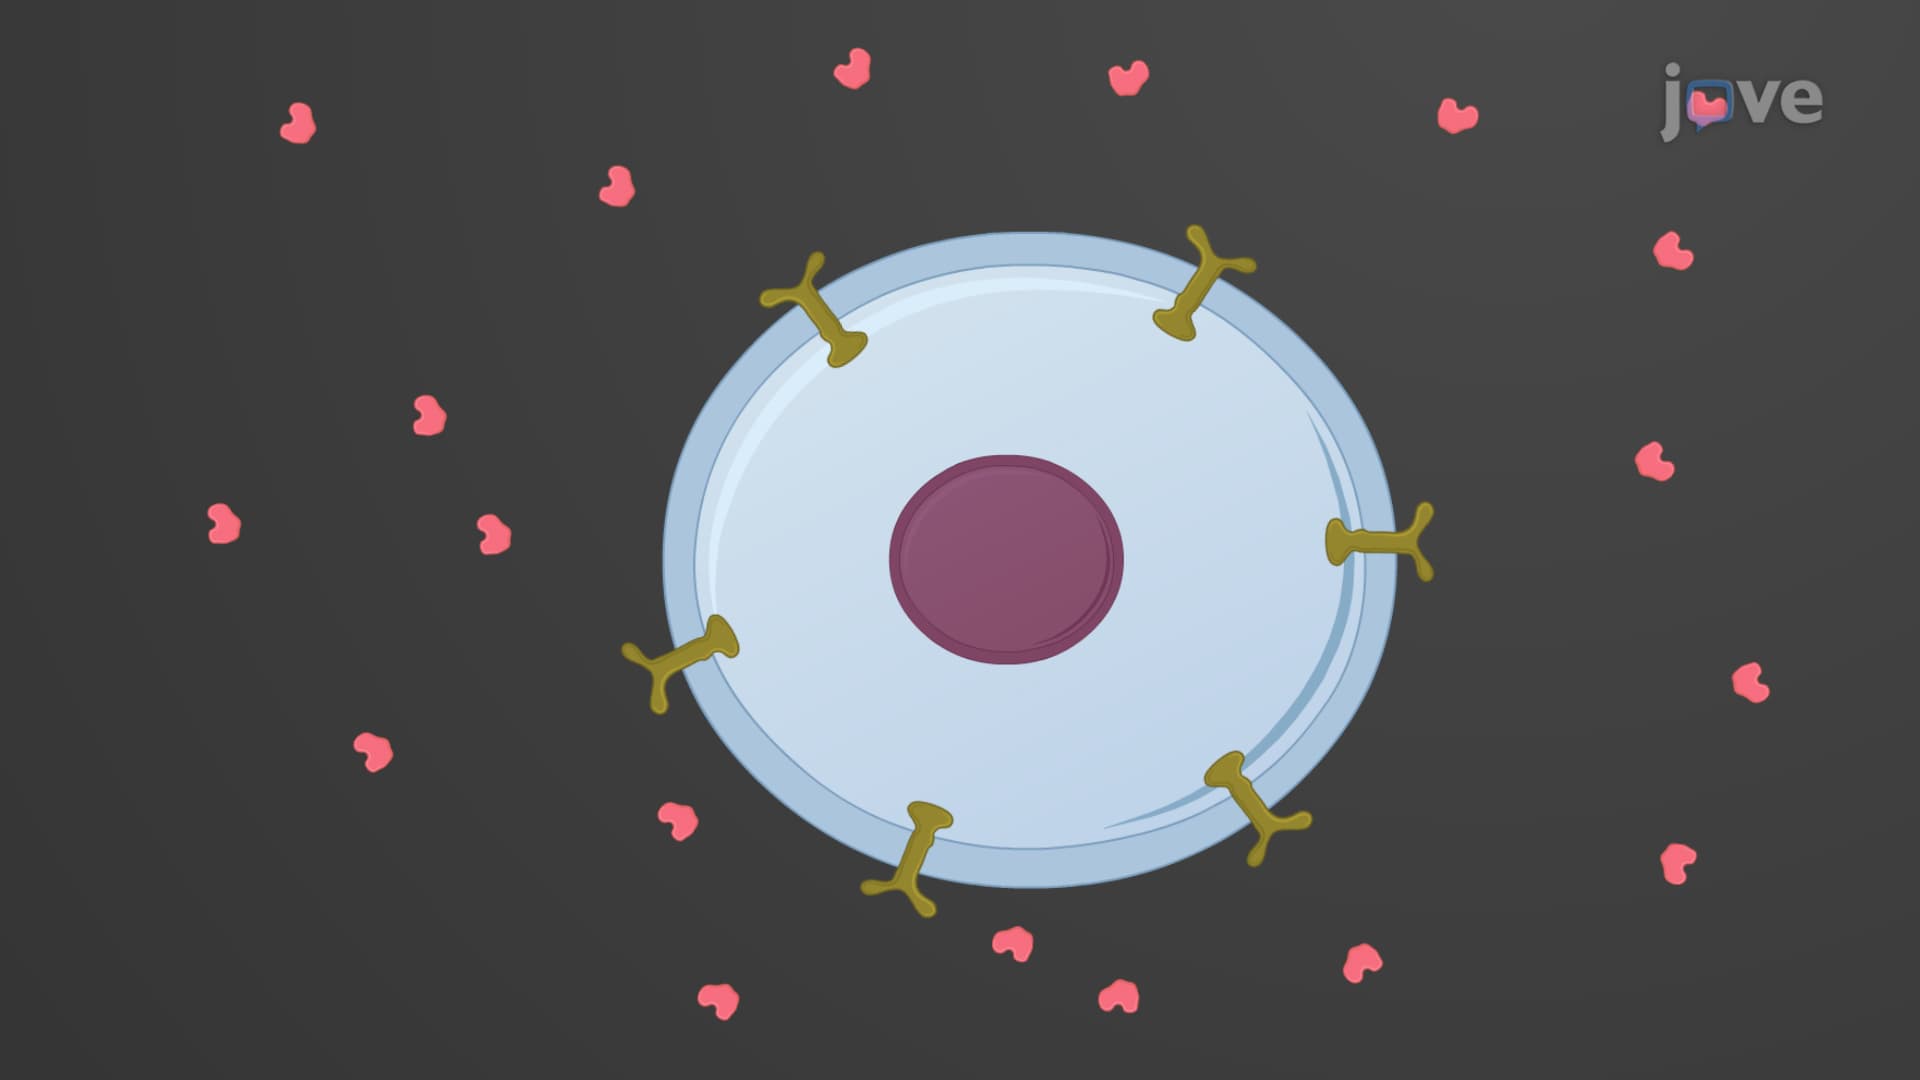
Target Cell Response to Hormones
Notably, the cellular response can be regulated by altering the number of receptors expressed in the cell. For example, prolonged exposure to elevated hormone levels results in a gradual decline or down-regulation in the number of receptors for that specific hormone on the cell surface. Conversely, in response to low hormone levels, cells may use up-regulation, producing an...
 01:29
Issues And Trends In Healthcare Delivery System
Cost Containment
Payment for healthcare services has historically promoted adoption of costly and often unnecessary or inefficient...
 01:22
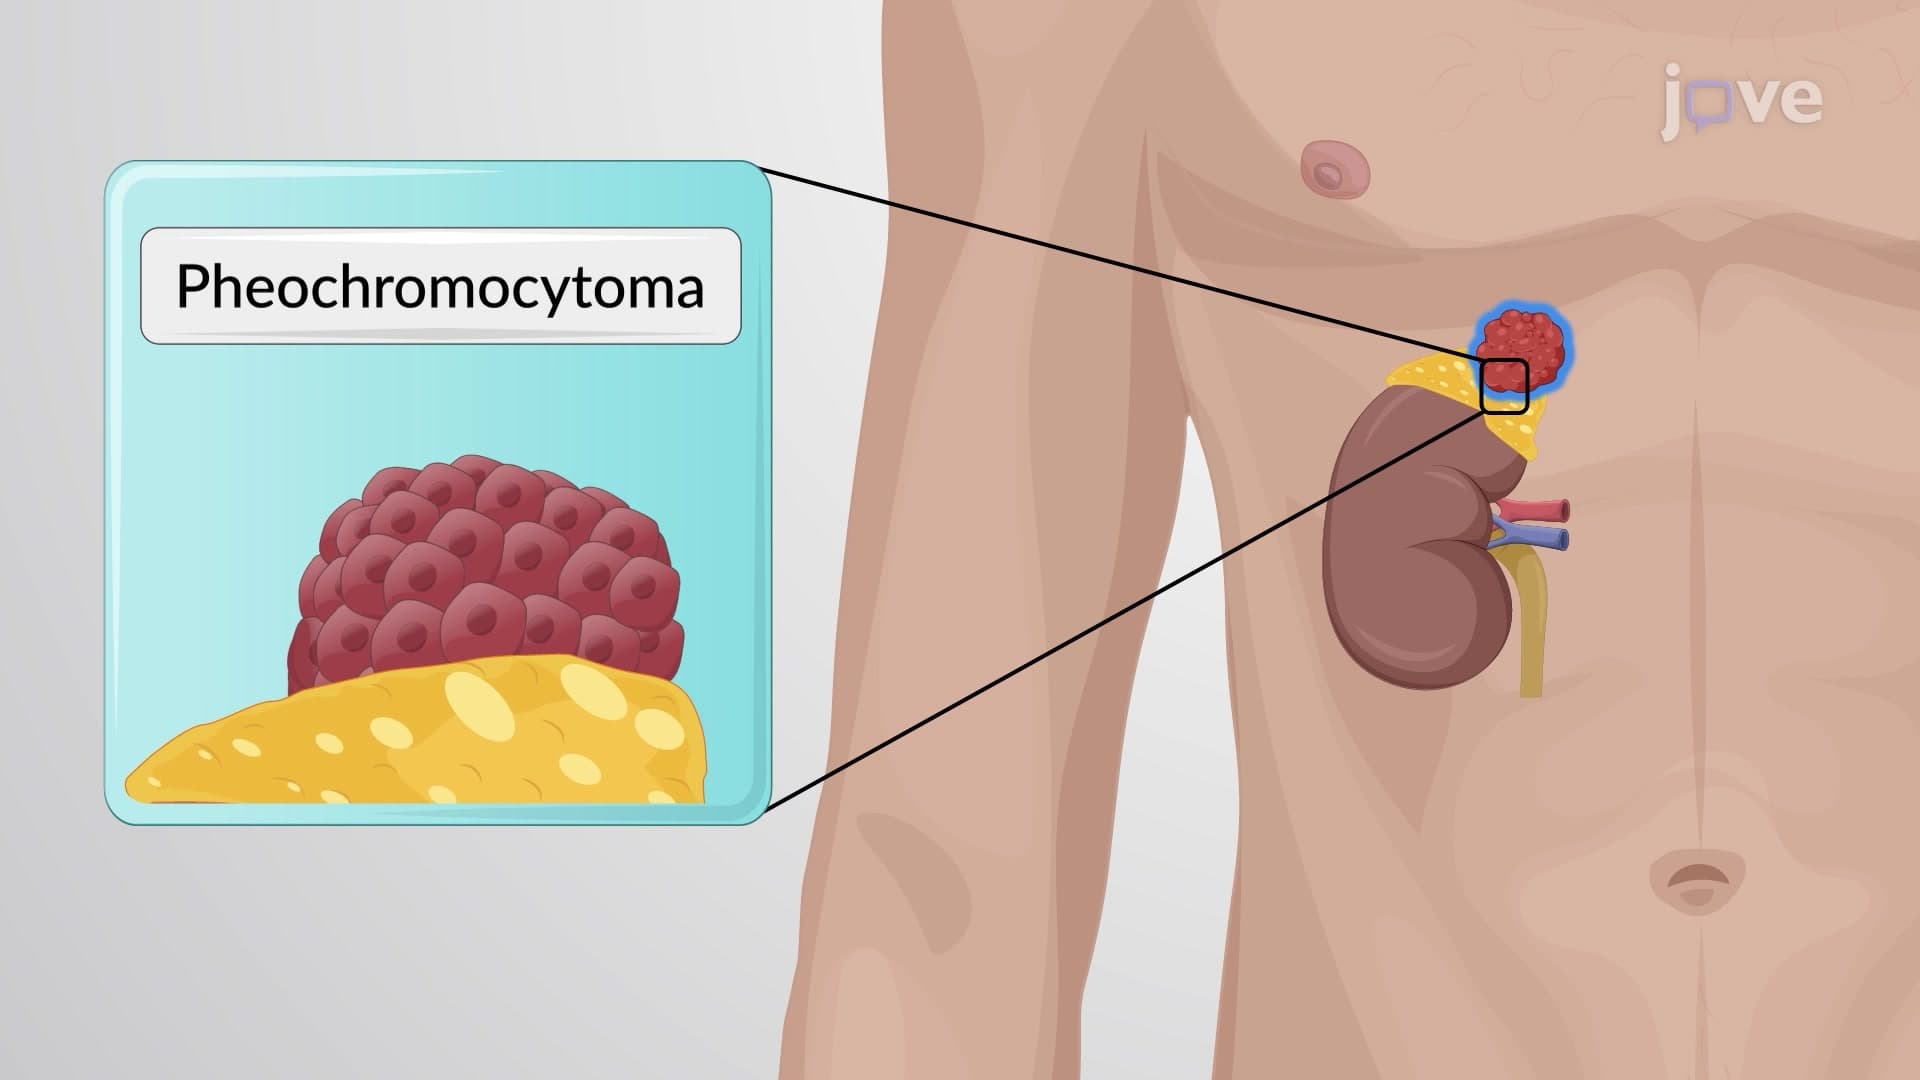
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System