Related Experiment Video
Updated: Jun 6, 2026
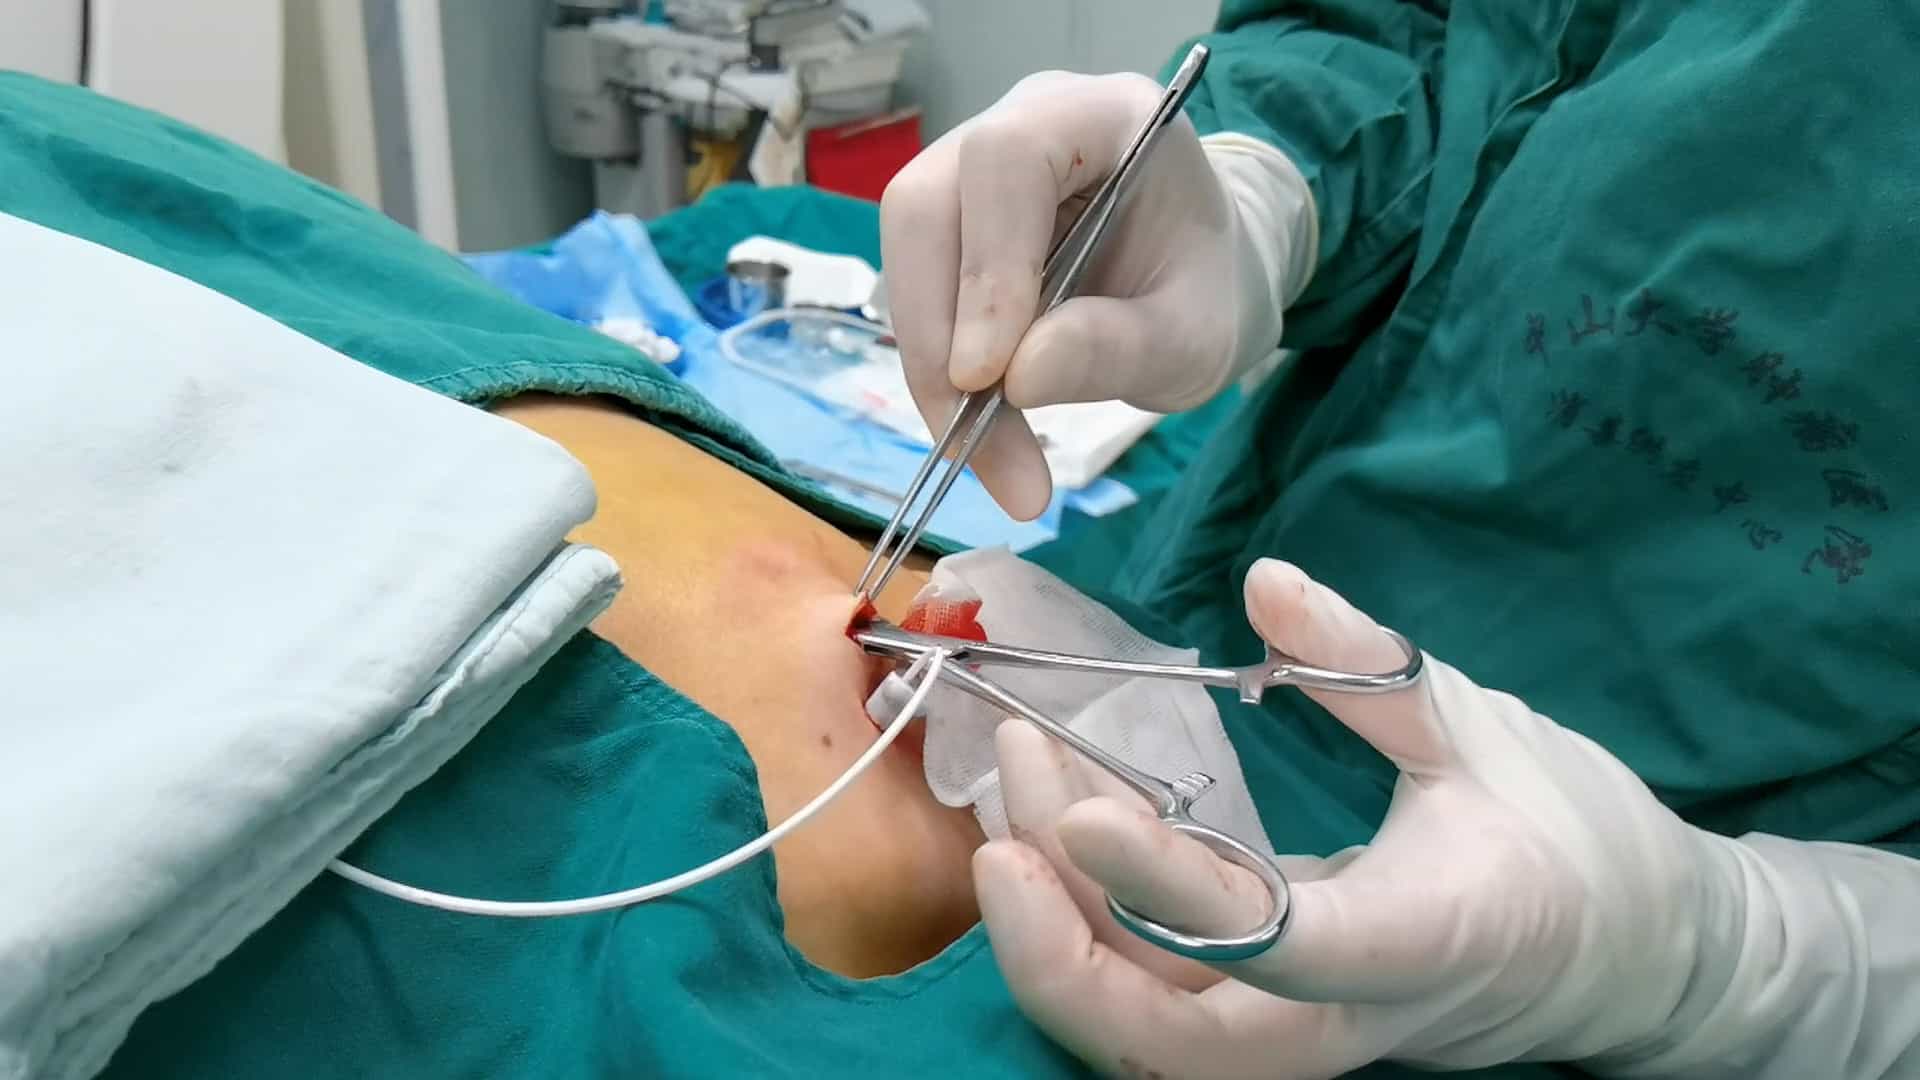

Computed Tomography (CT) Guided Implantation of a Totally Implantable Venous Access Port (TIVAP) through Subclavian Vein
Published on: January 13, 2026
Subclavian venoplasty by the implanting physicians in 373 patients over 11 years
Seth Joseph Worley1, Douglas Charles Gohn, Robert Ward Pulliam
1Implant Program, Heart Center, Lancaster General Hospital, Lancaster, Pennsylvania, USA. seth@mcworley.com

Background:
The need to add a lead(s) despite subclavian/innominate obstruction is increasing. Subclavian venoplasty may be a good alternative to the commonly employed options; however, there are few reports in the literature, and all are by interventional radiologists.
Objective:
To describe the procedural details, results and safety of venoplasty by implanting physicians in a large group of consecutive patients.
Methods:
Safety, lead function and success were established from review of the procedure reports and clinical complications in 373 consecutive venoplasty patients from 1999-2010. Procedural details were obtained by review of the angiograms (venograms) and procedural flow charts of 152 consecutive patients from 2004-2007.
Results:
Venoplasty was successful in 371 of 373 patients without damage to the existing leads and without clinical complications. Total angiographic occlusion was demonstrated in 65% of cases by peripheral venogram, but in only 20% of cases by contrast injection at the site of obstruction; 86% were crossed with a hydrophilic wire. Microdissection and excimer laser were used to cross three of the four wire-refractory occlusions. Obstruction was both central and peripheral in 22.1% of cases and central only in 17%. The time required to cross the obstruction and perform venoplasty was 13 ± 21 minutes. A noncompliant balloon was successful in most, but an ultranoncompliant balloon was required in 13% of cases. Contrast extravasation was common during crossing of a total obstruction and also was observed with balloon rupture on three occasions, but was not clinically significant.
Conclusions:
Subclavian venoplasty is a safe, practical lead-management option that can be used by implanting physicians.