3,423 emergency tracheal intubations at a university hospital: airway outcomes and complications
Related Experiment Video
Updated: Jun 6, 2026
Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Lizabeth D Martin1, Jill M Mhyre, Amy M Shanks
1Department of Anesthesiology, University of Michigan Medical School, Ann Arbor, USA.

Background:
There are limited outcome data regarding emergent nonoperative intubation. The current study was undertaken with a large observational dataset to evaluate the incidence of difficult intubation and complication rates and to determine predictors of complications in this setting.
Methods:
Adult nonoperating room emergent intubations at our tertiary care institution from December 5, 2001 to July 6, 2009 were reviewed. Prospectively defined data points included time of day, location, attending physician presence, number of attempts, direct laryngoscopy view, adjuvant use, medications, and complications. At our institution, a senior resident with at least 24 months of anesthesia training is the first responder for all emergent airway requests. The primary outcome was a composite airway complication variable that included aspiration, esophageal intubation, dental injury, or pneumothorax.
Results:
A total of 3,423 emergent nonoperating room airway management cases were identified. The incidence of difficult intubation was 10.3%. Complications occurred in 4.2%: aspiration, 2.8%; esophageal intubation, 1.3%; dental injury, 0.2%; and pneumothorax, 0.1%. A bougie introducer was used in 12.4% of cases. Among 2,284 intubations performed by residents, independent predictors of the composite complication outcome were as follows: three or more intubation attempts (odds ratio, 6.7; 95% CI, 3.2-14.2), grade III or IV view (odds ratio, 1.9; 95% CI, 1.1-3.5), general care floor location (odds ratio, 1.9; 95% CI, 1.2-3.0), and emergency department location (odds ratio, 4.7; 95% CI, 1.1-20.4).
Conclusions:
During emergent nonoperative intubation, specific clinical situations are associated with an increased risk of airway complication and may provide a starting point for allocation of experienced first responders.
Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
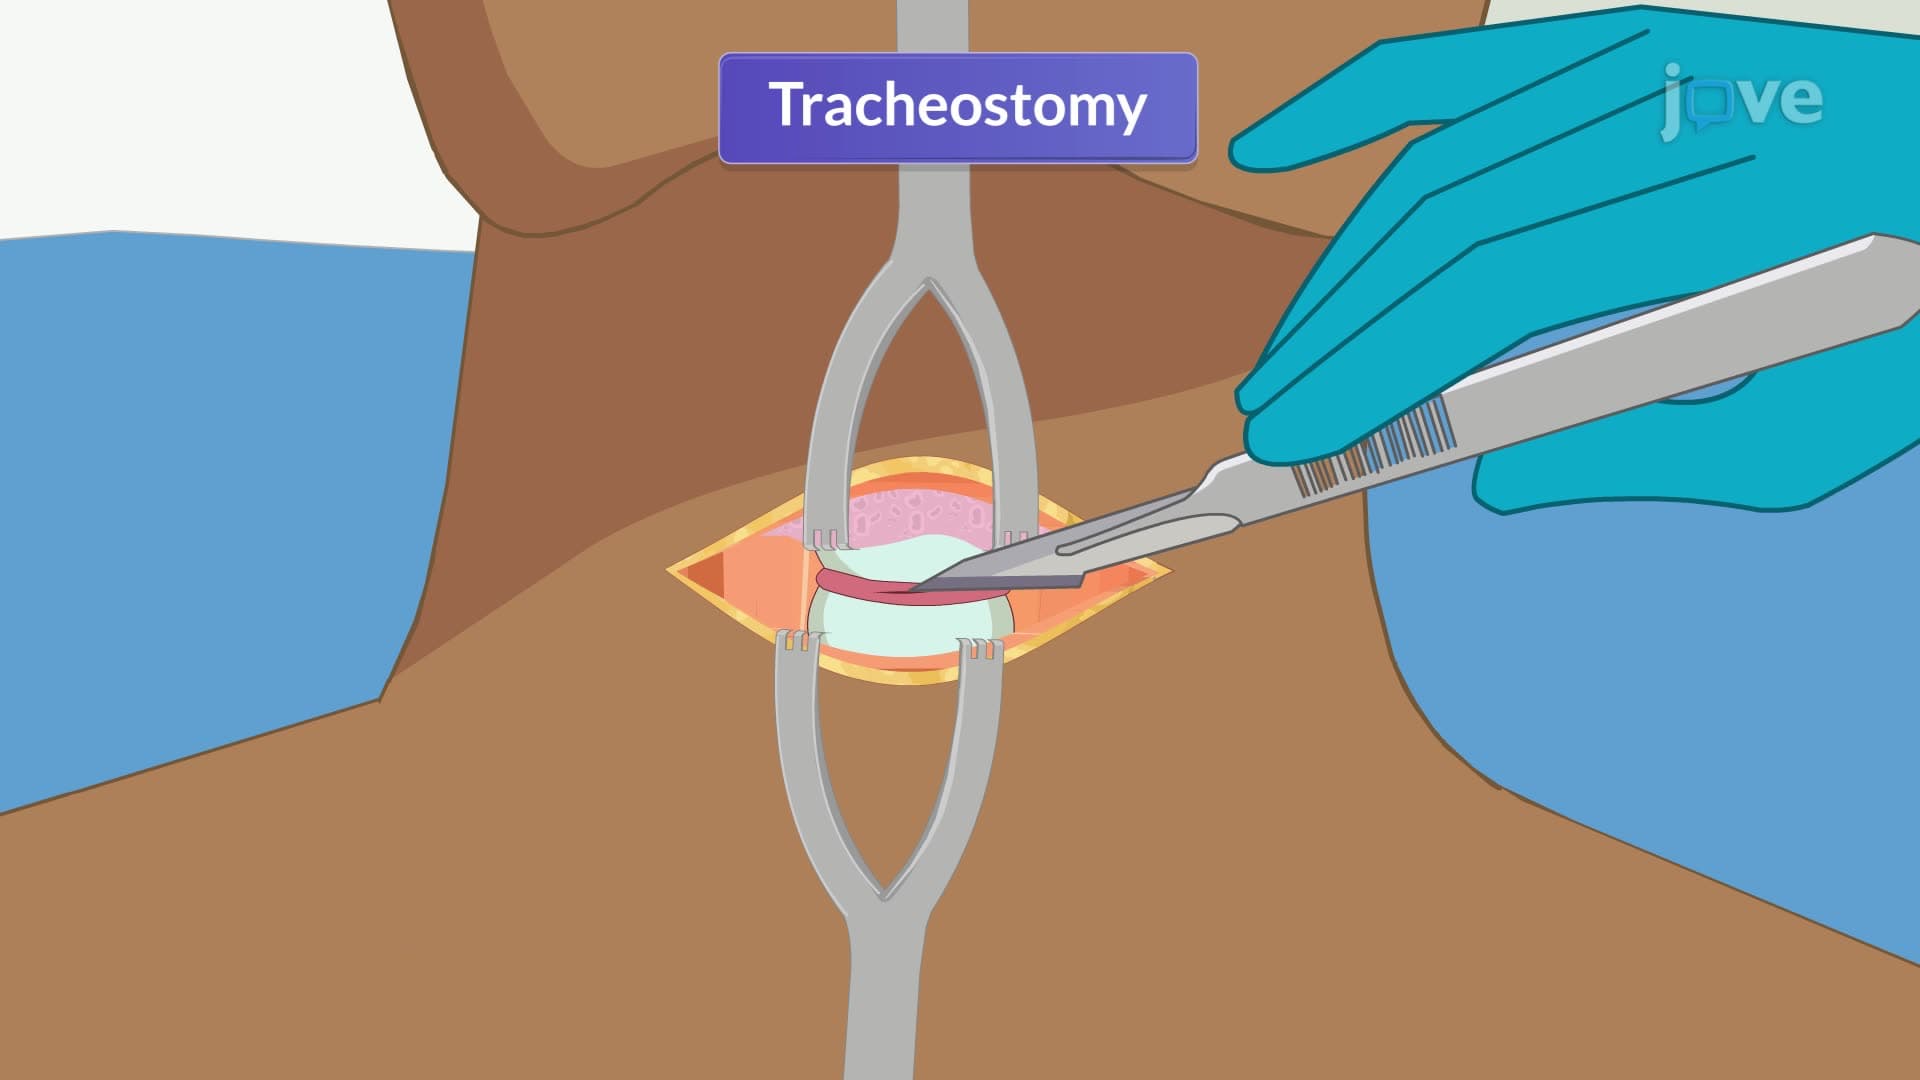
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...