Related Experiment Video
Updated: Jun 6, 2026


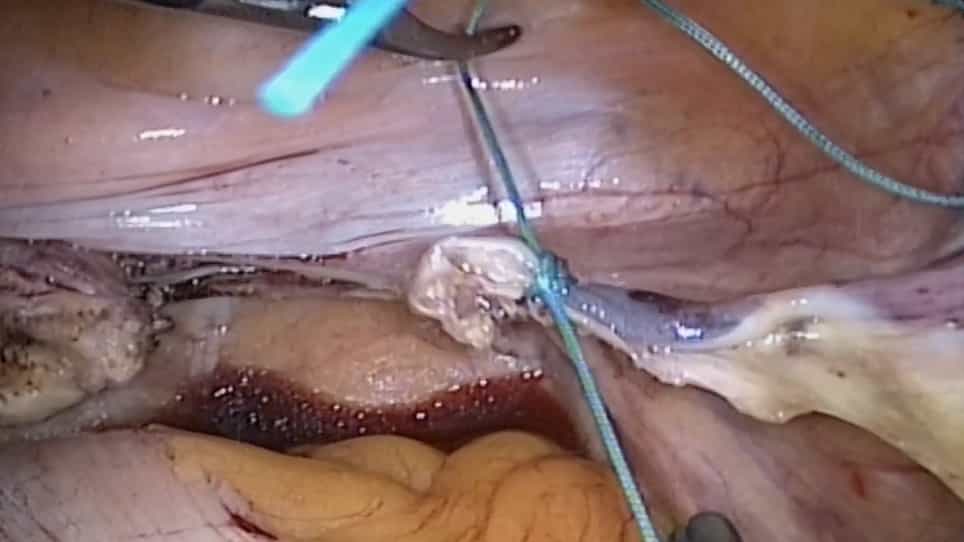
Laparoscopic Non-Mesh Cerclage Pectopexy with Uterine Preservation for Pelvic Organ Prolapse
Published on: October 25, 2024
Operative treatment of the peripelvic Morel-Lavallée lesion
1Klinik für Unfall-, Hand- und Wiederherstellungschirurgie, Universitätsklinikum des Saarlandes, Kirrbergerstr. 1, 66421, Homburg/ Saar, Germany, daniel.koehler@uks.eu.

OBJECTIVE : Evacuation of haematoma, haemostasis, reduction of dead space by vacuum systems for minimisation of secondary complications as full skin necrosis and deep infections, secondary wound closure. INDICATIONS : Morel-Lavallée lesion (MLL). All larger epifascial haematomas. CONTRAINDICATIONS : None. SURGICAL TECHNIQUE : Central longitudinal incision, detection of the subcutanous extent of the haematoma, transection of the full length of the lesion, haemostasis, debridement, application of vacuum systems, secondary wound closure or splitskin coverage. POSTOPERATIVE MANAGEMENT : Vacuum therapy must be continued until secretions are less than 30 ml/24 h. Negative bacterial culture before wound closure is imperative. Daily change of wound dressings, frequent controls of inflammation parameters. Weight bearing until consolidation of soft tissue. RESULTS : Operative treatment of the MLL with vacuum systems is a relatively new concept and results on larger collectives have not been published yet. Eight patients in our hospital underwent vacuum therapy after sustaining a MLL, five of them with concomitant instability of the pelvic ring. Emergency stabilisation and initiation of vacuum therapy were performed on day of admission. Three patients had initially positive bacterial colonialisation. Duration of vacuum therapy was 8,5 days (4-14). Dressings were changed every 2,6 days (1-4). Six wounds could be closed secondarily, two needed split skin coverage. Complications were not observed. Vacuum therapy facilitates wound management and helps to reduce bacterial colonialisation. It has also been proved to have a beneficial effect on qualitative and quantitative granulation.
OBJECTIVE : Evacuation of haematoma, haemostasis, reduction of dead space by vacuum systems for minimisation of secondary complications as full skin necrosis and deep infections, secondary wound closure. INDICATIONS : Morel-Lavallée lesion (MLL). All larger epifascial haematomas. CONTRAINDICATIONS : None. SURGICAL TECHNIQUE : Central longitudinal incision, detection of the subcutanous extent of the haematoma, transection of the full length of the lesion, haemostasis, debridement, application of vacuum systems, secondary wound closure or splitskin coverage. POSTOPERATIVE MANAGEMENT : Vacuum therapy must be continued until secretions are less than 30 ml/24 h. Negative bacterial culture before wound closure is imperative. Daily change of wound dressings, frequent controls of inflammation parameters. Weight bearing until consolidation of soft tissue. RESULTS : Operative treatment of the MLL with vacuum systems is a relatively new concept and results on larger collectives have not been published yet. Eight patients in our hospital underwent vacuum therapy after sustaining a MLL, five of them with concomitant instability of the pelvic ring. Emergency stabilisation and initiation of vacuum therapy were performed on day of admission. Three patients had initially positive bacterial colonialisation. Duration of vacuum therapy was 8,5 days (4-14). Dressings were changed every 2,6 days (1-4). Six wounds could be closed secondarily, two needed split skin coverage. Complications were not observed. Vacuum therapy facilitates wound management and helps to reduce bacterial colonialisation. It has also been proved to have a beneficial effect on qualitative and quantitative granulation.