Related Experiment Video
Updated: Jun 6, 2026
Adult and Pediatric Porcine Model of Acute Volume Overload
Published on: January 12, 2024
Quantitative analysis of continuous intravenous infusions in pediatric anesthesia: safety implications of dead
Haobo Ma1, Mark A Lovich, Robert A Peterfreund
1Department of Anesthesia, Critical Care, and Pain Medicine, Massachusetts General Hospital, Boston, MA 02114, USA.

Insights
Continuous pediatric infusions of propofol and remifentanil can deliver significant fluid loads. Infusion system dead volume and flow rates impact drug delivery, potentially causing inadvertent boluses and long lag times to reach therapeutic levels in neonates.
Area of Science:
- Pharmacokinetics and pharmacodynamics in pediatric populations.
- Analysis of drug delivery systems for continuous infusions.
- Quantitative characterization of anesthetic drug administration in neonates and infants.
Background:
- Systematic examination of drug delivery dynamics in pediatric continuous infusions is lacking.
- Previous analytic models are extended to propofol and remifentanil in infants and toddlers.
- Infusion system dead volume and flow rates are hypothesized to significantly influence drug delivery.
Purpose of the Study:
- To quantitatively characterize continuous pediatric drug infusions.
- To analyze the impact of infusion system parameters on drug delivery.
- To evaluate potential risks associated with propofol and remifentanil administration in pediatric patients.
Main Methods:
- Studied effects of patient weight, infusion system dead volume, drug/carrier flow rates, stock concentration, and dose.
- Calculated drug mass available for inadvertent bolus in dead volume.
- Estimated lag times to achieve targeted steady-state drug delivery rates.
Main Results:
- Drug mass in dead volume increases with dead volume size and dose, potentially exceeding loading doses in infants.
- Lag times to steady state are longest in neonates and depend on patient size and flow rates.
- Infusion fluid quantities can be substantial, increasing with flow rate and dilution, impacting maintenance fluid requirements.
Conclusions:
- Factors influencing drug delivery to circulation are critical, especially for propofol and remifentanil in small patients.
- Inadvertent bolus potential from dead volume is clinically relevant.
- Long lag times and significant fluid loads necessitate careful consideration for pediatric infusions.
Objective:
Quantitative characterization of continuous pediatric drug infusions.
Background:
The dynamics of drug delivery by continuous infusion to pediatric patients have not been systematically examined. This study extends previously described analytic models to propofol and remifentanil delivery, focusing on infants and toddlers. We postulated that infusion system dead volume, and drug and carrier flow rates, significantly influence drug delivery.
Methods:
We studied effects of patient weight, infusion system dead volume, drug and carrier flow rates, along with drug stock concentration and dose, on propofol and remifentanil delivery to the circulation. We calculated the drug mass available for inadvertent bolus in the dead volume, the volume of fluid supplied by drug infusions, and model-based estimates of the range of lag times to achieve a targeted steady-state rate of drug delivery.
Results:
The drug mass in the dead volume at steady state increased with dead volume size and drug dose. For infants, this drug mass could exceed 100% of commonly used loading doses. Predicted lag times to steady state depend on patient size, fluid flow rates, and the mixing behavior of the drug entering the main fluid pathway. Neonates have the longest lag times to achieve steady state. Fluid quantities delivered by drug infusions increase with drug flow rate and can represent a large fraction of estimated maintenance fluid requirements. Fluid delivery increases if stock drug concentrations are diluted. These relationships were qualitatively similar for propofol and remifentanil.
Conclusions:
Traditional studies focus on drug disposition once a drug enters the circulation. Our analysis shows the potential importance of factors influencing drug delivery to the patient's circulation, focusing on propofol and remifentanil administration to small patients. The drug mass available for inadvertent bolus residing in the reservoir of the dead volume at steady state may be large and clinically relevant. Lag times to achieve steady-state delivery are long, depending on the infusion system's architecture and fluid flow rates. By themselves, drug infusions can deliver significant fluid loads to children. These observations have practical and perhaps safety implications for infusions of drugs commonly administered to infants and children.
Related Concept Videos
 01:09
One-Compartment Model: IV Infusion
The one-compartment model for IV infusion uses mathematical equations to describe the rate of change in drug quantity in the body. At steady-state or infusion equilibrium, the drug input...
 01:24
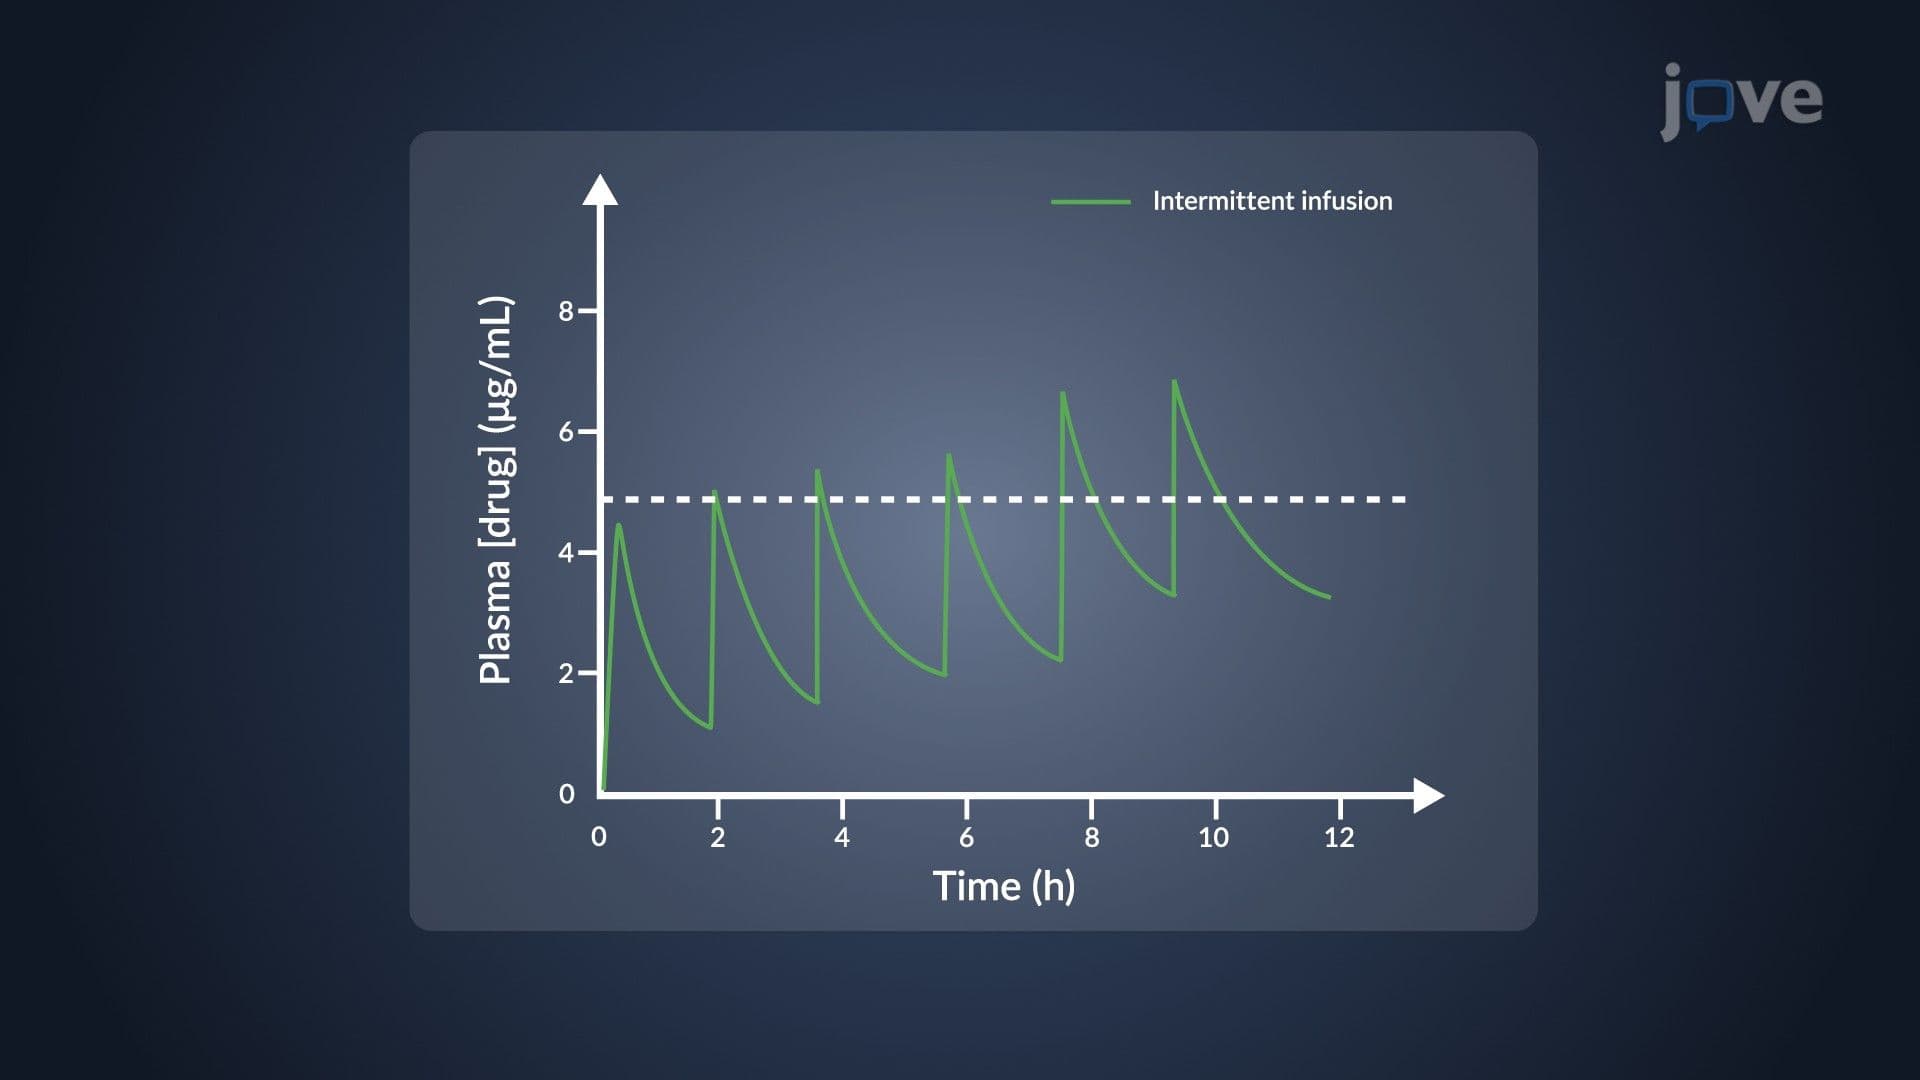
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:29
Drug Dosing: Infants and Children
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:15
Two-Compartment Open Model: IV Infusion
The model illustrates the decrease in plasma drug concentration from the central compartment with a specific equation. It shows that under steady-state conditions, the drug's input rate...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution